
You are using an out of date browser. It may not display this or other websites correctly.
You should upgrade or use an alternative browser.
You should upgrade or use an alternative browser.
Distal radius and proximal humerus fractures
Started by kmurp

Get help with your application
Use all the free resources available to you from SDN: articles, guides, expert advising, forums discussions, and school research.
My partner texted me about a patient with this combo of fractures asking which block(s) would I do for this case. My thoughts were ISB or superior trunk plus SCB or ISB/Superior trunk plus radial nerve just above the elbow. I’d be interested in opinions.
Depending on how proximal the humerus is I think you have to hit C5-C7 cause the incisions might encroach on axillary and suprascapular nerve distributions. And usually for distal radius you have to hit median and radial nerves. I think you're better off just splitting a reasonable volume between both complete ISB and SCB just to make sure you have overlapping coverage and no hotspots.
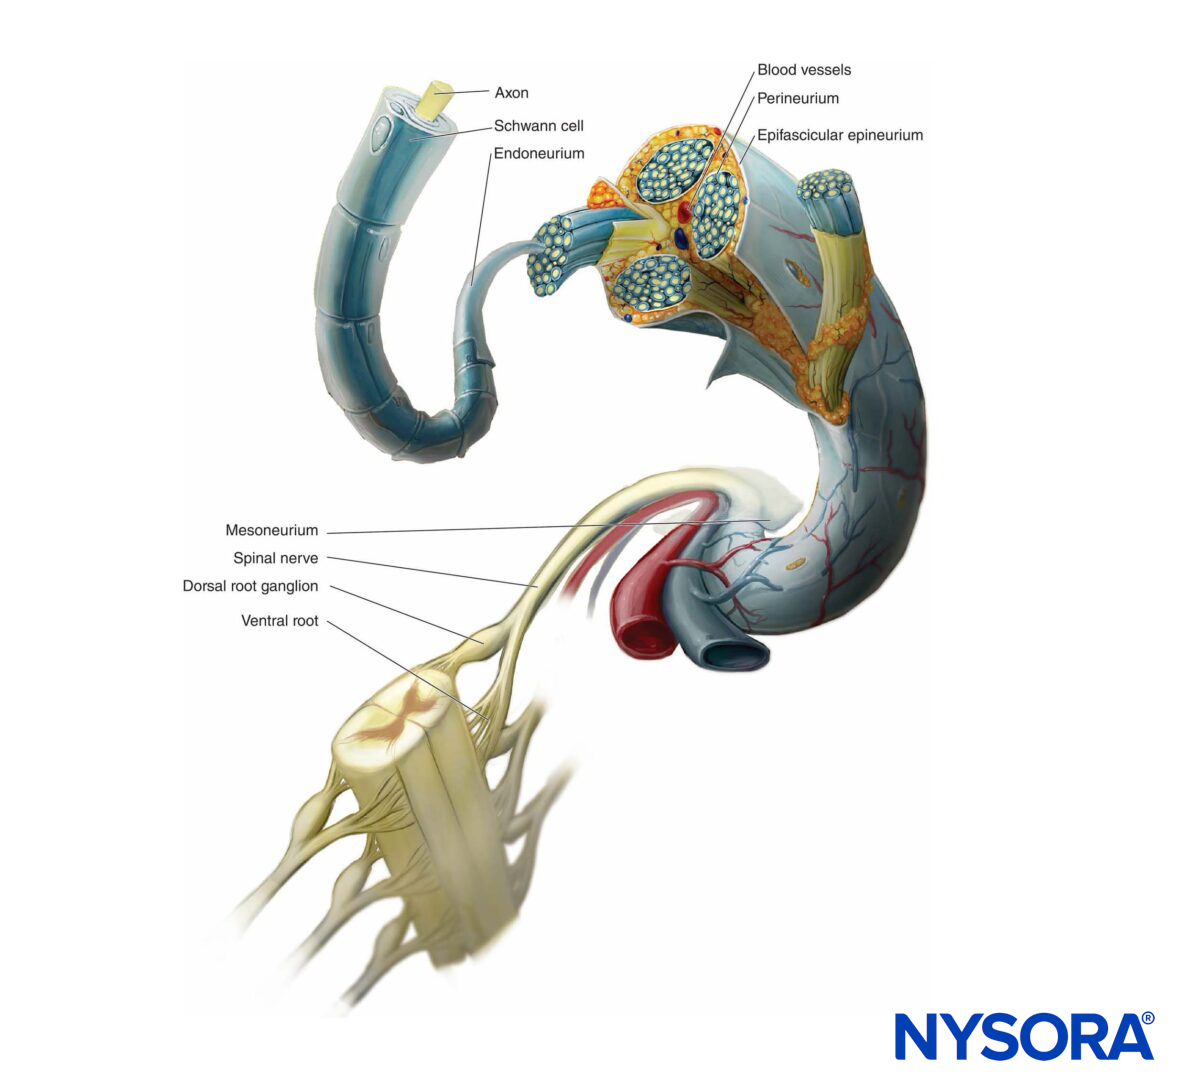
Functional Regional Anesthesia Anatomy - NYSORA
The practice of regional anesthesia is inconceivable without sound knowledge of the functional regional anesthesia anatomy. Just as surgical technique relies on surgical anatomy or pathology leans on pathologic anatomy, the anatomic information necessary for the practice of regional anesthesia...
 www.nysora.com
Infraclav block should work well for both of these fractures
Advertisement - Members don't see this ad

I would think supraclavicular alone would do the job.
D
deleted162650
A well performed SCB is the spinal of the arm.
Shouldn’t a good ISB cover everything needed here?
Shouldn’t a good ISB cover everything needed here?
Radial nerve which probably covers some of the posterior radius osteotome ultimately has some contribution from C8-T1
Last edited:
A well performed SCB is the spinal of the arm.
this guy blocks

I would choose a supraclavicuar block here. An interscalene block would work also provided local was deposited all along the nerve roots including C7. There may be some pain/pressure during the case from the C8 dermatome as well but that should be covered with a LMA
If in the pacu the patient had any shoulder pain I’d place another 10 Mls of local near C5 or C6. Typically, this isn’t necessary with a well placed SCB.
If in the pacu the patient had any shoulder pain I’d place another 10 Mls of local near C5 or C6. Typically, this isn’t necessary with a well placed SCB.
Ask the patient which hurts worse: shoulder or wrist? Proceed from there.
Sent from my iPhone using SDN
Sent from my iPhone using SDN
D
deleted162650
Ask the patient which hurts worse: shoulder or wrist? Proceed from there.
Sent from my iPhone using SDN
Why, just so you can make sure the other one hurts worse after surgery??

Doesn't ISB have ulnar sparing moreso than radial?Radial nerve which probably covers some of the posterior radius osteotome ultimately has some contribution from C8-T1

No the thumb is usually the weakest part of the blockDoesn't ISB have ulnar sparing moreso than radial?
No the thumb is usually the weakest part of the block
"Sensory distribution of the interscalene brachial plexus block (in red). Ulnar nerve distribution area (C8-T1) can also be accomplished by using larger volume (e.g. 15-20 ml) and using low interscalene block where the injection occurs between the ISB and supraclavicular block."

Ultrasound-Guided Interscalene Brachial Plexus Nerve Block - NYSORA
Describes the anatomy and practical approaches to the block of the brachial plexus at the interscalene space (above the clavicle).
www.nysora.com
The ulnar nerve has much more of a contribution from C8-T1 than the radial nerve.
Advertisement - Members don't see this ad
View attachment 306912
"Sensory distribution of the interscalene brachial plexus block (in red). Ulnar nerve distribution area (C8-T1) can also be accomplished by using larger volume (e.g. 15-20 ml) and using low interscalene block where the injection occurs between the ISB and supraclavicular block."
Ultrasound-Guided Interscalene Brachial Plexus Nerve Block - NYSORA
Describes the anatomy and practical approaches to the block of the brachial plexus at the interscalene space (above the clavicle).
The ulnar nerve has much more of a contribution from C8-T1 than the radial nerve.
ISB may work for distal radius, esp when supplemented by the anesthetic. I'm just saying that the radial nerve does have contributions from lower roots (not to mention the deltoid from the axillary n. if we havent forgotten about the humerus) in case someone had a low volume C5-7 ISB in mind. Additionally, if the fracture is very close to the articular parts and then rest of the wrist joint then I would feel uncomfortable not just covering the entire wrist from the getgo.
Last edited:
Why would you do an interscalene block which might cover what you need versus a supraclavicular which you are virtually guaranteed a complete block? Overthinking going on here.
Also given the injury, the orthos around here would request GA anyways. What mechanism caused a prox humerus and distal radius fractures?
Also given the injury, the orthos around here would request GA anyways. What mechanism caused a prox humerus and distal radius fractures?

I'm sure the guy was just standing on the corner minding his own business.Why would you do an interscalene block which might cover what you need versus a supraclavicular which you are virtually guaranteed a complete block? Overthinking going on here.
Also given the injury, the orthos around here would request GA anyways. What mechanism caused a prox humerus and distal radius fractures?
Most likely an old lady with osteoporosis. I see multiple weird fractures all the time. Osteoporosis is a bit(hI'm sure the guy was just standing on the corner minding his own business.
Why would you do an interscalene block which might cover what you need versus a supraclavicular which you are virtually guaranteed a complete block? Overthinking going on here.
Also given the injury, the orthos around here would request GA anyways. What mechanism caused a prox humerus and distal radius fractures?
honest answer is that I’ve done hundreds of ISBs and only dozens of SCBs, but sounds like I should shift my thinking. That’s why I surf here everyday.
An Interscalene block, even a low one near C7, will miss C8 about 10-15 percent of the time. Hence, if you need to block C8 or T1 then an interscalene block is a poor choice vs a supraclavicular or infraclavicular block.
For a radius fracture C7 needs to be blocked so a low interscalene should work most of the time. Still, I rarely ever do an ISB for distal extremity surgery any longer as we have ultrasound which makes the other brachial plexus blocks easy to perform.
c7 dermatome
For a radius fracture C7 needs to be blocked so a low interscalene should work most of the time. Still, I rarely ever do an ISB for distal extremity surgery any longer as we have ultrasound which makes the other brachial plexus blocks easy to perform.
c7 dermatome

Yes: SCB, large volume
My partner did a “low interscalene” (superior trunk maybe) but cheated and put in an LMA as well.
D
deleted162650
“Low interscalene” = SCB

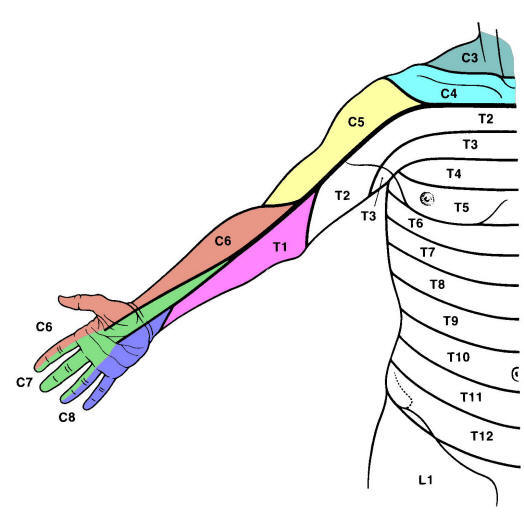
Here is a real image of the dermatomes. The typical incision for an ORIF of a radius involves C7. So, a "low" ISB which blocks C7 is required for good postop pain relief. I prefer a Supraclavicular block which is a superior block for distal upper extremity surgery while also providing very good post op analgesia for a proximal humerus fracture.
Similar threads


- Replies
- 1
- Views
- 506


