
Epidurals for axial low back pain? Didn’t the holier than thou crowd poo poo for discogenic pain? But it’s being ruled out to support intracept?See Glade Roper's LinkedIn post. L3-S1 for Modic changes and axial LBP that failed PT and epidurals. (Hint: Imaging not very supportive for this).
-
CycleTrack and SDN are teaming up to make medical school admissions more transparent and accessible! Read the announcement to learn how we’re supporting the future of CycleTrack’s free application-tracking tools .
You are using an out of date browser. It may not display this or other websites correctly.
You should upgrade or use an alternative browser.
You should upgrade or use an alternative browser.
Experience with Intracept.
Started by Laryngospasm
Get help with your application
Use all the free resources available to you from SDN: articles, guides, expert advising, forums discussions, and school research.

See Glade Roper's LinkedIn post. L3-S1 for Modic changes and axial LBP that failed PT and epidurals. (Hint: Imaging not very supportive for this).
Not signed up for linked in. What the gist about imaging?
That modic changes don’t predict Intracept success or that absence of modic changes doesn’t rule out successful intracept?

Not signed up for linked in. What the gist about imaging?
That modic changes don’t predict Intracept success or that absence of modic changes doesn’t rule out successful intracept?
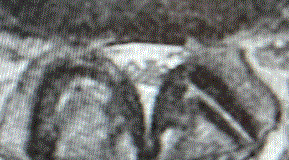
im having trouble finding the spinal stenosis on the MRI he posted. mild at best.
and the ligamentum flavum is borderline enough to do the MILD.
from his linkedin:
this is a typical MILD candidate and one that i did recently, after surgery refused (cardiac history):
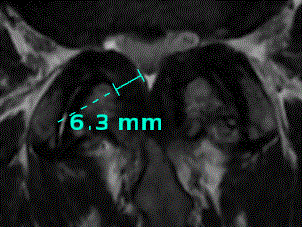
his and other "doctors" use of this procedure outside of the clear indications will lead to its ultimate demise, as has been done with all of our shiny new toys...
and the ligamentum flavum is borderline enough to do the MILD.
from his linkedin:
this is a typical MILD candidate and one that i did recently, after surgery refused (cardiac history):
his and other "doctors" use of this procedure outside of the clear indications will lead to its ultimate demise, as has been done with all of our shiny new toys...
im having trouble finding the spinal stenosis on the MRI he posted. mild at best.
and the ligamentum flavum is borderline enough to do the MILD.
from his linkedin:
View attachment 375505
this is a typical MILD candidate and one that i did recently, after surgery refused (cardiac history):
View attachment 375508
his and other "doctors" use of this procedure outside of the clear indications will lead to its ultimate demise, as has been done with all of our shiny new toys...
This is exactly why I posted.
Nice job on S1. You can see that you can go much more on the cephalad tilt if needed to clear crest
Nice S1
I did one last week. Looks like your s1. In the training video they had thr probe slightly higher toward the L5/s1 disc. I couldn't get it there. Will see in a few weeks the results.
I love the fact we are not implanting anything in this procedure.
D
deleted131481
What diagnosis do you use?Mod to severe spinal stenosis commonly hurts in the back and belt line and I commonly ILESI them with good results.

ClaudicationWhat diagnosis do you use?
D
deleted131481
My 4th and 5th patients are one month out and 50% relief, very please so far.The training/reps will call anything Modic changes. I've done 3 cases so far. One seems to be doing pretty good not a slam dunk, one nothing, and one some mild-moderate relief. The one doing the best I actually had to abort a level - bone was too sclerotic and the stylet bent, just couldn't advance.
Supposedly pain relief keeps going til 3 months out so we'll see. I've got 2 more booked this week. 4 of the 5 total so far are Medicare. Several do have mixed pain. I can't make anything of my n=3 so far. All had anterior column pain but mixed presentation. If I'm not getting great results I may limit to those middle age with more isolated anterior column pain.
We've been doing TIVA starting 2nd case and I'm slow with fellow. We may try true MAC as I get faster.
I’ve done about 70 cases. Results mirror literature.My 4th and 5th patients are one month out and 50% relief, very please so far.
I have only had a handful that were slamdunks at the two week incision check. Most are partially better at that point, some no better, truly does take up to three months. I have had many patient report the biggest change was somewhere in month two.

Do you use 75 degrees for 7 minutes?I’ve done about 70 cases. Results mirror literature.
I have only had a handful that were slamdunks at the two week incision check. Most are partially better at that point, some no better, truly does take up to three months. I have had many patient report the biggest change was somewhere in month two.
Yes, unless I truly was off target despite all possible adjustments, re-access, etc.Do you use 75 degrees for 7 minutes?
I’ve done about 70 cases. Results mirror literature.
I have only had a handful that were slamdunks at the two week incision check. Most are partially better at that point, some no better, truly does take up to three months. I have had many patient report the biggest change was somewhere in month two.
What is your average percentage of pain relief at 3 months with your patients?
What is your average percentage of pain relief at 3 months with your patients?
Haven’t kept track, but probably around 80%. A handful at 100%. A handful at 50. Most somewhere in between.
3 or 4 total failures.
Ask the rep.
is this on the correct thread?

All roads lead to Rome.is this on the correct thread?
Nope. Moving it.is this on the correct thread?

I like to ask once in a while; how do you not loose money doing this procedure? You need to book in the OR, takes a long time, pro fee is very low.

Anyone have any Cigna patients approved yet with the psych required visits. I just sent someone for the CBT today?
Do they require psych therapy? Or do they require a “clearance” like SCS?Anyone have any Cigna patients approved yet with the psych required visits. I just sent someone for the CBT today?
Failure of 3 sessions CBT. And a "clearance" attestation, but that can be done by you.Do they require psych therapy? Or do they require a “clearance” like SCS?
Taus,Available via telehealth. Several companies out there, have used a few for my stim psych clearances. Much better insurance coverage and faster turnaround than local psychologists
What telehealth companies have you used for CBT? I’ve seen my first cigna Intracept candidate and she needs CBT
Also, just saw this….

 www.massdevice.com
Boston Scientific to acquire nerve ablation tech developer Relievant Medsystems for $850M
Boston Scientific announced today that it entered into a definitive agreement to acquire Relievant Medsystems.
www.massdevice.com
Advantage Point BehavioralTaus,
What telehealth companies have you used for CBT? I’ve seen my first cigna Intracept candidate and she needs CBT
And
Www.Carewright.org
Just reviving this thread a bit. I did 2 Intracept cases this am with local/sedation with no issues. Big time saver. HOPD procedure suite. 14 cases so far with 3 failures 5 good responses and the others to soon to tell
Nice, I've done some this way as well. How many VBs, and how much fentanyl/Versed did you use?Just reviving this thread a bit. I did 2 Intracept cases this am with local/sedation with no issues. Big time saver. HOPD procedure suite. 14 cases so far with 3 failures 5 good responses and the others to soon to tell
5 mg Oral Valium. 50 mcg fentanyl. 3 levels. Probably 15cc .25% bupivicaine
Nice. Definitely a huge timesaver without GA.5 mg Oral Valium. 50 mcg fentanyl. 3 levels. Probably 15cc .25% bupivicaine
I’ve done over 100 cases at this point. 4 or 5 failures.
So you have a 97% success rate? That’s incredible.Nice. Definitely a huge timesaver without GA.
I’ve done over 100 cases at this point. 4 or 5 failures.
Nice. Definitely a huge timesaver without GA.
I’ve done over 100 cases at this point. 4 or 5 failures.
Taus, have you done extra-pedicular access for fusion levels? I have several patients with big screws obstructing access.
Have done for BKP but Relievant reps tell me they don't officially sanction this approach for BVN.
Any tips/tricks for fusion levels would be appreciated given your experience.
Thanks
Wow my minimum has been 2 mg versed, 100 mcg fentanyl5 mg Oral Valium. 50 mcg fentanyl. 3 levels. Probably 15cc .25% bupivicaine
Taus, have you done extra-pedicular access for fusion levels? I have several patients with big screws obstructing access.
Have done for BKP but Relievant reps tell me they don't officially sanction this approach for BVN.
Any tips/tricks for fusion levels would be appreciated given your experience.
Thanks
Those are total failures. Zero % relief. I have a few more under 50%, but not zero.So you have a 97% success rate? That’s incredible.
I am nowhere near what the literature claims. For axial back pain I will block/RF facets first then look for Intracept if patient localizes pain to the area of Modic change. But I’ve had too many failures with ideal placement.
For those non hospital employees..you guys actually find this procedure worth your while? I can’t imagine taking time out to go to a hospital, deal with their inefficiencies to do this procedure. I also just don’t see a lot of vertebrogenic back pain. Some people have mixed anterior/posterior column pain but there imaging is just straight up disc disease and facet arthropathy
you can do them in ASCs
It’s a low revenue to time ratio unfortunately. I was going to stop doing it due to OR inefficiency but now that I switched to the procedure room, it’s about a 45 minute block of time. About 11 wrvus so it’s not terrible for me. Facility does very well
Not according to my nj contractsyou can do them in ASCs
I do them in Asc. not bad now with more commercial insurance approvals and increased efficiency on procedure.
This is specific to each individual Asc and their own contracts.Not according to my nj contracts
I’m now actively looking into Intracept.
I’m also now a partner and part owner of our ASC. The ASC does very well on Intracept which is a motivating factor. ( I sent these out previously). And our commercial contracts pay more than 2x Medicare rate for the pro fee.
So I’m looking to get trained and offer intracept. It really helps people, and the pay is more reasonable if you’re RVU based or you have ASC shares.
Last edited:
Agree with all of the above.I do them in Asc. not bad now with more commercial insurance approvals and increased efficiency on procedure.
This is specific to each individual Asc and their own contracts.
I’ve seen two that need it in the last 3 days.I can't line up 5 pts who are ready and waiting on the procedure. How do yall do that?
Define “need” it.I’ve seen two that need it in the last 3 days.
