
-
Practice your interview with the new SDN AI Interview Coach. Choose a school, answer by voice or typing, and receive a personalized feedback report. Available now to all SDN members. Try the AI Interview Coach.
You are using an out of date browser. It may not display this or other websites correctly.
You should upgrade or use an alternative browser.
You should upgrade or use an alternative browser.
More and more programs using SOAP to fill
Started by 2021Doctor


We were once drinking Dom Perignon and Macallan 18 now we hittin up Naty Lite and RC cola at our after parties LOL.This friday is matchday. Many programs patting themselves in match that they “filled” and avoided soap. Bring out the bottles of André, Franzia “chillable red” and plastic red cups. Yay!
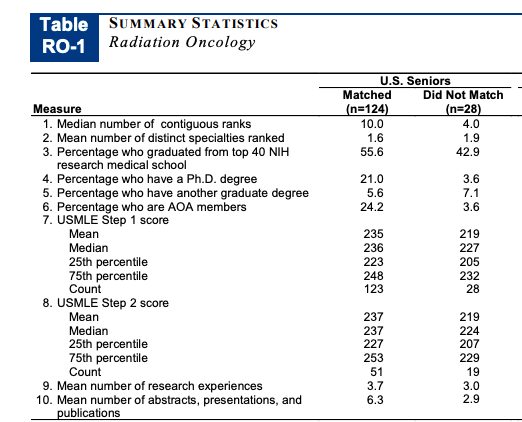
2020 Match Rate for US Seniors = 112/113 = 99.1%
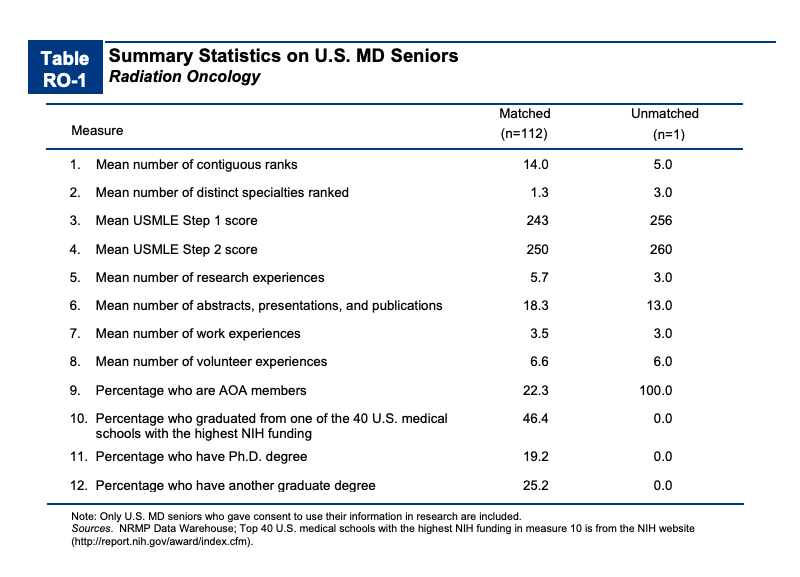
2018 Match Rate for US Seniors = 165/176 = 93.4%
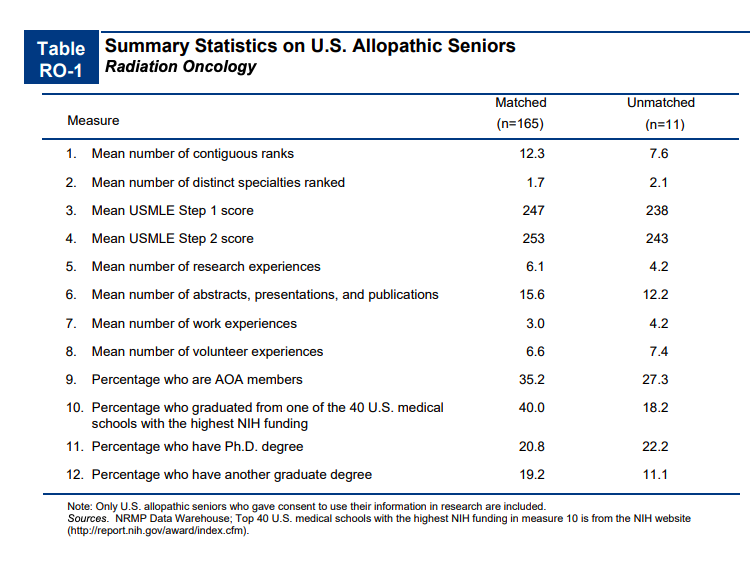
2016 Match Rate for US Seniors = 165/176 = 91.4%
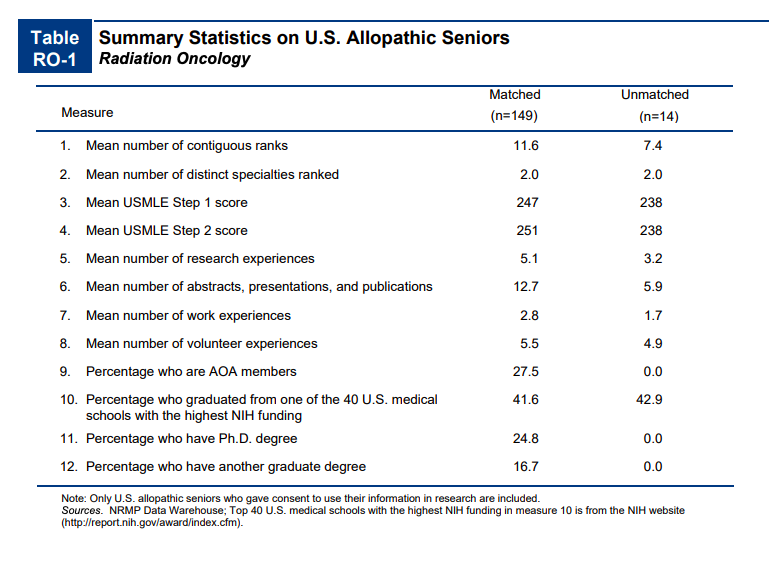
2009 Match Rate for US Seniors = 134/155 = 86.5%
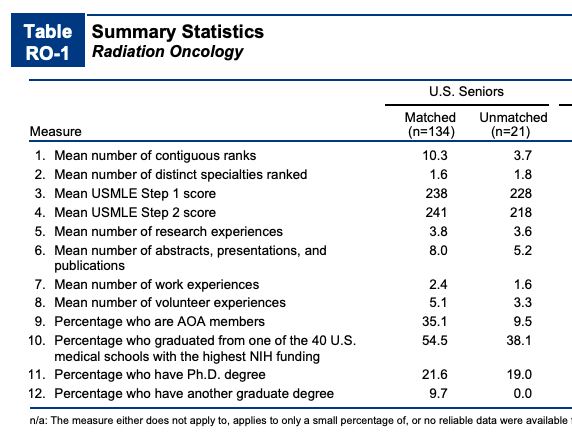
2007 Match Rate for US Seniors = 124/152 = 81.6%
2018 Match Rate for US Seniors = 165/176 = 93.4%
2016 Match Rate for US Seniors = 165/176 = 91.4%
2009 Match Rate for US Seniors = 134/155 = 86.5%
2007 Match Rate for US Seniors = 124/152 = 81.6%
Advertisement - Members don't see this ad
From those 2020 stats, every US MD Rad Onc was an allstar. It was just easier for them to match into what they wanted to, which is good.

I know the folks at my department are strutting around like peacocks about the fact that we don't need to SOAP.This friday is matchday. Many programs patting themselves in match that they “filled” and avoided soap. Bring out the bottles of André, Franzia “chillable red” and plastic red cups. Yay!
I'm just sitting there like...of course you didn't need to SOAP, you basically interviewed and ranked >50% of this year's applicants...
Some are still going to play Russian roulette regardless of the situationFrom those 2020 stats, every US MD Rad Onc was an allstar. It was just easier for them to match into what they wanted to, which is good.
16 of 24 programs that did not fill in the match filled spots in the SOAP yesterday.
OF COURSE they did.16 of 24 programs that did not fill in the match filled spots in the SOAP yesterday.
SOAP ends today, correct? I just checked - it ends at 3PM today.
I anticipate at least 20 of the 24 will fill.

You betcha the ASTRO president is filling those spots. Those notes will get written.
Do any of these candidates actually think they'll be employable in 2026+?
We all know there were bottom of the barrel folks in rad Onc who trained 30-40 years ago and looks like we are coming full circle again between the clear drop in quality and the fact that so many board certified docs are already going to be floating around ready to get first crack on any open jobs first.
We all know there were bottom of the barrel folks in rad Onc who trained 30-40 years ago and looks like we are coming full circle again between the clear drop in quality and the fact that so many board certified docs are already going to be floating around ready to get first crack on any open jobs first.
Same...also criminal record guy (college party incident) matchedI know the folks at my department are strutting around like peacocks about the fact that we don't need to SOAP.
I'm just sitting there like...of course you didn't need to SOAP, you basically interviewed and ranked >50% of this year's applicants...
Echoing DT, he admitted at interview, “yeah I grabbed them by the P”. But ya it was only a college thing, a boo boo you know.Same...also criminal record guy (college party incident) matched
rad onc pd: you would be a great rad onc. Take a seat!
100% of spots will fill eventually. Even those that “stay strong” and don’t SOAP are going to try to fill N+1 next year in the match. Rule 34 of GME, if a spot exists, it will be filled.16 of 24 programs that did not fill in the match filled spots in the SOAP yesterday.

100% of spots will fill eventually. Even those that “stay strong” and don’t SOAP are going to try to fill N+1 next year in the match. Rule 34 of GME, if a spot exists, it will be filled.
Ya this whole exercise is really pointless at the end of the day except for the light that it shines on the specialty and the profound and fundamental issues that it has. These 8 remaining spots will be offered in next year's match, off cycle or whatever. Greedy academic departments are not going to leave money/cheap labor on the table. The data so far shows that the aggregate numbers of trainees will not decrease. And since the RRC will never raise standards in a substantive way the only path forward is to fold the specialty back into radiology as a fellowship, which will allow for a truer labor market to exist. However, in my estimation, we are probably 10 years away from any real steps like that being taken.
The specialty is going the way of nuclear medicine.
Last edited:

So we’re saying Anthony Zietman was totally full of $HIT. Neat. Got it.

 forums.studentdoctor.net
Canaries in a Coal Mine
I recently attended the Annual UCSF Rad Onc course. One of the featured speakers was Anthony Zietman. Dr. Zietman has always been a highly engaging speaker and his topic was particularly timely - "the future of RO as a specialty." Many, many interesting points came out of this talk: 1. He...
forums.studentdoctor.net
Advertisement - Members don't see this ad
On a particularly auspicious note, that post is 1 month shy of its 5-year anniversary. The incubation period for the RadOnc Pipeline.So we’re saying Anthony Zietman was totally full of $HIT. Neat. Got it.
Canaries in a Coal Mine
I recently attended the Annual UCSF Rad Onc course. One of the featured speakers was Anthony Zietman. Dr. Zietman has always been a highly engaging speaker and his topic was particularly timely - "the future of RO as a specialty." Many, many interesting points came out of this talk: 1. He...
Coincidence or clairvoyance? You decide.

So we’re saying Anthony Zietman was totally full of $HIT. Neat. Got it.
Canaries in a Coal Mine
I recently attended the Annual UCSF Rad Onc course. One of the featured speakers was Anthony Zietman. Dr. Zietman has always been a highly engaging speaker and his topic was particularly timely - "the future of RO as a specialty." Many, many interesting points came out of this talk: 1. He...
I don't think he's full of it. I just think that we will continue to fill most positions until there are people going without jobs anywhere at any salary. There are a lot of red flag or international medical students buried in debt and/or with no other prospects to use their degrees. They will be happy to take a chance and fight for whatever they can get.
memories... light the corner of my mind... misty water-color memories... of the way we wereOn a particularly auspicious note, that post is 1 month shy of its 5-year anniversary. The incubation period for the RadOnc Pipeline.
Coincidence or clairvoyance? You decide.
How will we hear about such people. They won't self-report. There were some small single digit no-info gaps in even the most recent ARRO survey. I wondered if the ones we didn't know about were maybe unemployed. We know programs themselves (either attendings or co-residents) won't be rushing to report "Hey my program seems to have produced an unemployed fresh grad." But the year after residency is a small part of a career. I know personally of 3 mid-career rad oncs right now that want to be employed but aren't; 2 were let go recently and are having zero luck in job searching within a few hundred miles of where they live. That's sad folks!I just think that we will continue to fill most positions until there are people going without jobs anywhere at any salary.
So we’re saying Anthony Zietman was totally full of $HIT. Neat. Got it.
Canaries in a Coal Mine
I recently attended the Annual UCSF Rad Onc course. One of the featured speakers was Anthony Zietman. Dr. Zietman has always been a highly engaging speaker and his topic was particularly timely - "the future of RO as a specialty." Many, many interesting points came out of this talk: 1. He...
Argument was BS from the get go b/c of SOAPing. I believe I made comments stating the same in that thread four years ago. I really don't understand why anyone puts any faith in our "leadership" weather its Zietman, a newly woke KO, D. Spratt, the no SOAPing in this program pledgers or anyone else. Literally the only thing that is relevant is reducing complaint and or closing programs. When they start doing that they maybe be worth listening to.
This would be interesting to fold it back into radiology but I am not sure how feasible it would be or if anyone would commit to that for various reasons.Ya this whole exercise is really pointless at the end of the day except for the light that it shines on the specialty and the profound and fundamental issues that it has. These 8 remaining spots will be offered in next year's match, off cycle or whatever. Greedy academic departments are not going to leave money/cheap labor on the table. The data so far shows that the aggregate numbers of trainees will not decrease. And since the RRC will never raise standards in a substantive way the only path forward is to fold the specialty back into radiology as a fellowship, which will allow for a truer labor market to exist. However, in my estimation, we are probably 10 years away from any real steps like that being taken.
The specialty is going the way of nuclear medicine.
View attachment 332802
How long do you think the fellowship would need to be? Radiology is already 5 years without a fellowship.
This would be interesting to fold it back into radiology but I am not sure how feasible it would be or if anyone would commit to that for various reasons.
How long do you think the fellowship would need to be? Radiology is already 5 years without a fellowship.
prob like 6-7 yrs total including 4-5 yr rads then therapeutic rads fellowship. It would be a long time. I am more interested in a systemic therapy pathway as i don’t really care to read films.
Many/most radiologist already do fellowships of 1-2 years currently. This is the easiest path forward. I don't see chemo gate keepers ever getting on board with rad onc doing their own systemic therapies given our general lack of bread and butter medical training (which is essentially none after intern year) unlike gyn/onc and neuro/onc that do extensive inpatient/outpatient medical management.
The only way to fix this issue is for there to be fewer number of programs. How that happens is heavily debated. Leaders state anti-trust laws as the reason why they cannot contract spots. Another option would be to increase case requirements but that isn't going to change anything unless there is a huge change which I doubt. Another option would be to implement a faculty:resident ratio where programs with <1.1 ratio be shut down because of questionable education, which I feel is the best option. A study by Goodman showed that 22% of programs have faculty:resident ratio 1 or less.
Regardless of how it's done, there need to be fewer spots/programs. Otherwise, we will continue to be pumping out 170-190 rad onc residents each year. Even if half the programs don't SOAP, we will still have 175-180 residents which is excessive. I doubt our leaders will make any changes because many only care about themselves/their programs. The ASTRO president who is at WVU is a great example. WVU is a horrid program.
Regardless of how it's done, there need to be fewer spots/programs. Otherwise, we will continue to be pumping out 170-190 rad onc residents each year. Even if half the programs don't SOAP, we will still have 175-180 residents which is excessive. I doubt our leaders will make any changes because many only care about themselves/their programs. The ASTRO president who is at WVU is a great example. WVU is a horrid program.
The issue with clinical faculty/resident ratio is must specify that it is at main site that way hellpit places cannot include adjunct faculty or like satallite people to prop up their “faculty” complements. some of these hellpit programs that are spread around around multiple sites Operate this way. In reality, they have like 2-4 people at main siteThe only way to fix this issue is for there to be fewer number of programs. How that happens is heavily debated. Leaders state anti-trust laws as the reason why they cannot contract spots. Another option would be to increase case requirements but that isn't going to change anything unless there is a huge change which I doubt. Another option would be to implement a faculty:resident ratio where programs with <1.1 ratio be shut down because of questionable education.
Regardless of how it's done, there need to be fewer spots/programs. Otherwise, we will continue to be pumping out 170-190 rad onc residents each year. Even if half the programs don't SOAP, we will still have 175-180 residents which is excessive. I doubt our leaders will make any changes because many only care about themselves/their programs. The ASTRO president who is at WVU is a great example. WVU is a horrid program.
In regards to WV, i totally agree. I think this is the “canary” for nothing is going to change. The politics of how this person became ASTRO president, i understand not. Anybody know?
If they had something like IR with early specialization into rad onc to make it 6 years instead of 7 then it could be feasible IF jobs were guaranteed and paid 500k plus. It would be similar to breast radiology I imagine.prob like 6-7 yrs total including 4-5 yr rads then therapeutic rads fellowship. It would be a long time. I am more interested in a systemic therapy pathway as i don’t really care to read films.
You guys would have to clean through your departments and people would have to actually teach though as it would be condensed and radiologists are used to getting taught (1-2 hours of didactics per day and numerous hours at readout).
If that were to happen, after a few years people without that training would have to retire as no place would hire a rad onc vs these new oncologic radiologists as it currently stands. The new era would have people who would dictate studies when not seeing pts, biopsy potential cancers, independent image follow up, see pts immediately when finding/confirming cancers on imaging/biopsy, tumor boards from the comprehensive oncologic radiologist, etc. All would be exciting and I would probably consider this if in the works when I apply to fellowship.
Attachments

We are probably nearing an inflection point where the median radonc is only something like 12 years into his/her career.
With previous residency contraction (in the nineties) and rapid expansion starting in the mid-2000s, we are becoming a younger and younger (and bigger) specialty on average with each graduating class.
On the face, it seems like this should be a good thing, but it's actually the opposite. It means the spigot of retirement is draining much slower than new docs are being added to the bucket. Likely at approximately a 50% mismatch rate. It's clearly not sustainable.
Before the dreaded unemployment happens, we'll simply just destroy all the jobs out there into lower salary/lower autonomy/more boring/more exploitative drudgery that benefits no one but admins. Not patients. Not doctors.
With previous residency contraction (in the nineties) and rapid expansion starting in the mid-2000s, we are becoming a younger and younger (and bigger) specialty on average with each graduating class.
On the face, it seems like this should be a good thing, but it's actually the opposite. It means the spigot of retirement is draining much slower than new docs are being added to the bucket. Likely at approximately a 50% mismatch rate. It's clearly not sustainable.
Before the dreaded unemployment happens, we'll simply just destroy all the jobs out there into lower salary/lower autonomy/more boring/more exploitative drudgery that benefits no one but admins. Not patients. Not doctors.
yeah i think cleaning up departments has to happen regardless. Faculty young and old who do not teach and persistently have bad evals need to be fired and shunned. They can be locums in Kearney, Nebraska and not interact with any trainees as they persistently failed to nurture and mentor.In many of the bad rad onc departments, faculty give 1-2 lectures a year and half of the faculty get out of it through bs reasons and basically you have residents teaching themselves. The clean up act would be extensive, painful, but necessary.
the problems is many “leaders” are old turds who do not want to lift a finger.
the problems is many “leaders” are old turds who do not want to lift a finger.
On a particularly auspicious note, that post is 1 month shy of its 5-year anniversary. The incubation period for the RadOnc Pipeline.
Coincidence or clairvoyance? You decide.
The leaders in the field are not dumb. In fact, they're incredibly smart.
Everyone that does not benefit from over supply (ie all of us except those of us running hospitals), could see from a mile away that even if the "canaries" of US med grads didn't want to be rad oncs, these spots would fill via SOAP or another mechanism. There was/is no real appetite for actually contracting.
Leaders failed to lead. Hid behind phantom legal concerns* (show me the case law...it doesn't exist), used ridiculous reasoning/rationale for expansion (the old Ben Smith article with nary a mention of hypofrac or use of mid levels in their calculations), then inaction when the clear math was showing major over supply.
The people that have shown the most clarity with regard to thoughts/plans and bravery should be in charge. We need a coup and put Shah, Tendulkar, Simul, Mudit, Fields et al in charge. I bet with them in charge all the phantom "concerns" about how to contract magically disappear.
* Regarding legal concerns....I'd be more worried about a a PGY-1 that graduates in a few years and has no job offers suing someone than a phantom person suing bc spots were contracted. What if you had an email from a chair or PD saying "Job market is just fine" in 2020 and then in 2025 you graduate jobless with debt? The discovery on that case could get wild....as there are some pretty interesting graphs on SDN that would make really nice figures in a courtroom.
Advertisement - Members don't see this ad
In fact if you look at workforce analyses (ACR Bluebook e.g.) from the 1990s, hyperfractionation (which tried very hard to become a common thing in HNSCC) was always mentioned as a reason we'd need more docs (and linacs). But when hypofractionation became common? New math who dis.Leaders failed to lead. Hid behind phantom legal concerns* (show me the case law...it doesn't exist), used ridiculous reasoning/rationale for expansion (the old Ben Smith article with nary a mention of hypofrac or use of mid levels in their calculations), then inaction when the clear math was showing major over supply.
Additionally, a chairman openly stating in an international journal that more residency spots were needed to drive down salaries.The leaders in the field are not dumb. In fact, they're incredibly smart.
Everyone that does not benefit from over supply (ie all of us except those of us running hospitals), could see from a mile away that even if the "canaries" of US med grads didn't want to be rad oncs, these spots would fill via SOAP or another mechanism. There was/is no real appetite for actually contracting.
Leaders failed to lead. Hid behind phantom legal concerns* (show me the case law...it doesn't exist), used ridiculous reasoning/rationale for expansion (the old Ben Smith article with nary a mention of hypofrac or use of mid levels in their calculations), then inaction when the clear math was showing major over supply.
The people that have shown the most clarity with regard to thoughts/plans and bravery should be in charge. We need a coup and put Shah, Tendulkar, Simul, Mudit, Fields et al in charge. I bet with them in charge all the phantom "concerns" about how to contract magically disappear.
* Regarding legal concerns....I'd be more worried about a a PGY-1 that graduates in a few years and has no job offers suing someone than a phantom person suing bc spots were contracted. What if you had an email from a chair or PD saying "Job market is just fine" in 2020 and then in 2025 you graduate jobless with debt? The discovery on that case could get wild....as there are some pretty interesting graphs on SDN that would make really nice figures in a courtroom.
Still unbelievable to me.
Additionally, a chairman openly stating in an international journal that more residency spots were needed to drive down salaries.
Still unbelievable to me.
these people were not the brightest bunch back in day. He said the thing that is said behind closed doors out loud and publicly.
Someone could probably look into how nuclear medicine contracted and has like 3 residency programs now. None of them could be employed on graduation and someone got them all shut down instead of trying to SOAP innocent people.
That would at least be useful to publicize. Compare and contrast nuclear medicine to rad Onc and what they ended up doing as a field.
That would at least be useful to publicize. Compare and contrast nuclear medicine to rad Onc and what they ended up doing as a field.
Last edited:
Someone could probably look into how nuclear medicine contracted and has like 3 residency programs now. None of them could be employed on graduation and someone got them all shut down instead of trying to SOAP innocent people.
That would at least be useful to publicize. Compare and contrast nuclear medicine to rad Onc and what they ended up doing as a field.
That would take an actual interest in actually contracting.
Which would involve improving the prospects of the field and young physicians at the detriment of your own department.

Integrated residency training pathways of the future: diagnostic radiology, nuclear radiology, nuclear medicine, and molecular imaging - PubMed
Following up on the recommendations of the ACR/SNM Task Force on Nuclear Medicine Training, the respective leaderships convened Task Force II. Its charge is to develop realistic residency training pathways integrating diagnostic radiology, nuclear radiology, nuclear medicine, and molecular...
 pubmed.ncbi.nlm.nih.gov
I mean the nucs people dropped their egos and did it 🤷♀️🤷♀️🤷♀️
“the nuclear medicine and diagnostic radiology communities are the imaging-world equivalent of the Dr. Seuss characters called the Zax, who, “marching straight ahead, came face to face” and “refused to budge, stopping the forward progress for both of them.”
sounds very much like RO leadership but enough people got on board to fix the issue
“The challenge for the specialty of nuclear medicine is to attract highly qualified medical students into the field. The number of nuclear medicine residency training programs has decreased from 56 in 2007–2008 to 42 in 2017–2018, with 80 residents currently in training. The number of nuclear radiology programs has decreased from 22 to 18 during the same period, with 12 trainees this year”

 jnm.snmjournals.org
sounds very much like RO leadership but enough people got on board to fix the issue
“The challenge for the specialty of nuclear medicine is to attract highly qualified medical students into the field. The number of nuclear medicine residency training programs has decreased from 56 in 2007–2008 to 42 in 2017–2018, with 80 residents currently in training. The number of nuclear radiology programs has decreased from 22 to 18 during the same period, with 12 trainees this year”
Nuclear Medicine Training in the United States
In the October issue of The Journal of Nuclear Medicine, the authors of the “Hot Topics” paper, “Nuclear Medicine Training: What Now?” suggested a path forward for training in nuclear medicine that “matches the needs of the evolving clinical specialty” by “combined, multispecialty

So what would happen if someone comes on here and explains why their program would SOAP? Pitchforks and torches? Are there any 'good' reasons a program should SOAP this year?
Plenty of good reason$ to SOAP from any individual programs perspective. No real reason form the overall continued health of the specialty's perspective.
There's a litany of seemingly noble reasons why a program can purport to have SOAPed.
They all ignore the broader contextual reality, but I have no doubt they think they're in the right.
They all ignore the broader contextual reality, but I have no doubt they think they're in the right.
Common ways to justify matching any warm body:
1) we NEED residents (i.e programs falls apart)
2) anybody can be taught
3) these notes ain’t gonna write themselves
4) who will see all inpatients?!!!
1) we NEED residents (i.e programs falls apart)
2) anybody can be taught
3) these notes ain’t gonna write themselves
4) who will see all inpatients?!!!
5) Oy, the Dean's not going to like this.Common ways to justify matching any warm body:
1) we NEED residents (i.e programs falls apart)
2) anybody can be taught
3) these notes ain’t gonna write themselves
4) who will see all inpatients?!!!
How will we hear about such people. They won't self-report. There were some small single digit no-info gaps in even the most recent ARRO survey. I wondered if the ones we didn't know about were maybe unemployed. We know programs themselves (either attendings or co-residents) won't be rushing to report "Hey my program seems to have produced an unemployed fresh grad." But the year after residency is a small part of a career. I know personally of 3 mid-career rad oncs right now that want to be employed but aren't; 2 were let go recently and are having zero luck in job searching within a few hundred miles of where they live. That's sad folks!
I know some people with similar stories as well. I've always been surprised that they aren't on SDN screaming their heads off. In reply I get kind of an apathetic, defeatest attitude (what does my story matter?) and also internalization (i.e. there's something wrong with me/I should have done X, Y, or Z).
Standing within the institution.5) Oy, the Dean's not going to like this.
1) we NEED residents (i.e programs falls apart)
2) anybody can be taught
3) these notes ain’t gonna write themselves
4) who will see all inpatients?!!!
5) Oy, the Dean's not going to like this.
Here is #6
6) Students who did not match derm are perfect candidates for radonc residencies. In fact, they can be the future leaders of a new DermRads subspecialty which will require a 4 year radonc residency followed by a 2 year DermRads fellowship!
2) anybody can be taught
3) these notes ain’t gonna write themselves
4) who will see all inpatients?!!!
5) Oy, the Dean's not going to like this.
Here is #6
6) Students who did not match derm are perfect candidates for radonc residencies. In fact, they can be the future leaders of a new DermRads subspecialty which will require a 4 year radonc residency followed by a 2 year DermRads fellowship!
Advertisement - Members don't see this ad

Radonc is still attracting some very strong candidates but it is a shrinking number. One of the real concerns is that if the field continues to lose its standing, not address the current issues and start soaping anyone just to fill a spot, it will become less desirable to these strong candidates who will abandon it in the future.From those 2020 stats, every US MD Rad Onc was an allstar. It was just easier for them to match into what they wanted to, which is good.

7) We found the 1 US Senior who actually applied to Rad Onc and somehow did not match and will be offering that person our spot.Common ways to justify matching any warm body:
1) we NEED residents (i.e programs falls apart)
2) anybody can be taught
3) these notes ain’t gonna write themselves
4) who will see all inpatients?!!!
This is true. People who end up in that situation won't speak up about it.How will we hear about such people. They won't self-report. There were some small single digit no-info gaps in even the most recent ARRO survey. I wondered if the ones we didn't know about were maybe unemployed. We know programs themselves (either attendings or co-residents) won't be rushing to report "Hey my program seems to have produced an unemployed fresh grad." But the year after residency is a small part of a career. I know personally of 3 mid-career rad oncs right now that want to be employed but aren't; 2 were let go recently and are having zero luck in job searching within a few hundred miles of where they live. That's sad folks!
"Wait..... so you scored 260 on Step 1, Honored all your clinical rotations, were inducted into AOA..... and now you're unemployed?"
Not so smart are ya.....
They won't speak up because its embarrassing.
We should have a separate thread anonymously reporting these cases.... if you know of two individuals that can't find jobs it means there are many, many more out there.
A veritable unicorn in 2021 assuming no criminal background check issues7) We found the 1 US Senior who actually applied to Rad Onc and somehow did not match and will be offering that person our spot.
In post-bubble RadOnc, a "POC" now means "person of criminal record".A veritable unicorn in 2021 assuming no criminal background check issues
Similar threads
- Replies
- 6
- Views
- 2K

- Replies
- 20
- Views
- 3K
- Replies
- 11
- Views
- 2K

