
Step II nbme 7

Started by doc0610
This forum made possible through the generous support of SDN members, donors, and sponsors. Thank you.
Get help with your application

Use all the free resources available to you from SDN: articles, guides, expert advising, forums discussions, and school research.

doc0610

Full Member
7+ Year Member
Advertisement - Members don't see this ad
So, I was doing this offline, I was wondering what the answer to this question is
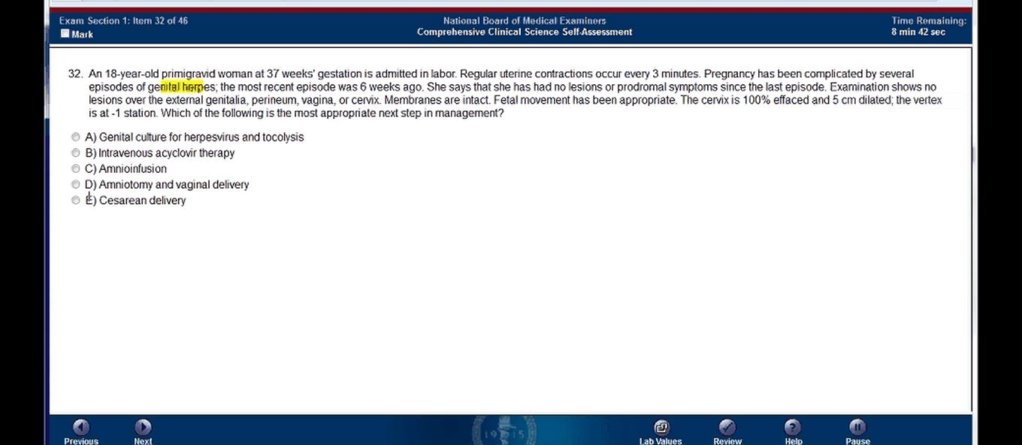
32.JPG


I picked Acyclovir (B)
I figured she is in active labor, why do an amniotomy right now? Yes, the cervix is effaced, but it's only 5 cm dilated and we have no idea of how long she has been in this stage, also, that baby is at -1 station.

Labor is my weakest area!
 
I think its D. The mom has a long history so she's got antibodies against it which she is passing to the baby and she currently has no active lesions. Active lesions or a a newly acquired infection would be indications for Cesarian. Acyclovir can be given to suppress the infection during pregnancy but at this point it wouldn't do anything.
 
I think its D. The mom has a long history so she's got antibodies against it which she is passing to the baby and she currently has no active lesions. Active lesions or a a newly acquired infection would be indications for Cesarian. Acyclovir can be given to suppress the infection during pregnancy but at this point it wouldn't do anything.

But, is this an indication for amniotomy? SO, if the lady had no h/o herpes and she was in the same situation, we would still do amniotomy or just wait it out? I think my question is why are we doing amniotomy, what is the indication here? how do we know the labor is not progressing?
 
But, is this an indication for amniotomy? SO, if the lady had no h/o herpes and she was in the same situation, we would still do amniotomy or just wait it out? I think my question is why are we doing amniotomy, what is the indication here? how do we know the labor is not progressing?

I haven't taken 7 so I may be wrong. I think the amniotomy was put in as a distractor. It didn't mention whether her membranes had ruptured so I guess they wanted you to assume that they hadn't, and thus would need to be ruptured artificially in order for labor to proceed. And they wanted to throw people off who assumed they had ruptured and make them second guess the vaginal delivery. But either way C vaginal delivery would be warranted in a mother without recent active lesions so in this case its really the only answer that makes sense even if you aren't certain about the amniotomy part.
 
Advertisement - Members don't see this ad
ok, thank you 🙂 I was just trying to figure out, if in other scenarios amniotomy was an option, when would i use it? If the labor was arrested?
 
ok, thank you 🙂 I was just trying to figure out, if in other scenarios amniotomy was an option, when would i use it? If the labor was arrested?
From what I remember back on OB rotation if the woman came in in labor and her water hadn't broken then you did amniotomy and allowed it to proceed. I think the hope is that once the fluid drains gravity forces the kid down and lets the muscles start engaging and pushing it out. If there was some reason why you didn't want it to proceed- i.e. premature, c-section indicated, etc..then you didn't perform amniotomy because rupturing the membrane puts the kiddo at increased risk of infection, cord accidents, etc.
 
I missed this one too. as far as I can gather:
no active lesions -> no ppx, vaginal delivery
active lesions -> c/s, no ppx(?), treat baby quickly if symptoms arise.
 
ok, thank you 🙂 I was just trying to figure out, if in other scenarios amniotomy was an option, when would i use it? If the labor was arrested?

If a mother has a prolonged labor and you need to get stuff rolling then you do an Amniotomy. It's pretty much for inducing or expediting labor.
 
From what I remember back on OB rotation if the woman came in in labor and her water hadn't broken then you did amniotomy and allowed it to proceed. I think the hope is that once the fluid drains gravity forces the kid down and lets the muscles start engaging and pushing it out. If there was some reason why you didn't want it to proceed- i.e. premature, c-section indicated, etc..then you didn't perform amniotomy because rupturing the membrane puts the kiddo at increased risk of infection, cord accidents, etc.

During my OB rotation, my observations were that if we were swamped, the resident would be in no hurry to rupture, but if things on the L&D floor were quiet, the resident would go ahead and perform amniotomy to get things going.
