

-
CycleTrack and SDN are teaming up to make medical school admissions more transparent and accessible! Read the announcement to learn how we’re supporting the future of CycleTrack’s free application-tracking tools .
You are using an out of date browser. It may not display this or other websites correctly.
You should upgrade or use an alternative browser.
You should upgrade or use an alternative browser.
United Health Care - Bone Met
Started by SneakyBooger

Get help with your application
Use all the free resources available to you from SDN: articles, guides, expert advising, forums discussions, and school research.

They want you to treat with 2D, and no IGRT (Sounds like I'm joking, but that's legit what they will say on your peer to peer. 3D-CRT only for re-treatment, etc.)

My guess is they want you to use an isodose plan rather than a 3D plan. It's bogus, but that's the only thing I can think of
Advertisement - Members don't see this ad
Can check private forum for tips and tricks for getting things like igrt etc approvedUNH requiring peer to peer for 3DCRT for 3 bone mets, single fraction, kV - kV matching...
What am I missing here?

Once you're doing a p2p where they're denying 3D, it's hard to shake them off that scentUNH requiring peer to peer for 3DCRT for 3 bone mets, single fraction, kV - kV matching...
What am I missing here?
D
deleted1116990
BTDT. On the phone, "Are you serious?" Then silence...They want you to treat with 2D, and no IGRT (Sounds like I'm joking, but that's legit what they will say on your peer to peer. 3D-CRT only for re-treatment, etc.)
While you plan with a CT, probably contour target volumes, and review isodoses, DVH, etc. they do not consider it 3D. There have been some arbitrary criteria in the past (need 3 OARs to spare) but now I think Evicore and others simply do not approve 3D for palliation of bone mets without soft tissue extension, and won't approve IGRT unless there is something particularly exceptional that necessitates it.
D
deleted1116990
While you plan with a CT, probably contour target volumes, and review isodoses, DVH, etc. they do not consider it 3D. There have been some arbitrary criteria in the past (need 3 OARs to spare) but now I think Evicore and others simply do not approve 3D for palliation of bone mets without soft tissue extension, and won't approve IGRT unless there is something particularly exceptional that necessitates it.
Soft tissue extension doesn't always get it either. I had a vertebral met with soft tissue extension. Wasn't significant in that location or something. Not like soft tissue extension should matter or not. But it's not an automatic way to get through on a technicality. Will still deny if they want.
Yeah- it's crazy. I've occasionally had luck appealing to the insurer (since they have the final say and only use Evicore is a contracted 'service').
Have only seen them approve 15 when that's the case instead of 10. Otherwise still complex and no igrtSoft tissue extension doesn't always get it either. I had a vertebral met with soft tissue extension. Wasn't significant in that location or something. Not like soft tissue extension should matter or not. But it's not an automatic way to get through on a technicality. Will still deny if they want.
Bingo. Do an appeal directly to the payor.Yeah- it's crazy. I've occasionally had luck appealing to the insurer (since they have the final say and only use Evicore is a contracted 'service').
Most of the time these are emergency situations and we just can't wait that long.
D
deleted1116990
This is such a waste of time to argue and often results in just accepting the lower payments or eating it.
At what point does our job market become so awful and this prior auth stuff so ridiculous that every practice just hires a new grad for 300k whose job is primarily to spend all day on the phone arguing with similarly paid evicore docs who also can't find a real job?
At what point does our job market become so awful and this prior auth stuff so ridiculous that every practice just hires a new grad for 300k whose job is primarily to spend all day on the phone arguing with similarly paid evicore docs who also can't find a real job?
We have a few FTEs for auths already. Not hard to just use one doc to handle diagnostic and RO duties thereThis is such a waste of time to argue and often results in just accepting the lower payments or eating it.
At what point does our job market become so awful and this prior auth stuff so ridiculous that every practice just hires a new grad for 300k whose job is primarily to spend all day on the phone arguing with similarly paid evicore docs who also can't find a real job?

Fast-forward to 2024 . . .
Request 2D without IGRT for a bone met.
Denied, needs peer-to-peer.
UHC Rad Onc: "We want you to hold a piece of Iridium next to where the patient is having pain for a couple of minutes. One fraction only."
Request 2D without IGRT for a bone met.
Denied, needs peer-to-peer.
UHC Rad Onc: "We want you to hold a piece of Iridium next to where the patient is having pain for a couple of minutes. One fraction only."
Advertisement - Members don't see this ad
This is, interestingly, also the climate-friendly solutionFast-forward to 2024 . . .
Request 2D without IGRT for a bone met.
Denied, needs peer-to-peer.
UHC Rad Onc: "We want you to hold a piece of Iridium next to where the patient is having pain for a couple of minutes. One fraction only."
D
deleted1116990
Welcome to palliative RT in 19222022:

Also it fixes the problem of having too many Rad OncsThis is, interestingly, also the climate-friendly solution
United is a payor and they are doing in-house RadOnc pre-auth review now? Smart
Evicore has been denying 3D or IGRT for bone mets for some time now. Not worth arguing
Evicore has been denying 3D or IGRT for bone mets for some time now. Not worth arguing

Things that have helped me get approval with 3D and IGRT (KV):
- Soft tissue extension (i.e. tumor not just limited to bone)
- BMI >30 (some plans require >35)
- Severe patient discomfort (patient wiggling around due to back pain means imaging required to make sure I'm hitting my target)
This is all very dumb and extremely frustrating. There are some legislative efforts underway to reduce this burden for Medicare Advantage plans (which is source of the bulk of my p2p time is spent).

There are some legislative efforts underway to reduce this burden for Medicare Advantage plans (which is source of the bulk of my p2p time is spent).
oh really? can you elaborate? interesting.

Just to really hammer this point home:- Soft tissue extension (i.e. tumor not just limited to bone)
- BMI >30 (some plans require >35)
- Severe patient discomfort (patient wiggling around due to back pain means imaging required to make sure I'm hitting my target)
Some of my friends and colleagues, when I have recommended ways to communicate soft tissue extensive to the Evil Empire, balk at what seems like "stretching the truth".
Sure, if you have a single small lesion in the middle of the right iliac crest, I get it.
However: the majority of the time, when a patient is referred for palliation of a bone lesion(s), it's based on JUST imaging, right? So how can you be absolutely certain there is ZERO soft tissue extension? You can't. You can only know that for certain if you do an en bloc resection and be like "yup, this was completely confined to bone, good thing I know that".
But most importantly: if you feel that 3D and IGRT are in your patient's best interest, then you are ethically bound to make that happen. eviCore and UHC and whoever else are acting as a barrier to the care that you have deemed necessary. If a treatment is in the best interest of your patient, than blinding the benefit managers with BS is the actual "moral highroad".
Now, if you're doing it just to generate some more RVUs, then get bent.
oh really? can you elaborate? interesting.

Just ask for SBRT and cite the meta-analysis showing faster and more durable response rates. I just read a patterns of care study from Memorial showing that SBRT has essentially replaced 30 in 10 even for previously unirradiated bone mets.
MSKCC network is doing 1000 vertebral SBRTs a year! It’s nearly 1 in 5 under beam patients in Manhattan. It sure does cost a lot to make pain go away versus cheaper options.Just ask for SBRT and cite the meta-analysis showing faster and more durable response rates. I just read a patterns of care study from Memorial showing that SBRT has essentially replaced 30 in 10 even for previously unirradiated bone mets.
where is this published?MSKCC network is doing 1000 vertebral SBRTs a year! It’s nearly 1 in 5 under beam patients in Manhattan. It sure does cost a lot to make pain go away versus cheaper options.
Right here on SDN.where is this published?
1. Spratt D. What is the problem...can one define it? Let your voice be heard.... Accessed Aug 11, 2022.
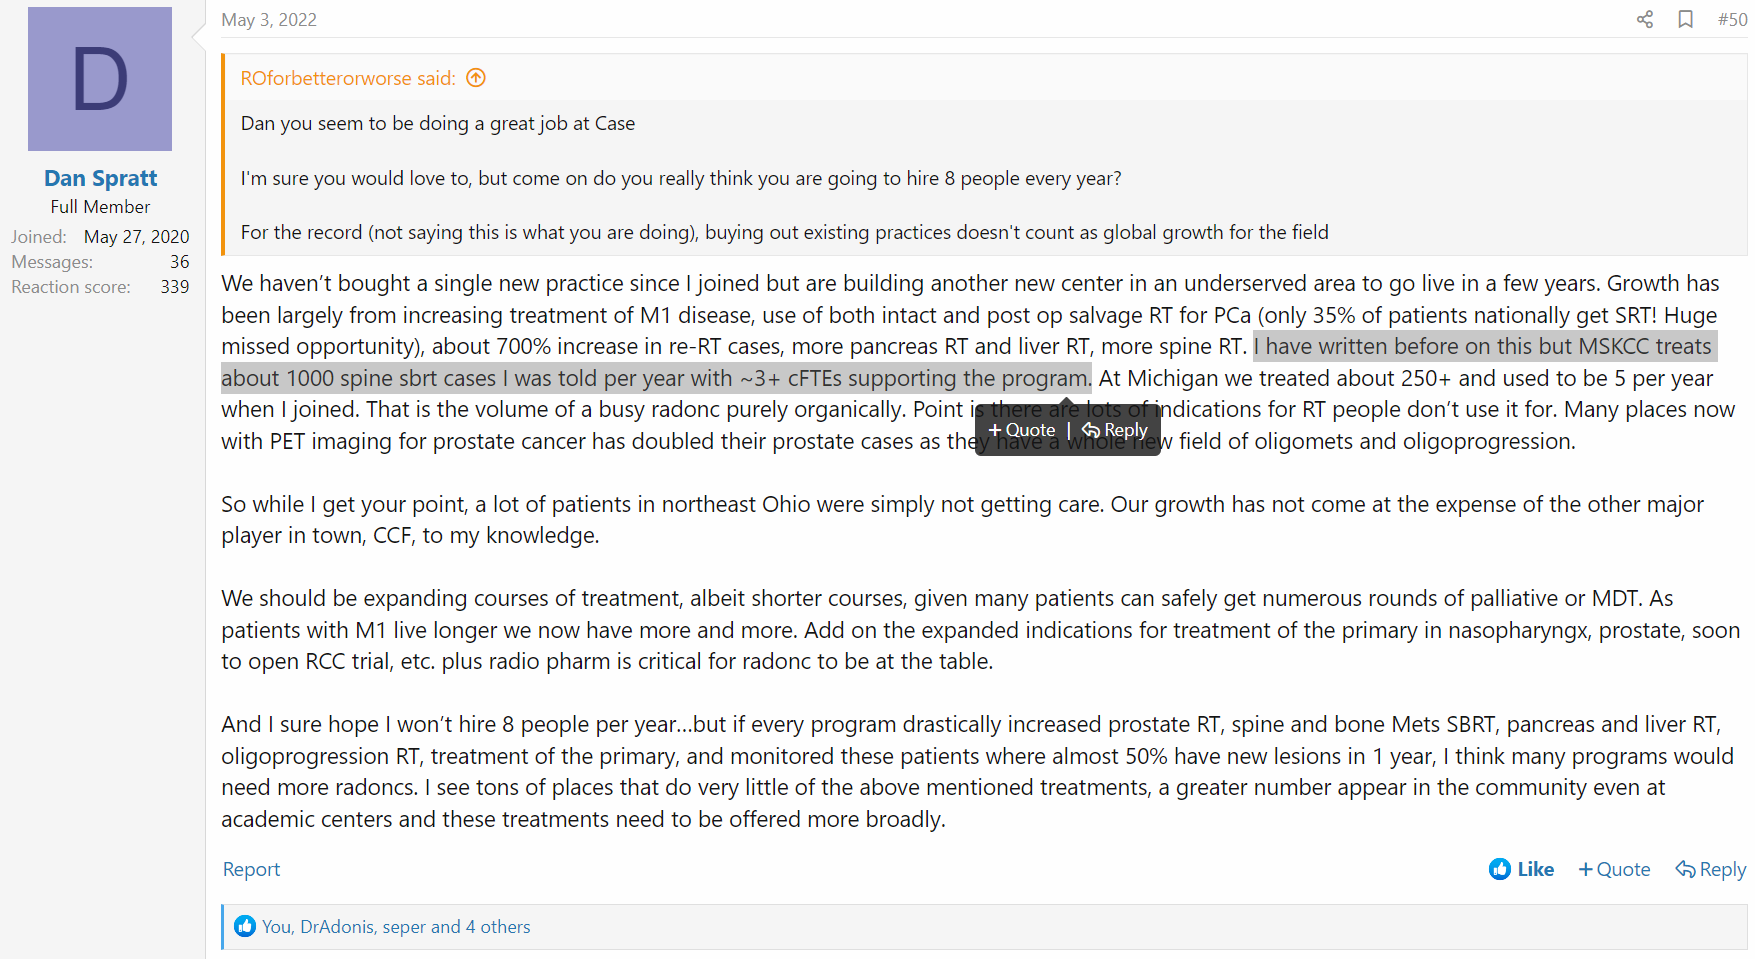
MSKCC network is doing 1000 vertebral SBRTs a year! It’s nearly 1 in 5 under beam patients in Manhattan. It sure does cost a lot to make pain go away versus cheaper options.
How are they getting that through insurance?
Also it makes me feel like a boomer that I don't SBRT every bone met. I mean I do a fair amount, but not the majority of my bone mets. Am I out of touch?
How are they getting that through insurance?
Also it makes me feel like a boomer that I don't SBRT every bone met. I mean I do a fair amount, but not the majority of my bone mets. Am I out of touch?
Nah I do tons of SBRT for all sorts of stuff but don’t pursue it often for spine mets. It’s more convenient but otherwise not so sure it’s all
That much better for pain control
Probably MSKCC itself a Great Filter. Once you’ve been accepted as a patient there, your insurance is so good/so favorable to MSKCC, they kind of get to do whatever they want.How are they getting that through insurance?
Also it makes me feel like a boomer that I don't SBRT every bone met. I mean I do a fair amount, but not the majority of my bone mets. Am I out of touch?
Advertisement - Members don't see this ad
Would say Less than 5% of my pts are sbrt candidates for bone Mets. are they giving 5-6 gy x 5 “sbrt” to femurs and illiac/sacral Mets to run up the bill.Probably MSKCC itself a Great Filter. Once you’ve been accepted as a patient there, your insurance is so good/so favorable to MSKCC, they kind of get to do whatever they want.
Last edited:

Indication is the keyword here, I would say. You can irradiate bone mets to control pain, avoid complications, fractures, etc.Also it makes me feel like a boomer that I don't SBRT every bone met. I mean I do a fair amount, but not the majority of my bone mets. Am I out of touch?
Or you can irradiate them in the context of the "oligometastasis", "oligoprogression" fairy tale. I have seen a few big cancer centers here in Europe that keep their people busy by zapping met after met to keep med oncs happy and patients on IO or whatever.
Wouldn’t surprise me if they are doing monthly surveillance imaging to catch that “oligoprogreesive” windowIndication is the keyword here, I would say. You can irradiate bone mets to control pain, avoid complications, fractures, etc.
Or you can irradiate them in the context of the "oligometastasis", "oligoprogression" fairy tale. I have seen a few big cancer centers here in Europe that keep their people busy by zapping met after met to keep med oncs happy and patients on IO or whatever.
Ralph W poisoned our field with that one offhand missive way back when in JCO. Imho.Wouldn’t surprise me if they are doing monthly surveillance imaging to catch that “oligoprogreesive” window
I treat a fair amount of oligoprogressive disease (granted, mostly lung mets). Anecdotally, it isn’t a fairy tail for some.Indication is the keyword here, I would say. You can irradiate bone mets to control pain, avoid complications, fractures, etc.
Or you can irradiate them in the context of the "oligometastasis", "oligoprogression" fairy tale. I have seen a few big cancer centers here in Europe that keep their people busy by zapping met after met to keep med oncs happy and patients on IO or whatever.
There are a couple of flavors of oligo patients who I treat
1) TKI or IO with 1-2 sites of progression in the lung (gets definitive SBRT)
2) Enlarging bulky hilar/mediastinal adenopathy as only site of progression, threatening airway/great vessels (gets dose painting 45-65 in 15fx)
3) oligopersistent disease in the lung in pt who wants to stop IO but pt/med onc or skittish unless I treat.
I am sure there are others…
Agreed, but I just find it hard to believe that there were a 1000 cases of oligoprogreesive bone disease at mskcc in one year.If I ever have oligoprogressive cancer of any type you had better bet I'm SBRTing it. I've had many success stories in my patient population. Shame that academia has done such a terribly poor job of investigating SBRT for oligomets.
If I ever have oligoprogressive cancer of any type you had better bet I'm SBRTing it. I've had many success stories in my patient population. Shame that academia has done such a terribly poor job of investigating SBRT for oligomets.
have they? many trials ongoing, multiple reported to date
and CURB trial for oligoprogression
have they? many trials ongoing, multiple reported to date
and CURB trial for oligoprogression
They're at least 5 years behind where we should be now. Non-RCTs don't count.
D
deleted1111261
Good thing did all those proton vs photon studies in the 80s-90s-00s… and so many other great studies to bolster our footprint in medicine and oncology.
They're at least 5 years behind where we should be now. Non-RCTs don't count.
They're at least 5 years behind where we should be now. Non-RCTs don't count.
Didn’t work out to well in breast cancer.
Didn’t work out to well in breast cancer.
I'm not surprised by that to be honest. I don't see very many oligoprogressive breast cancer patients. They seem to progress in a non-oligoprogressive pattern if that makes sense, with lots of extracranial mets progressing at once. I do see lots of breast cancer patients with controlled extracranial disease for which I continue to SRS brain progression over and over, so I guess that's one type of oligoprogression they do have from time to time.
Bone Mets are not a common site of oligoprogression (adrenal lung brain etc) outside of prostate ca, which is why I was surprised by the 1000 cases a year.I'm not surprised by that to be honest. I don't see very many oligoprogressive breast cancer patients. They seem to progress in a non-oligoprogressive pattern if that makes sense, with lots of extracranial mets progressing at once. I do see lots of breast cancer patients with controlled extracranial disease for which I continue to SRS brain progression over and over, so I guess that's one type of oligoprogression they do have from time to time.
Yeah I don’t know what this means.They're at least 5 years behind where we should be now. Non-RCTs don't count.
Sabr comet first started enrolling patients in 2012 meaning it was designed probably around 2010. You saying people in the early 2000s should have been pursing this? Like before we had the first trial results of sbrt for lung cancer?
Same thing true for BR001
Not really an accurate or fair criticism IMO
Absolutely fair. There is even randomized evidence with OS benefit for what you are doing, for instance that nice Chinese trial in EGFR mutated oligometastatic NSCLC.I treat a fair amount of oligoprogressive disease (granted, mostly lung mets). Anecdotally, it isn’t a fairy tail for some.
There are a couple of flavors of oligo patients who I treat
1) TKI or IO with 1-2 sites of progression in the lung (gets definitive SBRT)
2) Enlarging bulky hilar/mediastinal adenopathy as only site of progression, threatening airway/great vessels (gets dose painting 45-65 in 15fx)
3) oligopersistent disease in the lung in pt who wants to stop IO but pt/med onc or skittish unless I treat.
I am sure there are others…
On the other hand, there is a lot of unnecessary SBRTing of mets that grow a few mm, just to keep the patient on a drug.
Advertisement - Members don't see this ad
Agreed, but I just find it hard to believe that there were a 1000 cases of oligoprogreesive bone disease at mskcc in one year.
No, they are SBRT’ing instead of conventional palliative fractionation for most things according to that recent patterns of care study.
Honestly it is tough to argue against it since SBRT is either equivalent or better. But the irony is that they act like the community centers are the ones milking the cow.
Medicare PFS billing in my neck of the woods doesn't break 5 figures for a global course of SBRT... At mayo, sloane, mdacc it's mid 5 figures from what I'm hearingNo, they are SBRT’ing instead of conventional palliative fractionation for most things according to that recent patterns of care study.
Honestly it is tough to argue against it since SBRT is either equivalent or better. But the irony is that they act like the community centers are the ones milking the cow.
D
deleted1111261
Oligo Mets first written about in 1995
Stereo being used shortly afterwards
I can say in 2006 we were routinely treating Oligo Mets and although upmc was early adopter, not the first.
For it to be 2022 and how little data we have, it is sad.
Stereo being used shortly afterwards
I can say in 2006 we were routinely treating Oligo Mets and although upmc was early adopter, not the first.
For it to be 2022 and how little data we have, it is sad.
Oligo Mets first written about in 1995
Stereo being used shortly afterwards
I can say in 2006 we were routinely treating Oligo Mets and although upmc was early adopter, not the first.
For it to be 2022 and how little data we have, it is sad.
Doesn’t help that people have been doing it for that long and have bought their own hype about it. They don’t want to randomize
But this is just not IMO true at all and reflective of the fact that SDN will complain about anything
When I was bringing up oligomets and “curative”RT in 2010 for certain M1 patients I was derided, upbraided, jeered, and probably farted at by many an academic cancer center director. (ok. Not many. Just one.)Oligo Mets first written about in 1995
Stereo being used shortly afterwards
I can say in 2006 we were routinely treating Oligo Mets and although upmc was early adopter, not the first.
For it to be 2022 and how little data we have, it is sad.
They don’t jeer anymore. Times have changed; not sure the data REALLY has. The oligometastatic paradigm somehow feels related to DEI and wokeness and other “paradigm shifts.” Goes to show, medical science is as much about culture/“prevailing wisdom” as it is about science. Would rather my wagon be hitched to science.
Similar threads


- Replies
- 72
- Views
- 10K

