
Advertisement - Members don't see this ad
Her risk of bone marrow involvement is greater than the risk of IMN involvement here... so *shocker* noSo upper inner quadrant change anything for people? I suspect sentinel nodes weren't mapped?


Use all the free resources available to you from SDN: articles, guides, expert advising, forums discussions, and school research.
Her risk of bone marrow involvement is greater than the risk of IMN involvement here... so *shocker* noSo upper inner quadrant change anything for people? I suspect sentinel nodes weren't mapped?

Sounds like another win for IMRT in this space.For different reasons I was looking at this paper, which also applies here:
View attachment 354531
I think we understand a lot less than people would have us believe we do in this space, regarding what/how to irradiate, and what specific anatomical regions drive patterns of failure.
dare i ask: Is there ever a case where this isnt the case in the absence of a positive IMN biopsy?Her risk of bone marrow involvement is greater than the risk of IMN involvement here... so *shocker* no
nice comeback! 😉dare i ask: Is there ever a case where this isnt the case in the absence of a positive IMN biopsy?

20 years ago I came to SDN to learn how to get into medical school.View attachment 354570
* I don't actually believe this, but internet memes crack me up so I was feeling creative.
Ugh I have someone now that had auto recon and plastics biopsied the IMN. Shocker, it is positive. Also didn’t want chemo, and pretty sure after talking to her doesn’t want RT. Whelp, least she’s on Tam…dare i ask: Is there ever a case where this isnt the case in the absence of a positive IMN biopsy?
Don't worry about those dormant ER+ bone marrow mets. Nobody know WTF they mean or to do with them.Her risk of bone marrow involvement is greater than the risk of IMN involvement here... so *shocker* no

 www.nature.com
I think this is so provocative yet seldom talked about. The "magic" may truly be an abscopal effect. That is to say, as counterintuitive as it seems, irradiating just a percent of the subclinical/microscopic disease in a breast cancer patient's body may illicit a response in the unirradiated cells.Looking at post mastectomy BC Trial, clearly that XRT working some magic in patients who almost certainly had dormant bone marrow mets

Well, following that logic, perhaps we should stop irradiating pelvic nodes in cT3 cN0 rectal cancer. The risk of microscopic positive pelvic nodes (beyond the mesorectum) is likely lower than that of microscopic liver metastases...Her risk of bone marrow involvement is greater than the risk of IMN involvement here... so *shocker* no
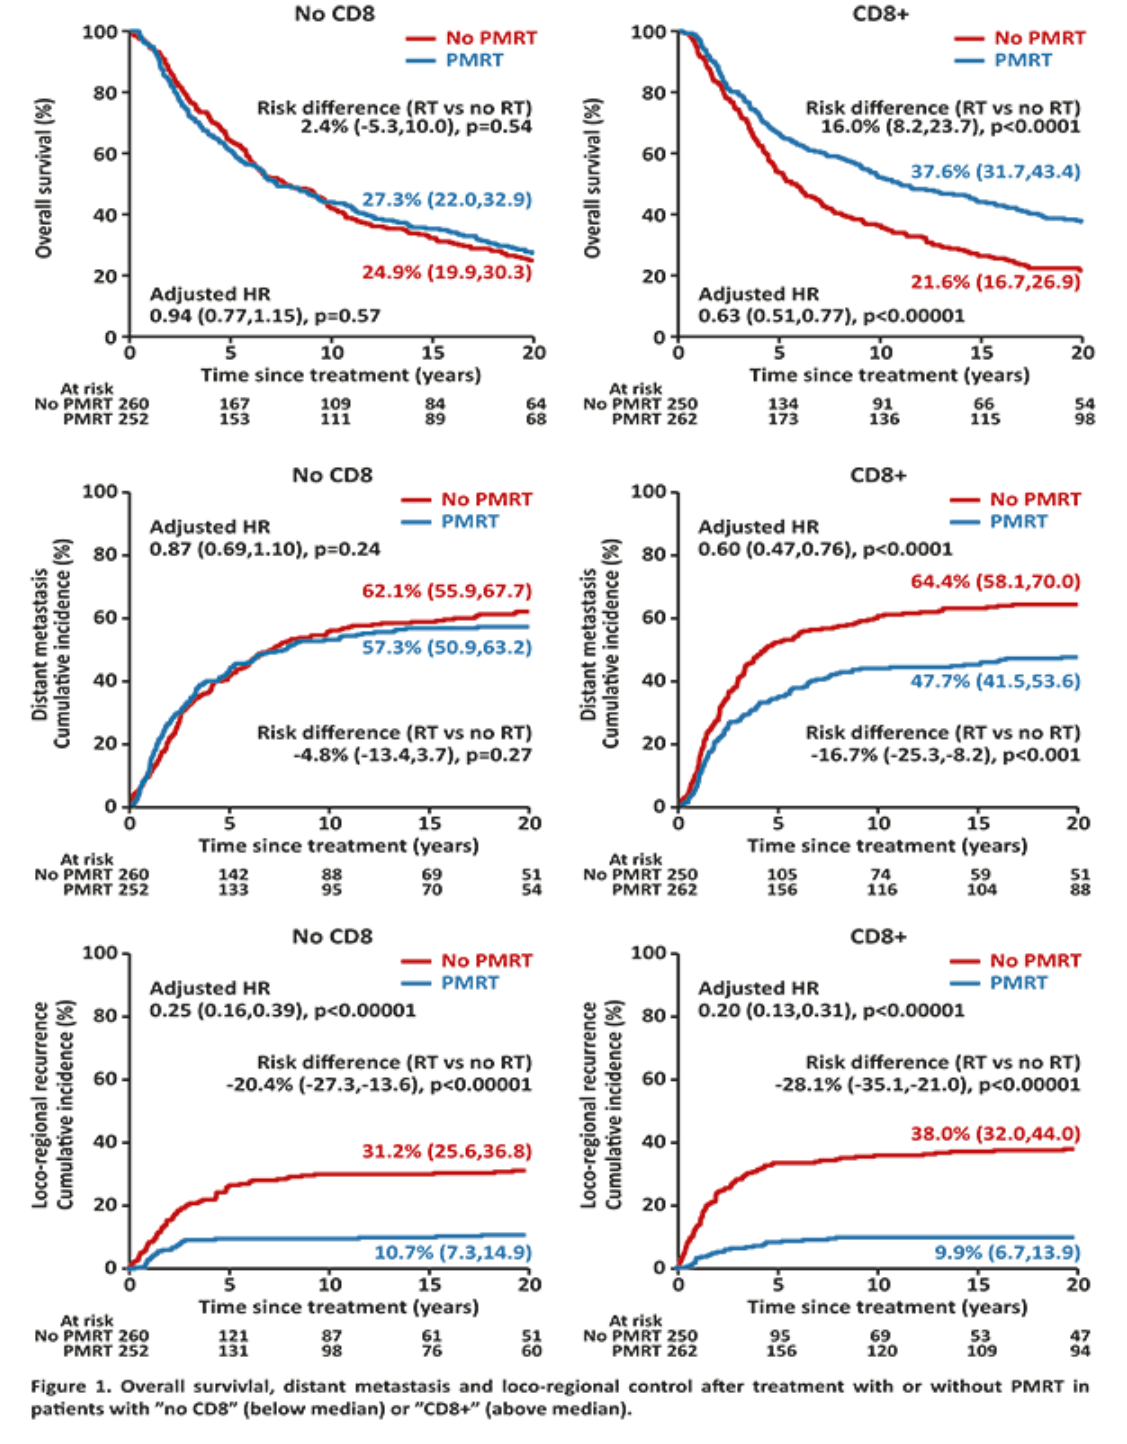
There was some interesting Danish work on CD8+ t-cells and PMRT effect at ESTRO. We have just started to breach the surface with our understanding of immunoRT effects I thinkI think this is so provocative yet seldom talked about. The "magic" may truly be an abscopal effect. That is to say, as counterintuitive as it seems, irradiating just a percent of the subclinical/microscopic disease in a breast cancer patient's body may illicit a response in the unirradiated cells.
And this explains why we will never see OS benefits from RNI machinations or differing styles thereof in most breast cancers. Locoregional therapy can be too sloppy and hurt survival, but it can be as fancy as you'd like and the returns rapidly diminish. Again confirming Fisher:
This trial had an enormous influence on how radiation oncologistssurgeonsand clinicians perceived the behavior of breast cancer; it convinced them, once and for all, that nuances in locoregional therapy were unlikely to have a substantial influence on ultimate survival and that patients succumbed to the disease not because of inattention to radiotherapeuticoperativedetail but rather because micrometastases were present at the time of the initial irradiationoperation. This provided the biologic rationale for the evolution of clinical trials that evaluated not only additional reduction in the extent of locoregional therapy, but also, more importantly, the use of adjuvant systemic therapy.
There was some interesting Danish work on CD8+ t-cells and PMRT effect at ESTRO. We have just started to breach the surface with our understanding of immunoRT effects I think
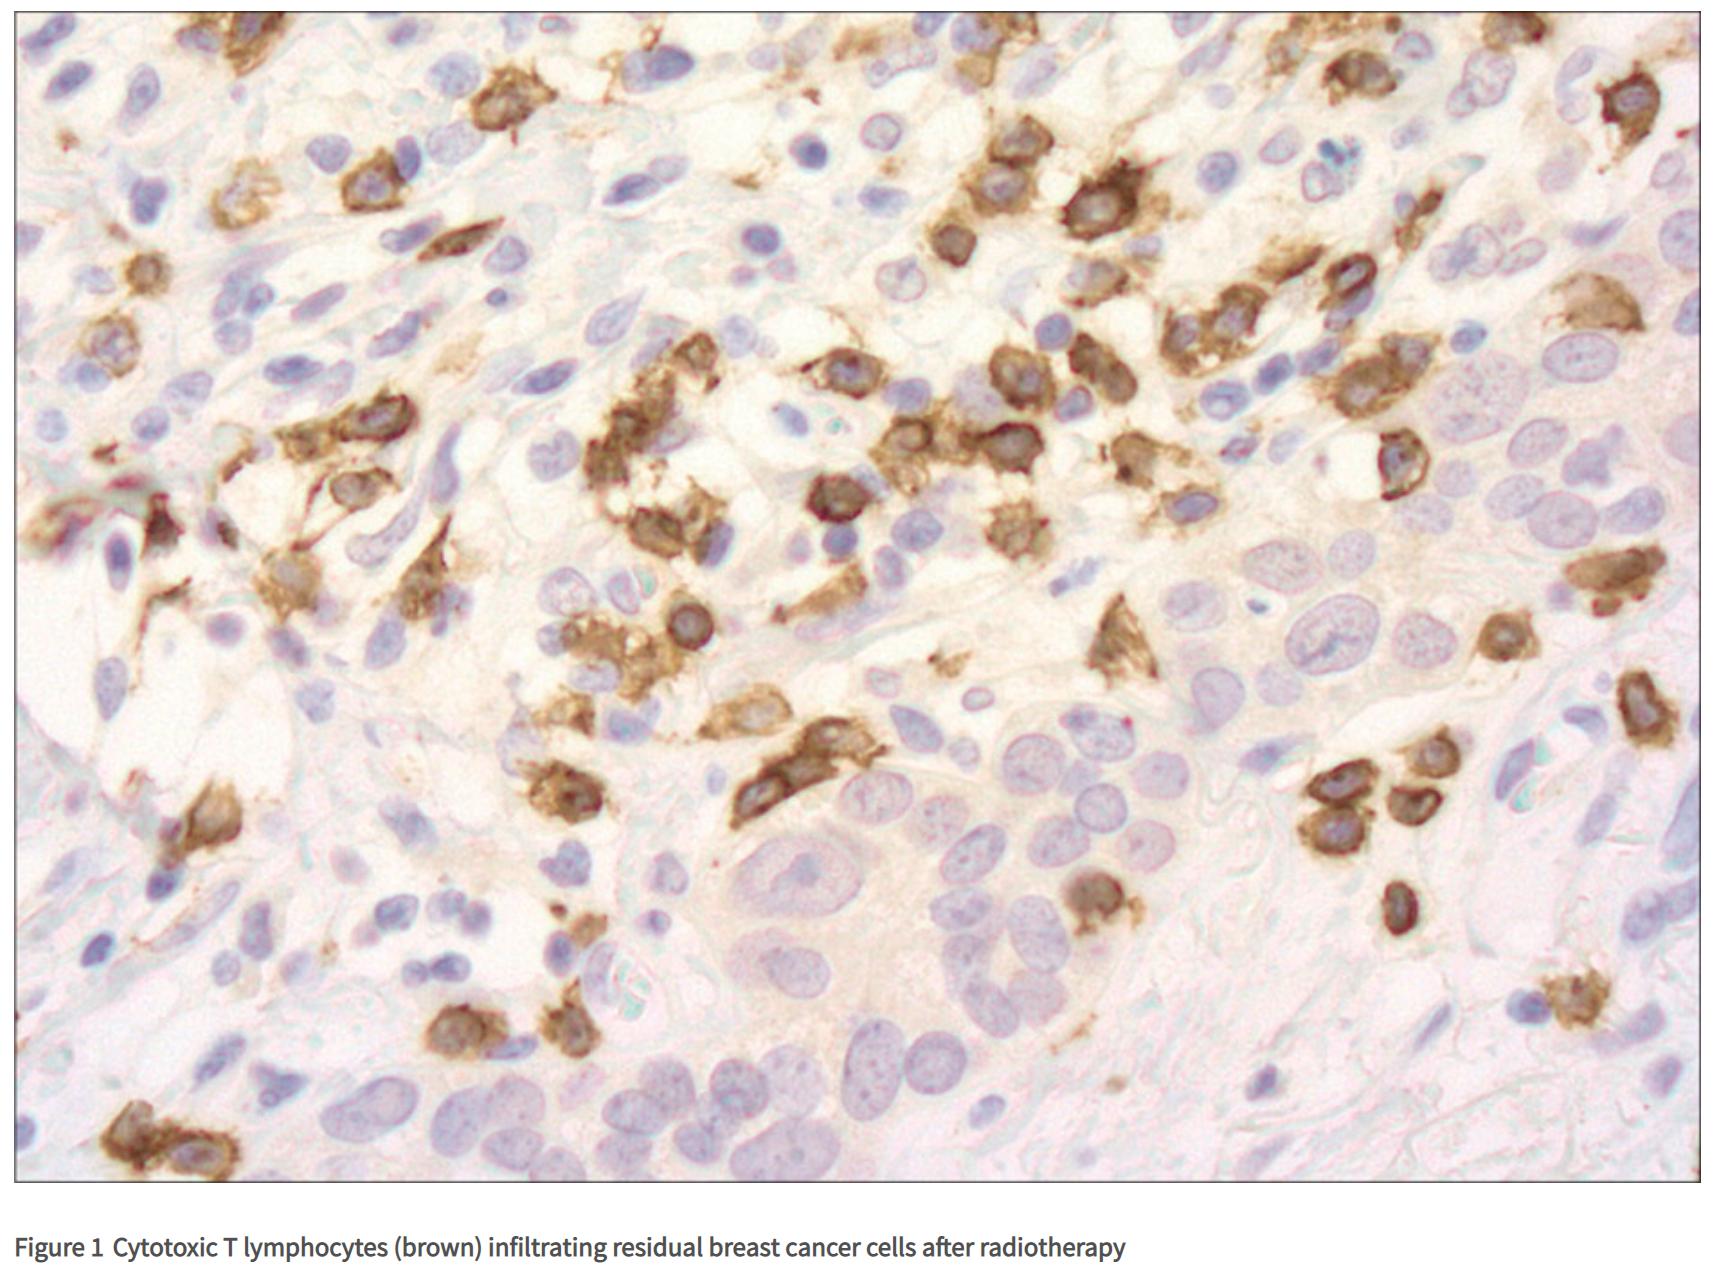
Here you go. VERY cool results IMHO and I have considered this for a long time thanks to Formenti. Now, it will actually mean (if we base PMRT on CD8+ findings) a little less PMRT utilization, but such is life! The stratification for PMRT effect seems to be more pronounced for CD8+ status than it does for LN status; keep in mind EORTC 22922/MA20 showed no OS benefit to RNI, yet here we have a near doubling of OS using PMRT based on CD8+ at 20y with a p<0.00001. (NB: CD8+ cells are cytotoxic T cells if you recall from med school immuno.)There was some interesting Danish work on CD8+ t-cells and PMRT effect at ESTRO. We have just started to breach the surface with our understanding of immunoRT effects I think
40/15For those of you doing chest wall only for +sm, are you treating the primary plan to 40/15 or 50/25?


I hear from colleagues that once you start doing your three field breasts with hypofrac you just simply never go back.

For those of you doing chest wall only for +sm, are you treating the primary plan to 40/15 or 50/25?
I hear from colleagues that once you start doing your three field breasts with hypofrac you just simply never go back.

Our mission is to provide students with free, unbiased information, resources, and advising for careers in the health professions. We believe every student deserves access to trustworthy guidance, regardless of background or ability to pay.


