

-
CycleTrack and SDN are teaming up to make medical school admissions more transparent and accessible! Read the announcement to learn how we’re supporting the future of CycleTrack’s free application-tracking tools .
You are using an out of date browser. It may not display this or other websites correctly.
You should upgrade or use an alternative browser.
You should upgrade or use an alternative browser.
Pictures of the Week
Started by Epidural

Get help with your application
Use all the free resources available to you from SDN: articles, guides, expert advising, forums discussions, and school research.


So folks, what are we looking at here?

So folks, what are we looking at here?
DISH?
Advertisement - Members don't see this ad
Nope.
C1-4 congenital block vertebrae with marked DDD.
I figured it was something else. Didn't scream DISH but didn't look like DDD only. Thanks for posting.


Saw today a X-ray photo of a one year old girl who swallowed a sewing pin.

New patient. Axial neck pain, slow onset, possibly fall from horseback as a kid. No radiating arm pain or neuro deficit. Noticing some difficulty swallowing and "if I put on finger just here on my throat, it's hard to breath."View attachment 198871
http://radiopaedia.org/articles/diffuse-idiopathic-skeletal-hyperostosis
Forestier's Disease. Check an HLA-B27. Consult spine surgeon and see if Rheum has any Biologics if HLA+.

Radiology report says moderate medial joint space loss.


Referral for L4 fracture either malignancy or osteoporosis. Pedicles were already taken, so I had to go really slow to avoid the exiting root. Patient kept mostly awake to make sure I could dock in the vertebral body. Didn't go bad, just more stress getting in.
70m 3 weeks moderate back and right L4 distribution parasthesias with "foot slap" after shoveling snow. Tib ant 2/5. Knee extension/quad weak at 4/5 manually, but unable to rise from single leg squat. Bowel/bladder fine. Biggest disc I've seen with cephalad/caudal migration. Lami/microdisc following day after expedited surgery consult...
Sent from my iPhone using SDN mobile app
View attachment 200650
View attachment 200651
70m 3 weeks moderate back and right L4 distribution parasthesias with "foot slap" after shoveling snow. Tib ant 2/5. Knee extension/quad weak at 4/5 manually, but unable to rise from single leg squat. Bowel/bladder fine. Biggest disc I've seen with cephalad/caudal migration. Lami/microdisc following day after expedited surgery consult...
Sent from my iPhone using SDN mobile app
whats the rush? damage already done. central canal huge, no cauda equina. his foot will keep slapping. outcome (strength)would be the same with or with surgery.
if the foot slapping gets worse, then yes, surgery. but it wont
if this was pain-free, id just do PT
if there was pain, right L4 TFESI.
dont let the size of the disc scare you.
Thank you for input. I admit the size of disc played a role, but really the degree of weakness pushed me to surgery consult ASAP. What patient called foot slap I called frank foot drop with inability to clear/dorsiflex on gait and less than anti-gravity Tib ant. You sit on that if its your back? I have a hard time sitting on anything less then 3/5 motor.
Sent from my iPhone using SDN mobile app
Advertisement - Members don't see this ad
Overdevest et al found two risk factors for poor motor recovery after radic due to disc herniation were 1) severe weakness (authors deemed 3/5 "severe") and 2) size of herniation that took up 25% or more of canal. I'd send that person to spine surgeon to at least allow patient to have the option of surgery.
Thank you for input. I admit the size of disc played a role, but really the degree of weakness pushed me to surgery consult ASAP. What patient called foot slap I called frank foot drop with inability to clear/dorsiflex on gait and less than anti-gravity Tib ant. You sit on that if its your back? I have a hard time sitting on anything less then 3/5 motor.
Sent from my iPhone using SDN mobile app
yes.
without a doubt.
that disc will resorb, and the motor recovery will be the same with or without surgery.
there is no wrong answer here. if this patient has surgery, that is fine. non-operative treatment is also fine.
if pain leg pain cannot be resolved with non-operative measures, or there is progressive motor loss, then i am all for a discectomy
Overdevest et al found two risk factors for poor motor recovery after radic due to disc herniation were 1) severe weakness (authors deemed 3/5 "severe") and 2) size of herniation that took up 25% or more of canal. I'd send that person to spine surgeon to at least allow patient to have the option of surgery.
http://www.ncbi.nlm.nih.gov/pubmed/12131740
Nice to have MRI compatible leads.
If you breach medial pedicle on the kypho you will have a lead revision case in a few weeks. Prolia yet?
I'm not sure if I'm going to do a kypho at this point. Agree I have to change him from the Fosamax though.
Another huge disc. Largest cervical hnp I've seen in my short career. 2 weeks of worsening right c6 radic pain, progressive weakness, mild balance deficit, new Hoffmanns on right and brisk reflexes....


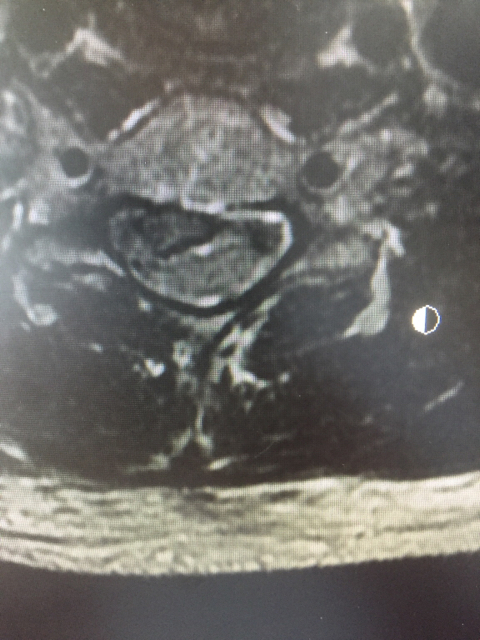
Sent from my iPhone using SDN mobile app
Sent from my iPhone using SDN mobile app
can i ask - do you guys get "approval" from patients before posting? i obviously do not see identifying markers, so it appears HIPAA compliant, but all the same....
can i ask - do you guys get "approval" from patients before posting? i obviously do not see identifying markers, so it appears HIPAA compliant, but all the same....
No, deidentified info. No face, no tatoo, no ID of person possible. Otherwise need their consent.
My informed consent document states:
I consent to the taking and publication of any photographs in the course of this operation for documentation or for advancing medical education.
I still anonymize before using.
I consent to the taking and publication of any photographs in the course of this operation for documentation or for advancing medical education.
I still anonymize before using.
I didn't see where the contrast went under lateral.... went to clo and injected under live again...

Sent from my iPhone using SDN mobile app
Sent from my iPhone using SDN mobile app
Bored. One of my kyphos from last week. 80+ yr old was stuck in bed or chair. T8 got way worse between CT and procedure date.


Had a good AP showing cross fill, but contrast on software makes it all look the same.


Had a good AP showing cross fill, but contrast on software makes it all look the same.
86 y.o. with axial LBP.
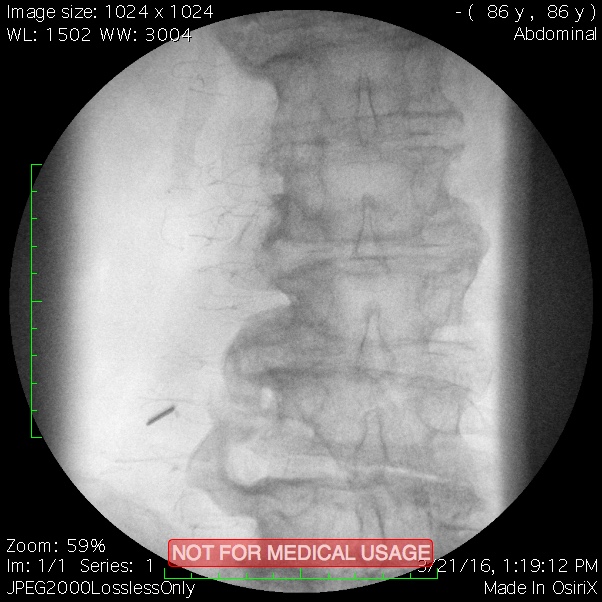
86 y.o. with axial LBP.
View attachment 201526
Some of sort of seronegative spondyloarthropathy, maybe psoriatic in nature?
Some of sort of seronegative spondyloarthropathy, maybe psoriatic in nature?
nope. he's just old. maybe DISH
Advertisement - Members don't see this ad
nope. he's just old. maybe DISH
Agreed, just some good ol ancient spine.... and my avg RFA patient.
Sent from my iPhone using SDN mobile app
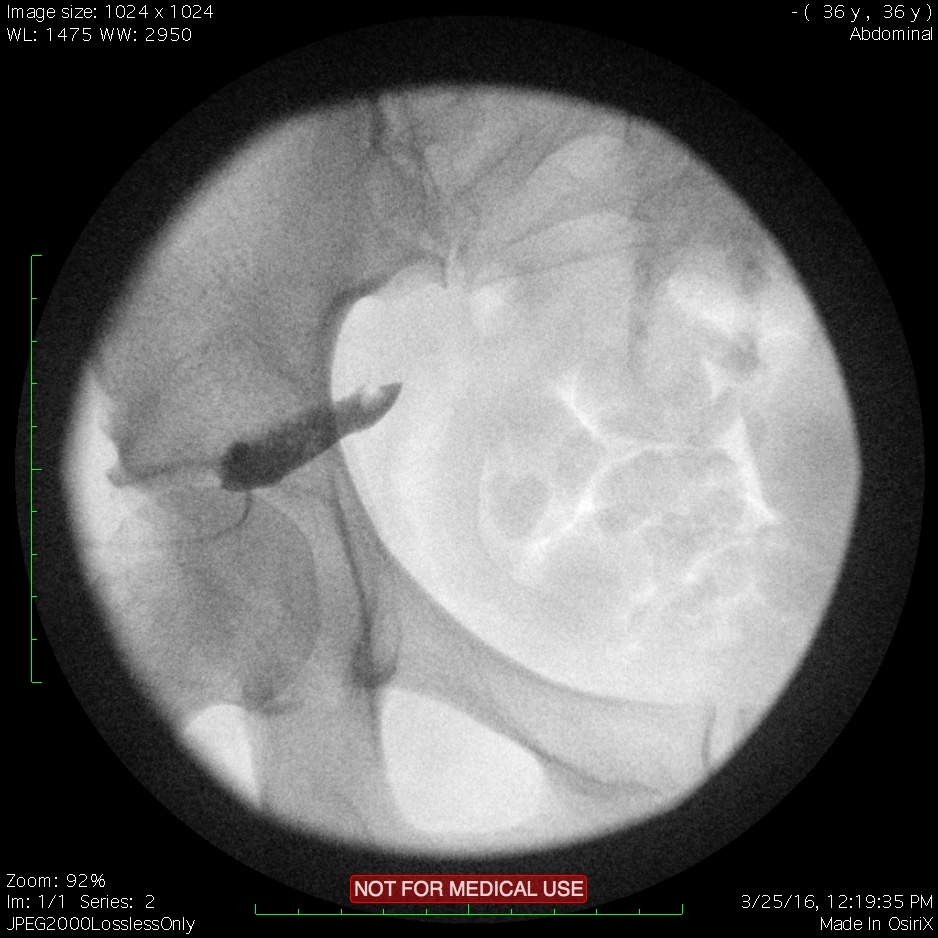
I have like this technique for piriformis injections and thought I would post pictures:
http://www.painphysicianjournal.com/current/pdf?article=OTk0&journal=43

http://www.painphysicianjournal.com/current/pdf?article=OTk0&journal=43
I have like this technique for piriformis injections and thought I would post pictures:
http://www.painphysicianjournal.com/current/pdf?article=OTk0&journal=43
View attachment 201765 View attachment 201766
That's my go to technique. I like having a bony endpoint and get very reliable spread. 2:30/9:30 on acetabulum, verify looks in line of where muscle expected to course.
Sent from my iPhone using SDN mobile app
Sent to me today on film, will see Thursday. T12 looks too liquid to be bone. 90 yr old, s/p fall.


From my office to the ER then OR today......
Hey doc is it normal that I can't feel anything in my crotch....


Sent from my iPhone using SDN mobile app
Hey doc is it normal that I can't feel anything in my crotch....
Sent from my iPhone using SDN mobile app
Last edited:
From my office to the ER then OR today......
View attachment 202462
View attachment 202463
Looks like a fingerprint smudge obscuring the left hemicanal on axial. Guess it's no artifact.
Sent from my iPhone using SDN mobile app
Do I go CESI or MBB first?


Do I go CESI or MBB first?
What are the symptoms and exam findings?
I would start with a blood patch and follow that with a disco.
Right arm weakness. No leg symptoms. No breathing problems.

Do I go CESI or MBB first?
Neither. Cervical SCS obviously with an occipital nerve stim. Follow up with stem cells, ketamine infusion and decompression table with your in house chiropractor. After that, they'll be good as new.
Def need to aspirate thatNeither. Cervical SCS obviously with an occipital nerve stim. Follow up with stem cells, ketamine infusion and decompression table with your in house chiropractor. After that, they'll be good as new.
Right arm weakness. No leg symptoms. No breathing problems.
Neck flexor weakness?
Neck flexor weakness?
Yes.

Hairline Fx, might need CT to see it.
Advertisement - Members don't see this ad
Hairline Fx, might need CT to see it.
Suggestive of, clinical correlation suggested...

U
Undescended testes?
Would you rather?
1. Have 2cc cement floating in front of your spine?
or
2. Have a cement straw coming 1cm out of your pedicle?
Similar threads


- Replies
- 29
- Views
- 1K

- Replies
- 33
- Views
- 2K
- Replies
- 30
- Views
- 5K
