SCS trial antibiotics?

Started by Baron S
This forum made possible through the generous support of SDN members, donors, and sponsors. Thank you.
Get help with your application

Use all the free resources available to you from SDN: articles, guides, expert advising, forums discussions, and school research.

Advertisement - Members don't see this ad
you got it backwards.
I don't think so. The data matters, but the recs are pretty conservative in both cases, so it's a wash between trial and implant there.

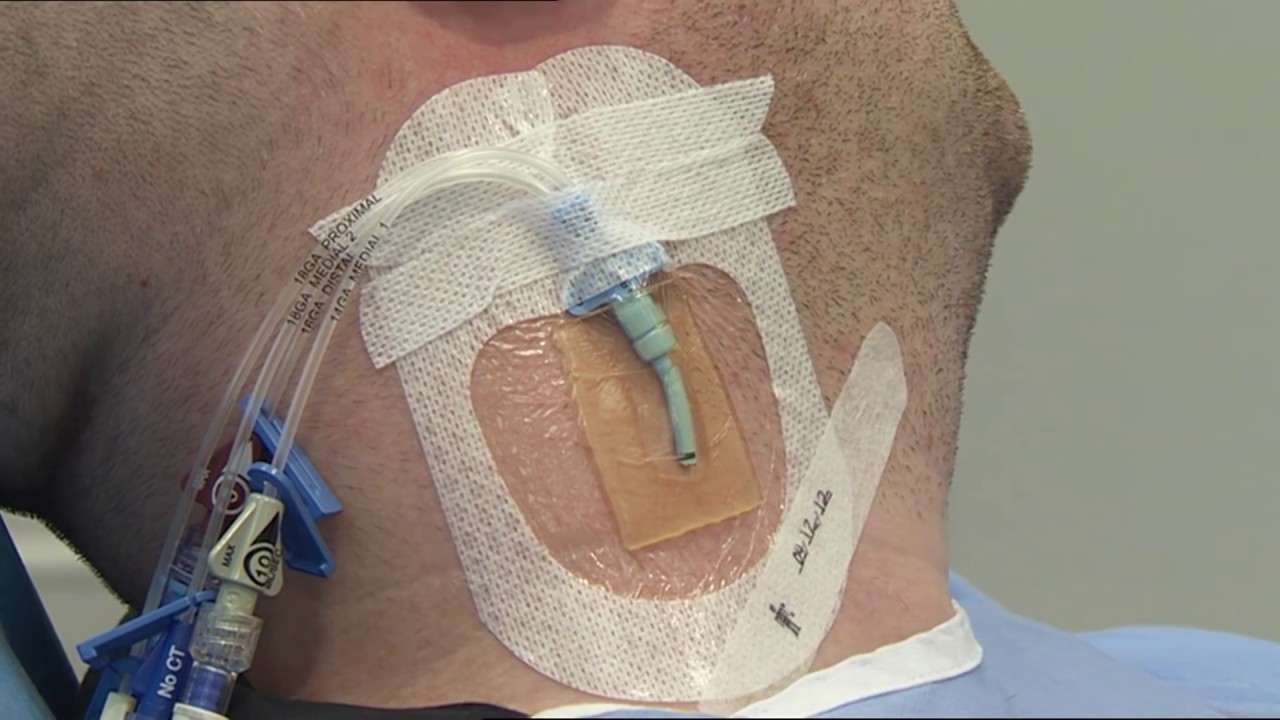
From a face validity standpoint, in a trial, a sterile lead going through skin and, admittedly, sticking out, which was sterilized and prepped then covered with tegaderm, is a low infection environment. It remains a relatively closed system in a good way, and there's in theory not that much opportunity for biofilm to develop and track infectious material up the leads.

In an implant, you have a midline and flank incision which was exposed to OR air, mucked around with fingers and instruments, and then sealed up, creating a closed system in a bad way. There is plenty of opportunity for biofilm to form, seroma formation and possible static fluid, and a larger length of incision (compared to puncture) in an implant.

The potential harms of infection in an implant are severe infection sequelae, harms of re-operation for hardware removal, loss of therapy, and need for resurgery to reimplant. Postop abx for implant makes way more sense at every level compared to trial.

IIRC surgical literature implies that most gram positive bacterial ingress happens at the time of incision (or second incision, something like that).
 
I see where you are coming from, but antibiotics do not work that way.

If contamination tracks along the externalized hardware, there is no amount of Keflex that is going to reliably prevent an infection. Generally speaking, seeded hardware does not get salvaged with systemic antibiotics.

I think the concept of pre-op antibiotics is being confused with some magical property that Keflex simply does not have. Pre-op prophylaxis is about having adequate tissue levels at the time of bacterial inoculation. It is not a sterility shield for several days of externalized hardware sitting under a dressing in the real world.

The retrospective implant paper and a case report do not really strengthen the argument. At best, they show infection can happen

Completely agree with the length of trial associated with higher risk
if the keflex reduces bacterial load at the implantation site, the incidence of seeding may be reduced to the point that it does not cause significant abscess formation.

at least that is the concept, and the one article suggested that post op antibiotics do reduce incidence of infection.
 
Advertisement - Members don't see this ad
I agree that PO or IM or IV antibiotics pre-operatively should be given in an adequate time frame to get tissue levels.

The majority of the guidance/literature about this is from SCIP which is more for incisional/implantable stuff.

I think Pope et al had a paper around 2021 about how in neuromodulation specific implant cases, continuing oral antibiotics after a case reduced the infectious rate, but I still would rather save my 1st line antibiotics for when I know there's a problem, rather than chase a problem with less optimal or more aggressive guns.

I do think dressings have improved a lot. My most recent health system had just gotten the CHG tegaderms which I felt were the best dressings for my trials.

maxresdefault.jpg


I do routinely go longer on trials into the 7-14 days range and am unaware of any deep infections. Most commonly some skin irritation at the site. I should remind people that that the new ASRA infection control guidelines suggest we should be gowning/full barrier drapes/OR style for anything that is meant to stay in for over 5 days, so I assume we'll all do 4.5 day trials from now on.

As I transition into the community, I think I would lean towards covering with Iodophor- or CHG- impregnated incise drape to hold the leads in place under whatever tape they can tolerate.

I use Ioban over trial leads. No PO abx.
4-5 day trials.
Infections = 0
 
Lick it and stick it.
1000 infections.
I doubt it. My saliva's pristine.

And seriously, when you look at it, the body has an immune system that works. Like they do Moh's surgeries, infection risk with sterile vs boxed gloves is the same. Make it even scarier and look at the incidence of infection in battlefield penetrating wounds, oddly enough only about 25%.

Still, don't lick it and stick it unless it's organic and you're doing it through a mask.