
Advertisement - Members don't see this ad
This thread definitely deserves a bump. Great work!
this thread just makes me sad that Dr. Fraud is gone. I miss his random skewed, and occasionally contradictory, arguments. They made the day exciting.


Use all the free resources available to you from SDN: articles, guides, expert advising, forums discussions, and school research.
This thread definitely deserves a bump. Great work!

Maybe he's still here lurking, waiting to rise up from the ashes under a new handle.this thread just makes me sad that Dr. Fraud is gone. I miss his random skewed, and occasionally contradictory, arguments. They made the day exciting.


That was my thought as well... But I really don't remember him, and am not sure why he was banned
With a name like Dr. Fraud, its just a matter of time. A pretty good troll name imo


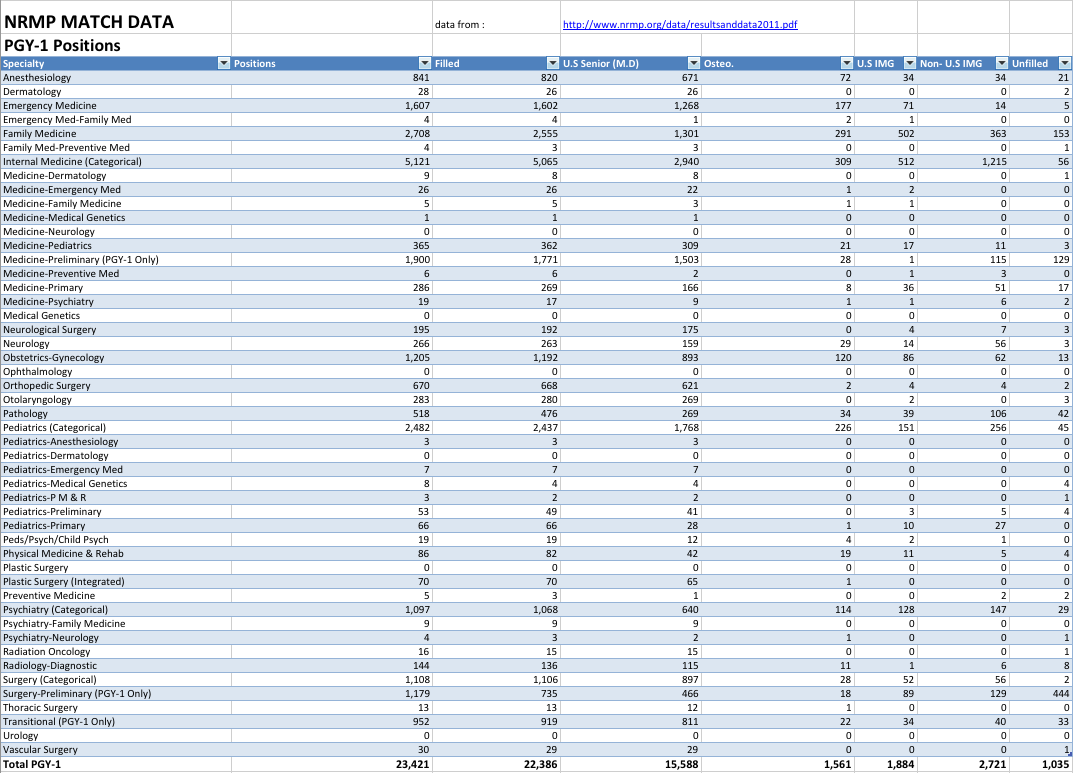
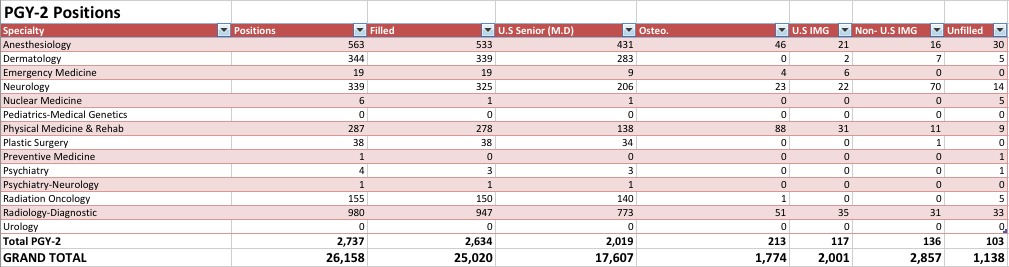
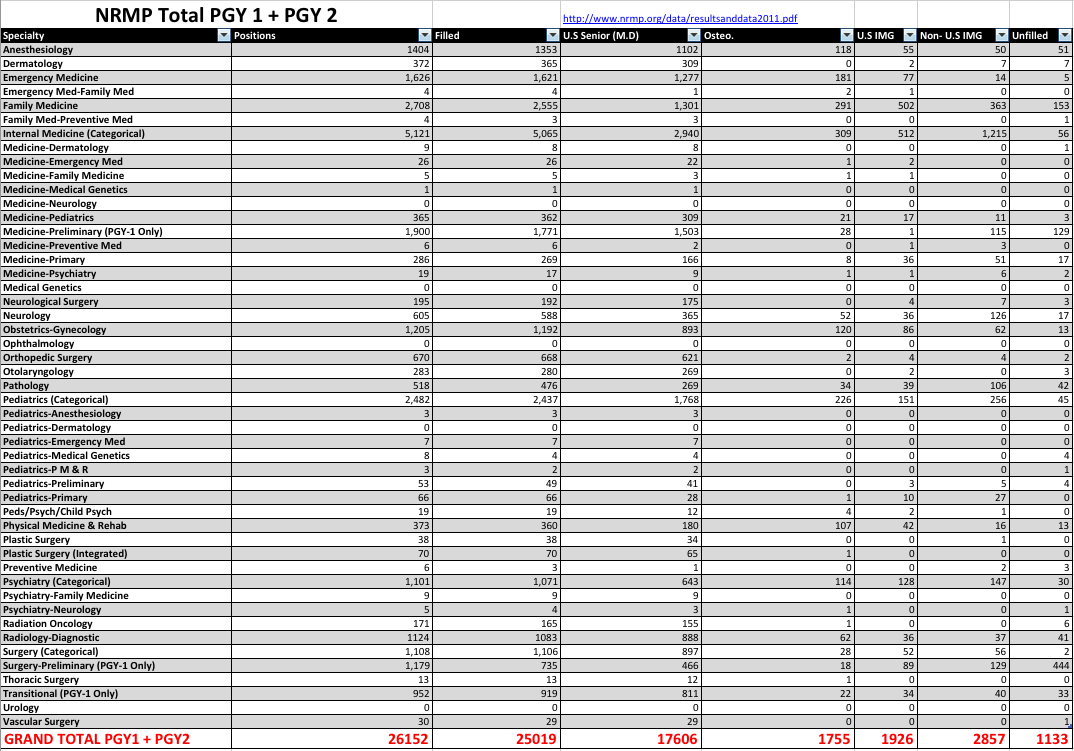
Just updated the spreadsheet with 2011 NRMP data so that it's as up to date as possible. Check my first post for the download.
Enjoy!

EDIT: Updated to include 2011 NRMP data (2/9/12)
EDIT: well, schucks. I spoke too soon. It's all updated now, DrHockey (4/18/11)
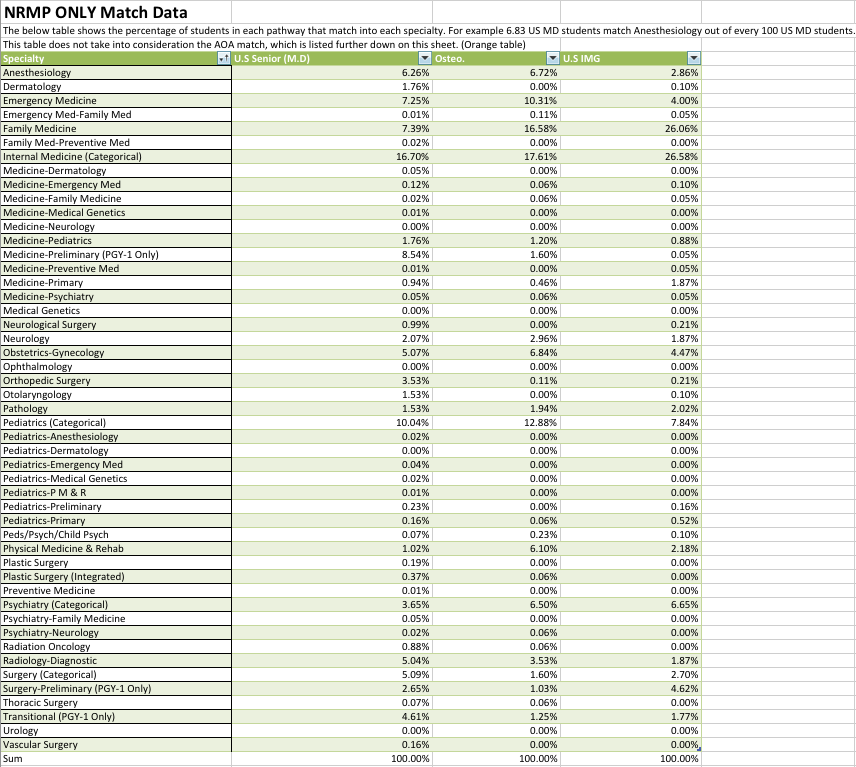
Since we're all too lazy to click, I went ahead and took screencaps of the relevant ones. NOTE: I'm not updating this if any info changes, so take it for what it's worth.
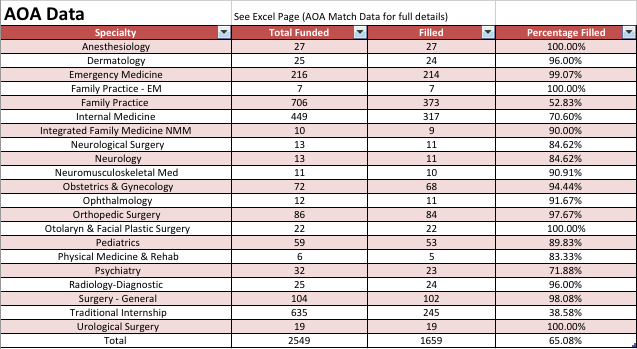
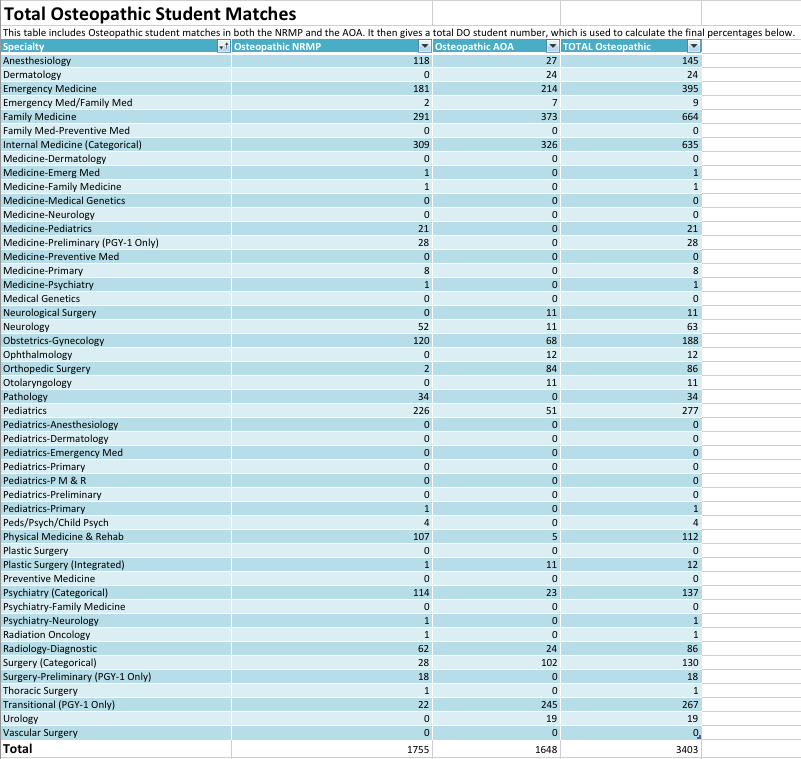
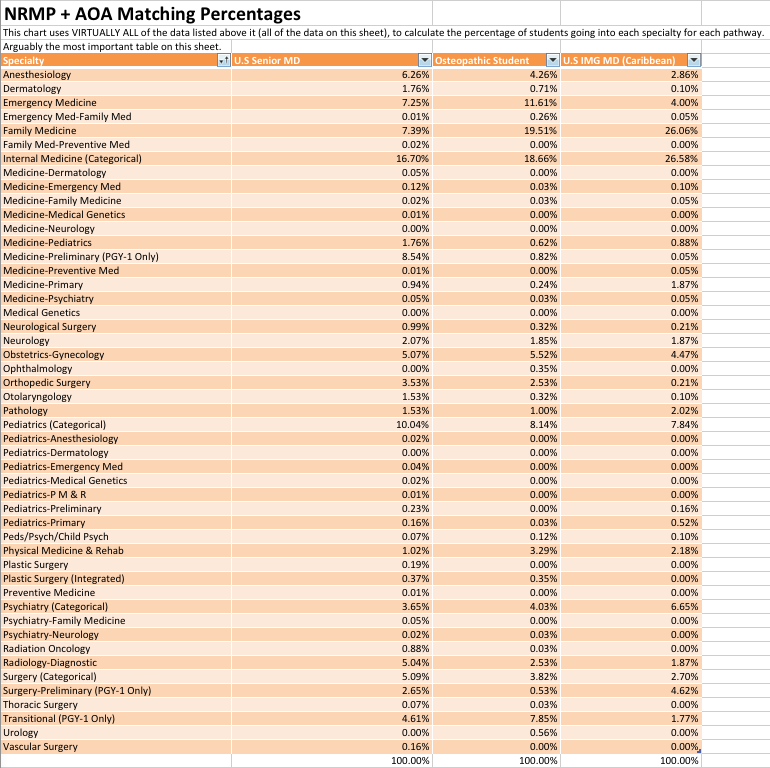
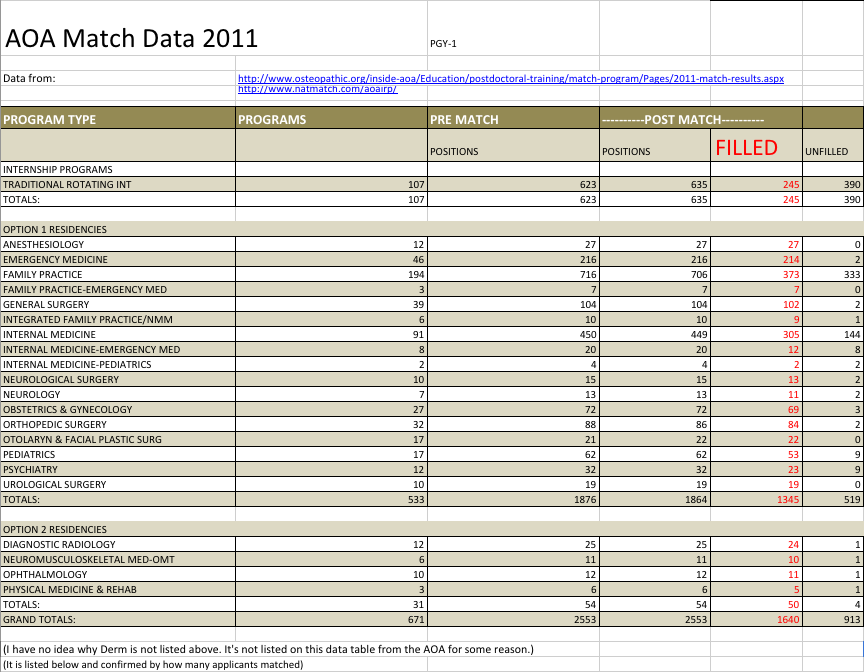
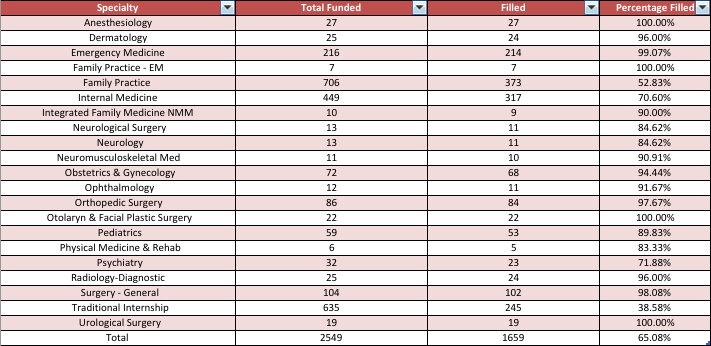

HockeyDr, you are truly amazing. Lol
HockeyDr you're the man! Thank you!
Not everyone wants to go into FP with debts in the 300k's
is this really a substantial reason for empty positions?
if they're empty why won't they take caribbean folk?
I see some interesting stuff....if I'm reading the spreadsheet right 😕
0% MD got into Urology, while 0.56% DO did.
0% MD got into Ophthalmology, while 0.35% DO did.
😱😱😱
.

I see some interesting stuff....if I'm reading the spreadsheet right 😕
0% MD got into Urology, while 0.56% DO did.
0% MD got into Ophthalmology, while 0.35% DO did.
😱😱😱
1. Only DOs can apply for AOA residencies.
2. The quality of applicants were poor enough that the PDs would rather have their slots go unfilled.
oh that just a glitch because of how the data was collected. The NRMP (nor the NMS/AOA) match urology or ophtho. They both match in their own independent match programs. The NRMP just doesnt stop listing them since they assume one day they will run the match for these (which is exactly what happened with neurosurgery, which used to be 100% its own match). The way the .56 came about is likely measuring the number of DOs matching into these specialty matches. I think its ~2 DOs per year into a AUA urology program. (and 18-19 into AOA programs)
oh that just a glitch because of how the data was collected. The NRMP (nor the NMS/AOA) match urology or ophtho. They both match in their own independent match programs. The NRMP just doesnt stop listing them since they assume one day they will run the match for these (which is exactly what happened with neurosurgery, which used to be 100% its own match). The way the .56 came about is likely measuring the number of DOs matching into these specialty matches. I think its ~2 DOs per year into a AUA urology program. (and 18-19 into AOA programs)
For a premed you are way too opinionated about your future colleagues and about things that you know very little about! Just wait until you start medical school where you will consider yourself lucky to be in the middle of your class. Every premed on SDN thinks they are the s*** and about half way into the 1st month of medical school they'll realize that they are not that much smarter than their colleagues.
There are many reasons programs go unfilled and quality of applicant is not one of the top reasons. Any program would rather get the worst applicant than go unfilled at the end because interns/residents = funding from the federal government (close to $100K per trainee in addition to their salaries/benefits).
Also, there are some applicants who choose not to do FM even if that means waiting an extra year and there are few who decide not to pursue a career in medicine after medical school.
ah, that makes more sense 👍
eh..so you're saying on the ACGME side, the PDs of these unfilled FM programs couldn't find any desperate IMG/FMG at all to fill? Really now? Quality of applicant doesn't start to weigh in a bit more here?
FYI, my first point was referring to unfilled AOA slots (which IMG/FMG can't apply to), while my second point was referring to unfilled ACGME slots.

Do you by any chance have data on the average stats of people who failed to get into certain DO residencies? Like for example 29 people got into DO Derm, with XXX Comlex, average people who failed to get into DO Derm with YYY Comlex as well as the amount of people who failed to get into that residency and total who applied.

Do you by any chance have data on the average stats of people who failed to get into certain DO residencies? Like for example 29 people got into DO Derm, with XXX Comlex, average people who failed to get into DO Derm with YYY Comlex as well as the amount of people who failed to get into that residency and total who applied.
Derm #'s aren't on there because of how the match works I think. All the other ones should be though

My philosphy on that one was always that we do everything in their curriculum and then some 🙂Just curious..why are DO's allowed to go into MD spots? However, MD's can't go into DO spots?
My philosphy on that one was always that we do everything in their curriculum and then some 🙂
I don't actually know a lot about the residency programs...however, it has been my understanding that AOA residency programs are typically going to have an OMM type component incorporated into it. That may just be occasional CME type things, but it would be hard to place someone in that situation with zero OMM experience. Two years of OMM in school could very well be condensed down for MDs if they wanted to make it a viable option. However, let's be honest....with the stigma still in existence between the two career paths, how many MDs are going to apply for DO residencies anyway?? I mean, this is coming from me, as a very proud DO student lol.
Anyone has else more perspective on this? Maybe there's a more policially based type reason for this...
Just curious..why are DO's allowed to go into MD spots? However, MD's can't go into DO spots?
For as much as I'm on here, I never see this one being asked....not sure how I miss it honestly 🙂 I was also unaware about the 4 wk thing...why would that be a policy if MDs can't apply? DO students get 2 years worth as a standard, right? Sorry, I think I might be misunderstanding your post...To complete a DO residency you must complete a DO internship which requires at least 4 weeks of formal OMM rotation (regardless of specialty). Also some MD students would kill to have access to some of our ROAD/surgical specialties.
However, these question are usually asked by trolls... This question is asked and answered on average about once every other week with increased frequency during this time of the year. The best is to just ignore them.
There's that political reason I was looking for lol....this makes sense.The answer is quite simple.
The AOA will recognize training for DOs done at either ACGME or AOA programs.
The ACGME will only recognize training for MDs done at ACGME programs, not AOA programs. An MD is not "allowed" to go into an AOA program simply because it wouldn't make sense at all. Why complete post-graduate residency training at a program that won't be recognized? If the ACGME ever changes its stance then MDs could potentially apply to DO programs.
For as much as I'm on here, I never see this one being asked....not sure how I miss it honestly 🙂 I was also unaware about the 4 wk thing...why would that be a policy if MDs can't apply? DO students get 2 years worth as a standard, right? Sorry, I think I might be misunderstanding your post...
There's that political reason I was looking for lol....this makes sense.
Pretty sure that there is either no OMM rotation reqirement or that it is state-specific. I looked up the differences between acgme and aoa interns in dual accredited programs. The differences are (besides obvious different tests) 1. Required aoa membership. 2. An EM month (for aoa only) 3. A OMM clinic (which simply requires that you document an Osteopathic structural exam, not any treatment) and 4. At least 12 hours of OMM education per year. That's hours.
I can promise you no one at the two DO training sites knows any OMM unless they keep it up themselves. If only filling out a structural exam once per patient (not per visit, pet chart) counts, and it does, that's some huge corner cutting to allow when others go and do a full on month. It would take a few hours to teach an md to palpate a spine and diagnose just the spine if no treatment, just diagnosis, is required.
I don't know what your point is but those are the rules. If programs cut corners, you (or the interns/residents) should report them to the AOA as their education is being compromised.
their education is being compromised.

I can promise you no one at the two DO training sites knows any OMM unless they keep it up themselves. If only filling out a structural exam once per patient (not per visit, pet chart) counts, and it does, that's some huge corner cutting to allow when others go and do a full on month. It would take a few hours to teach an md to palpate a spine and diagnose just the spine if no treatment, just diagnosis, is required.
No. That's accepted amounts of omm activity was my point. The hospital was actually just audited by aoa in October. 12 hours of OMM lecture and filling out structural evaluation of yhr spine once per patient is all that is required.
I was simply noting that the unique "DO specific" requirements are remarkably minimal. I'm sure many programs go beyond that, but I also know 2 for 2 of the do sites I know do the minimum, and one of them was just audited and passed fine. Nothing had to change.
It's sad really..all those somatic dysfunctions falling through the cracks.
GraceEuphoria you see now how these arguments about the AOA match get started by some troll and where it always ends!
So let's ignore the troll (the person who originally asked the question) and get back to the very important and substantive discussions regarding hard facts and statistics of MD vs DO vs Caribbean 😴😴😴😴
Wait... Am I the troll? For knowing the exact requirements delineated by the aoa and practiced by multiple, perhaps many or most, aoa programs? I was just fact checking (or more accurately I was clarifying a somewhat impercise comment). It's not trolling if I'm politely correcting a slightly incorrect statement while still agreeing with your main point. Plus this thread stopped being about do vs img ages ago and morphed into tangents many posts ago.
I may have entirely misunderstood your comment cause I'm still not sure I get it.

People in this thread may be interested in this spreadsheet I created. It compares match lists of osteopathic schools as well as COMLEX, GPA/MCAT and a bunch of other stuff. Its not perfect but not the data needed is publicly available. It's a work in progress, I'll put out an update every few months as I add more.
HockeyDr09 - What you did is awesome, THANK YOU!! I hope you don't mind, i hosted your spreadsheet on my site as well in hopes that more people will see it (I gave you full credit)
https://sites.google.com/site/osteopathicreference/home

So does average indebtedness include loans taken out for living fees and everything or simply for tuition and fees?
So does average indebtedness include loans taken out for living fees and everything or simply for tuition and fees?
In that excellent excel sheet a few posts up under the schools tab
People in this thread may be interested in this spreadsheet I created. It compares match lists of osteopathic schools as well as COMLEX, GPA/MCAT and a bunch of other stuff. Its not perfect but not the data needed is publicly available. It's a work in progress, I'll put out an update every few months as I add more.
HockeyDr09 - What you did is awesome, THANK YOU!! I hope you don't mind, i hosted your spreadsheet on my site as well in hopes that more people will see it (I gave you full credit)
https://sites.google.com/site/osteopathicreference/home
For each school, I divided the total number of students who matched into residency by the entering class size. For most schools, only about 70~80% of students successfully matched after all. Does that mean the overall attrition rate can be as high as 30% throughout the four years?😱

Correct me if I'm wrong (I'm not a DO), but I believe that DOs who complete ACGME residencies are accredited through the ABMS boards (the MD pathway) and not through the AOA/osteopathic boards.The AOA will recognize training for DOs done at either ACGME or AOA programs.
The problem isn't the ACGME or the ABMS. If an MD did hypothetically complete an AOA residency, then they would need to be accredited by the osteopathic boards that oversaw his/her postgraduate education.The ACGME will only recognize training for MDs done at ACGME programs, not AOA programs. An MD is not "allowed" to go into an AOA program simply because it wouldn't make sense at all. Why complete post-graduate residency training at a program that won't be recognized? If the ACGME ever changes its stance then MDs could potentially apply to DO programs.



Our mission is to provide students with free, unbiased information, resources, and advising for careers in the health professions. We believe every student deserves access to trustworthy guidance, regardless of background or ability to pay.

