
-
CycleTrack and SDN are teaming up to make medical school admissions more transparent and accessible! Read the announcement to learn how we’re supporting the future of CycleTrack’s free application-tracking tools .
You are using an out of date browser. It may not display this or other websites correctly.
You should upgrade or use an alternative browser.
You should upgrade or use an alternative browser.
Best fellowships in Pathology
Started by Pathshoppingaddict

Get help with your application
Use all the free resources available to you from SDN: articles, guides, expert advising, forums discussions, and school research.

Molecular pathology is the future.
D
deleted314957
If you want a job with a modicum of geographic choice and decent ( and rising) pay you should seriously consider forensics. Molecular may well become the province or partial province of PhD’s and as with the rest of clinical and surgical pathology, reimbursement rates go down with every years CPT pay reduction. But, not everyone can handle forensics.
Advertisement - Members don't see this ad

No fellowship.
Check path outlines. They can’t find bodies to do this crap anymore. The exodus from pathology is finally happening.
It’s the most interesting field in medicine, but medicine in the USA is fading fast. Leadership worries more about personal pronouns and therapy dogs than striving for excellence. I’m glad I woke up before I dedicated 30 more years to this hell. I know I’m not alone.

No way would I vote for dermpath or cytopath.
The exodus in the last year is real.
The exodus in the last year is real.

Care to elaborate? I'm out of the loop.No way would I vote for dermpath or cytopath.
The exodus in the last year is real.
People still look for Cytopath trained fellows. It can land you a job. I wouldn’t recommend it though. Try to work hard in residency so you don’t have to do a fellowship.Care to elaborate? I'm out of the loop.
Preview as many cases as you can, formulate a diagnosis and get feedback from your attending if you make a mistake. Do it over and over again. This is the best way to learn in my opinion.
Damn there are more openings than I’m used to seeing. A lot of weak a😉 fellowship programs who depend on cheap labor should be closed. Good riddens.No fellowship.
Check path outlines. They can’t find bodies to do this crap anymore. The exodus from pathology is finally happening.
It’s the most interesting field in medicine, but medicine in the USA is fading fast. Leadership worries more about personal pronouns and therapy dogs than striving for excellence. I’m glad I woke up before I dedicated 30 more years to this hell. I know I’m not alone.
If any of you trainees go on to a fellowship, please go to the best one possible. Like surgpath. Go to the best program out there. Don’t waste your time at lesser name program. Surgpath, cytopath and hemepath fellowships aren’t competitive to get into. Your going to be slaving away anyways. You might as well get the best bang for your buck.
You forgot renal pathology. Not like it matters.
Have been seeing a lot of jobs looking for hemepath in past year.
Sorry. Added.You forgot renal pathology. Not like it matters.
I'm thinking of the same. I wouldn't really pursue Fellowship in a particular field unless I feel that I need to strengthen my capabilities in that field. The only field that I think you would need to do fellowship if it aligns with your interest is Forensic? I feel like residency isn't enough to prepare you to practice as a Forensic Pathologist but correct me if I'm wrong.People still look for Cytopath trained fellows. It can land you a job. I wouldn’t recommend it though. Try to work hard in residency so you don’t have to do a fellowship.
Preview as many cases as you can, formulate a diagnosis and get feedback from your attending if you make a mistake. Do it over and over again. This is the best way to learn in my opinion.
D
deleted314957
I'm thinking of the same. I wouldn't really pursue Fellowship in a particular field unless I feel that I need to strengthen my capabilities in that field. The only field that I think you would need to do fellowship if it aligns with your interest is Forensic? I feel like residency isn't enough to prepare you to practice as a Forensic Pathologist but correct me if I'm wrong.
If you want to do forensics, you will need a fellowship.

This is a little OT but I'm curious as to what you folks feel is your comfort level with dermpath coming out of residency. Full disclosure, I'm derm trained dermpath (who does almost all dermpath). I was either derm or path in med school, so I still try to keep up with the path world because I always liked it.
Anyway, in my limited experience, it seems that most folks don't seem to get what I feel is enough dp in residency. We had an end of year cytopath fellow here a few years back who wasn't able to tell sccis from mmis for instance.
I'm not saying that a dp fellowship is necessary to practice gen surg path, but I'm just interested in general about thoughts of dp competency straight out of residency.
Also,
"Preview as many cases as you can, formulate a diagnosis and get feedback from your attending if you make a mistake. Do it over and over again. This is the best way to learn in my opinion."
That seems to me to be what path residency should mostly be about. I find it a little sad it has to be stated outright, but I understand why it does.
Last edited:
Advertisement - Members don't see this ad

I don't do dermpath anymore, but I got a good dose of derm at my program and felt pretty comfortable with the bread and butter stuff out of residency. In reality though I suspect for most general paths the only Dx's of importance are Melanoma/SSC/BCC/AK vs. benign, which I suspect most are comfortable with, and anything else gets referred out to a dermpath.This is a little OT but I'm curious as to what you folks feel is your comfort level with dermpath coming out of residency. Full disclosure, I'm derm trained dermpath (who does almost all dermpath). I was either derm or path in med school, so I still try to keep up with the path world because I always liked it.
Anyway, in my limited experience, it seems that most folks don't seem to get what I feel is enough dp in residency. We had an end of year cytopath fellow here a few years back who wasn't able to tell sccis from mmis for instance.
I'm not saying that a dp fellowship is necessary to practice gen surg path, but I'm just interested in general about thoughts of dp competency straight out of residency.
Also,
"Preview as many cases as you can, formulate a diagnosis and get feedback from your attending if you make a mistake. Do it over and over again. This is the best way to learn in my opinion."
That seems to me to be what path residency should mostly be about. I find it a little sad it has to be stated outright, but I understand why it does.
I'm a path trained dermpath and any general pathologist should be able to distinguish sccis from mmis. Your story about the cytopath fellow is unusual.This is a little OT but I'm curious as to what you folks feel is your comfort level with dermpath coming out of residency. Full disclosure, I'm derm trained dermpath (who does almost all dermpath). I was either derm or path in med school, so I still try to keep up with the path world because I always liked it.
Anyway, in my limited experience, it seems that most folks don't seem to get what I feel is enough dp in residency. We had an end of year cytopath fellow here a few years back who wasn't able to tell sccis from mmis for instance.
I'm not saying that a dp fellowship is necessary to practice gen surg path, but I'm just interested in general about thoughts of dp competency straight out of residency.
Also,
"Preview as many cases as you can, formulate a diagnosis and get feedback from your attending if you make a mistake. Do it over and over again. This is the best way to learn in my opinion."
That seems to me to be what path residency should mostly be about. I find it a little sad it has to be stated outright, but I understand why it does.
gbwillner, that's what I was suspecting (the part about what to handle and what to send out). That makes sense. I'd guess training at most path programs (hopefully) should be good to get people comfortable with those diagnoses.
HeyDalaron: I'm hoping that is unusual. I believe you're correct that it is.
HeyDalaron: I'm hoping that is unusual. I believe you're correct that it is.
Depending on volume of dermpath. Some programs have lower volume. That’s why I advocate applicants to go to residency programs with many fellowship programs so you know that the program has the volume.I'm a path trained dermpath and any general pathologist should be able to distinguish sccis from mmis. Your story about the cytopath fellow is unusual.
D
deleted314957
I'm a path trained dermpath and any general pathologist should be able to distinguish sccis from mmis. Your story about the cytopath fellow is unusual.
No kidding. I’ve been retired for 8 years and i could do that in my sleep today.
Even if you see a slight uptick in postings on path outlines, these are mostly third rate jobs. People who spend this many years in education and training want good jobs, not a bunch of third rate crap where they are being exploited. Many of these jobs are academic, and a lot of the private jobs don’t even offer a partnership track. I suppose you are supposed to go there and spend your whole career busting your ass just to fatten somebody else’s bonus check.No fellowship.
Check path outlines. They can’t find bodies to do this crap anymore. The exodus from pathology is finally happening.
It’s the most interesting field in medicine, but medicine in the USA is fading fast. Leadership worries more about personal pronouns and therapy dogs than striving for excellence. I’m glad I woke up before I dedicated 30 more years to this hell. I know I’m not alone.
I see one or two on there that might be promising, if you can actually trust them. And I wish I had a dollar for every time an employer or prospective employer lied to me- especially with regards to partnership tracks and stability of contracts.
Last edited:
All academic jobs are 3rd rate? Come on. Not everyone has a primary motivation of only making as much money as possible. If that was your only goal, medicine was a bad choice.Even if you see a slight uptick in postings on path outlines, these are mostly third rate jobs. People who spend this many years in education and training want good jobs, not a bunch of third rate crap where they are being exploited. Many of these jobs are academic, and a lot of the private jobs don’t even offer a partnership track. I suppose you are supposed to go there and spend your whole career busting your ass just to fatten somebody else’s bonus check.
I see one or two on there that might be promising, if you can actually trust them. And I wish I had a dollar for every time an employer or prospective employer lied to me- especially with regards to partnership tracks and stability of contracts.
Indeed. I turned down dermpath to do informatics, and even I feel comfortable with neoplastic dermpath (ie, I know my limits). Less so with the inflammatory derm.No kidding. I’ve been retired for 8 years and i could do that in my sleep today.

What are your thoughts on combining a molecular with hemepath fellowship?Molecular, then molecular in no 2 and then molecular no 3 as well.
Start up money in mol diagnostics space is insane. Go biotech or go home.
D
deleted314957
Molecular, then molecular in no 2 and then molecular no 3 as well.
Start up money in mol diagnostics space is insane. Go biotech or go home.
Or retire from the rat race.
Good combo. You should be able to get a job with heme only as well.What are your thoughts on combining a molecular with hemepath fellowship?
What about Molecular + Microbiology?Good combo. You should be able to get a job with heme only as well.
Never heard of anyone doing that combo. Maybe good for academics only. I’ve rarely seen jobs advertised for micro.What about Molecular + Microbiology?
Waste of time.What about Molecular + Microbiology?
Advertisement - Members don't see this ad
Nice to see Molecular take its rightful place as the king of the fellowships!

I find it interesting that molecular has the most votes from a perspective I presume is external--anyone on here actually HAVE a molecular fellowship or just projecting?
I had the same mind 10 yrs ago when looking at fellowships and decided against it as it was too early. We've come a long way since then but I just don't see molecular as offering fantastic job prospects by itself, rather the POTENTIAL if(when) molecular platforms become routine/commonplace. Perhaps it will give you headway in mega groups or it's a long-play for the next 10 (20?) years, but all the current jobs for molecular are either academic or large corporate (Quest, Roche, CTCA), or if you are legit looking for biotech start-up opportunities.
A molecular fellowship wouldn't give anyone an advantage applying to any group I'm familiar with, IMO it just gives potential IF one is entrepreneurial and has lots of patience for the economy of scale to filter down to non-corporate/academic entities. The platforms are just too diverse and expensive to offer broad all encompassing molecular services, and table top machines that can perform some basic NSCLC and breast testing don't require a molecular fellowship.
Last edited:
I am boarded in Molecular and this is really all I practice. I agree with most of your statements- it is not necessarily a good fellowship for most AP's if your focus is surgical pathology sign out. It is really its own expertise that is far closer to medical oncology than surgical oncology. While you are also right that there probably is not much room/value in most path groups to start a molecular service, there is a lot of opportunity in this space in the form of niche molecular labs, start-ups, large commercial labs, industry, drug development, and academia for molecular. I will also add that a 1 year fellowship hardly teaches you enough molecular genetics to really become an expert in this field.I find it interesting that molecular has the most votes from a perspective I presume is external--anyone on here actually HAVE a molecular fellowship or just projecting?
I had the same mind 10 yrs ago when looking at fellowships and decided against it as it was too early. We've come a long way since then but I just don't see molecular as offering fantastic job prospects by itself, rather the POTENTIAL if(when) molecular platforms become routine/commonplace. Perhaps it will give you headway in mega groups or it's a long-play for the next 10 (20?) years, but all the current jobs for molecular are either academic or large corporate (Quest, Roche, CTCA), or if you are legit looking for biotech start-up opportunities.
A molecular fellowship wouldn't give anyone an advantage applying to any group I'm familiar with, IMO it just gives potential IF one is entrepreneurial and has lots of patience for the economy of scale to filter down to non-corporate/academic entities. The platforms are just too diverse and expensive to offer broad all encompassing molecular services, and table top machines that can perform some basic NSCLC and breast testing don't require a molecular fellowship.
D
deleted314957
I am boarded in Molecular and this is really all I practice. I agree with most of your statements- it is not necessarily a good fellowship for most AP's if your focus is surgical pathology sign out. It is really its own expertise that is far closer to medical oncology than surgical oncology. While you are also right that there probably is not much room/value in most path groups to start a molecular service, there is a lot of opportunity in this space in the form of niche molecular labs, start-ups, large commercial labs, industry, drug development, and academia for molecular. I will also add that a 1 year fellowship hardly teaches you enough molecular genetics to really become an expert in this field.
How do y’all plan/ hope to keep the PhD’s away from this? Or is it already a turf battle?
This is a great question. IMO, this is where test interpretation becomes vital. A PhD can't interpret a test result or make recommendations for management based on those results; these are also billable events. PhDs are more than able to act to oversee some molecular activities like germline testing, looking for likely pathogenic variants, etc., but they cannot tell an oncologist they should change chemo or recommend pembrolizumab.How do y’all plan/ hope to keep the PhD’s away from this? Or is it already a turf battle?
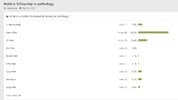
Molecular has a whole 8 votes in the poll. Are we ready to project it as the winner?

What are your thoughts on combining a molecular with hemepath fellowship?
There´s probably a fair amount of crossover and utility. Our Hemepath is pretty much tasked with most of the molecular related tests. Back in training, I met an attending that leveraged this combo quite strategically. Either or both would be valuable in practice.
Wonder how many who voted for dermpath in 2009 are now working at some VC funded slide mill?
Hopefully they were able to make bank/partner and receive a healthy buyout from VC's before pathology reimbursement took a sharp nosedive circa 2016.Wonder how many who voted for dermpath in 2009 are now working at some VC funded slide mill?
No. That would be a professional service. They are not physicians and thus cannot perform such services.In our academic department, two out of the seven molecular pathology faculty are PhD's. Are they not allowed to bill for interpretations?
Lol. Goes to show that there are fewer and fewer voices here.This is from a post in 2009. We should wait for more votes..
D
deleted314957
Wonder how many who voted for dermpath in 2009 are now working at some VC funded slide mill?
A whole lot. And I know that for a fact.

Just don’t do a fellowship at a crappy place with low volume. Choose your fellowship based on seeing consults, variety, and a high number of cases. The metrics by the ACGME for approving fellowship sites sux. Unfortunately many choose fellowships locations to remain in a region and give up quality of education, exposure, responsibility over cases for lifestyle and region. Do that after your done training. Why do so many want lifestyle so quickly rather than going to the best places after sacrificing so much money and time to get to this point?
Advertisement - Members don't see this ad
D
deleted314957
Just don’t do a fellowship at a crappy place with low volume. Choose your fellowship based on seeing consults, variety, and a high number of cases. The metrics by the ACGME for approving fellowship sites sux. Unfortunately many choose fellowships locations to remain in a region and give up quality of education, exposure, responsibility over cases for lifestyle and region. Do that after your done training. Why do so many want lifestyle so quickly rather than going to the best places after sacrificing so much money and time to get to this point?
It’s called “ delayed gratification”. Some folks can’t delay anymore than they have already.
Just don’t do a fellowship at a crappy place with low volume. Choose your fellowship based on seeing consults, variety, and a high number of cases. The metrics by the ACGME for approving fellowship sites sux. Unfortunately many choose fellowships locations to remain in a region and give up quality of education, exposure, responsibility over cases for lifestyle and region. Do that after your done training. Why do so many want lifestyle so quickly rather than going to the best places after sacrificing so much money and time to get to this point?
Agree go to the best program you can get in for fellowship especially the non competitive ones like surgpath, cytopath, hemepath (although more competitive at top places).
I can understand in certain situations though where people have family and houses and moving can be a pain in the butt.
Unfortunately many choose fellowships locations to remain in a region and give up quality of education, exposure, responsibility over cases for lifestyle and region. Do that after your done training. Why do so many want lifestyle so quickly rather than going to the best places after sacrificing so much money and time to get to this point?
Spouse here.
Some people may want to settle in a particular region, and think that doing a local fellowship positions them to do so more effectively than a better fellowship somewhere else. Local training can help—if my husband hadn’t trained in our current city, I doubt we could have stayed.
Fellowship(s) may also coincide with having very small kids, or with a phase of a spouse’s career that is equally critical.
Even spouses who were okay with moving for med school and/or residency may conclude that moving repeatedly within a two year period is more than they want to deal with. I think it’s safe to say that most people don’t love uprooting repeatedly for the sake of someone else’s career aspirations.
So sometimes it’s not about “lifestyle” as much as balancing your career aspirations with your entire family’s needs and the rest of your life.
Always great to have a supportive spouse.Spouse here.
Some people may want to settle in a particular region, and think that doing a local fellowship positions them to do so more effectively than a better fellowship somewhere else. Local training can help—if my husband hadn’t trained in our current city, I doubt we could have stayed.
Fellowship(s) may also coincide with having very small kids, or with a phase of a spouse’s career that is equally critical.
Even spouses who were okay with moving for med school and/or residency may conclude that moving repeatedly within a two year period is more than they want to deal with. I think it’s safe to say that most people don’t love uprooting repeatedly for the sake of someone else’s career aspirations.
So sometimes it’s not about “lifestyle” as much as balancing your career aspirations with your entire family’s needs and the rest of your life.
Especially one that posts on a path board. Obviously decisions made for family stability are of utmost importance. However a fellowship was intended to be the capstone of a career after much sacrifice and incurring of debt. As you may have seen in other posts many people move within a few years of their first job so why not at least get solid training?
Spouse here.
Some people may want to settle in a particular region, and think that doing a local fellowship positions them to do so more effectively than a better fellowship somewhere else. Local training can help—if my husband hadn’t trained in our current city, I doubt we could have stayed.
Fellowship(s) may also coincide with having very small kids, or with a phase of a spouse’s career that is equally critical.
Even spouses who were okay with moving for med school and/or residency may conclude that moving repeatedly within a two year period is more than they want to deal with. I think it’s safe to say that most people don’t love uprooting repeatedly for the sake of someone else’s career aspirations.
So sometimes it’s not about “lifestyle” as much as balancing your career aspirations with your entire family’s needs and the rest of your life.
Yeah agree train where you want to work to put yourself in a good position for local jobs that may pop up. The word of mouth jobs aren’t advertised so you have to be in the loop aka you need to be local.
Similar threads
- Replies
- 0
- Views
- 581
