
Advertisement - Members don't see this ad
You are using an out of date browser. It may not display this or other websites correctly.
You should upgrade or use an alternative browser.
You should upgrade or use an alternative browser.
Colonoscopy death. 25 Million Jury verdict
Started by NPJR

Advertisement - Members don't see this ad
What was the cavalier part?Good. Need more verdicts and headlines like this. No reason for that man to be dead. Hopefully they won’t be so cavalier going forward.
What exactly happened during the case that rose to the level of malpractice?Good. Need more verdicts and headlines like this. No reason for that man to be dead. Hopefully they won’t be so cavalier going forward.

cittykat
Full Member
What was the cavalier part?
What exactly happened during the case that rose to the level of malpractice?
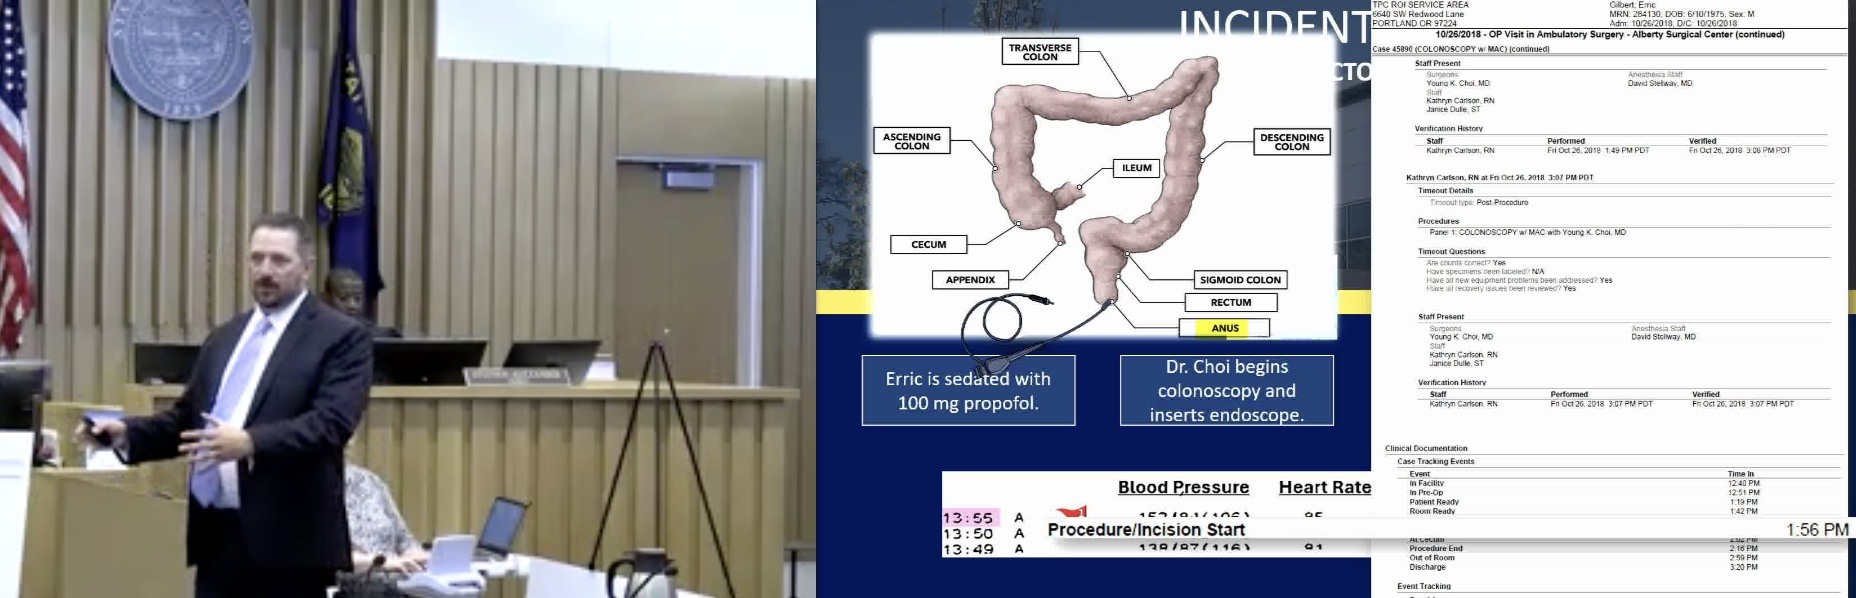
$50M+ Malpractice Trial Over Death After Routine Colonoscopy Begins, Watch Online via CVN
An Oregon jury heard openings Wednesday in a malpractice lawsuit blaming a medical team at an outpatient surgery center for a man’s death following a routine colonoscopy.
“Shortly after Dr. David Stellway administered the anesthesia, Claggett said Gilbert's blood pressure began to rise and his blood oxygen levels began to fall. Despite this, he claimed Dr. Young Choi, the gastroenterologist performing the colonoscopy, continued with the procedure even when Kathryn Carlson, the sedation nurse, noted signs of respiratory distress and lack of pinkness in Gilbert’s skin.
Dr. Stellway began “bagging” Gilbert using an external respiration mask, but did not advise Dr. Choi to halt the procedure when asked if a pause would be helpful to focus on restoring Gilbert’s airway. By this point Claggett noted Gilbert had been in respiratory arrest for almost eight minutes. Dr. Choi continued and concluded the procedure, but according to Claggett Gilbert’s vitals worsened further.
Claggett described that eventually a surgical technician in the room, Janice Dulle, not Dr. Choi or Nurse Carlson, realized the severity of Gilbert’s condition and hit the “code” button on the wall, summoning a nearby EMS team, which found Gilbert at that point in full cardiac arrest.
“They arrive and find the staff in chaos and no CPR being given, even after the code,” Claggett said, claiming adequate CPR only began 22 minutes after Gilbert stopped breathing. He was transported to a local hospital, declared brain dead, and died shortly afterward.“
Pt reportedly had BMI 40 and used CPAP for OSA. No reason to do that case at a freestanding surgicenter. Description says pt was mask ventilated, was there even an anesthesia machine and advanced airway devices in the room? If not it was a setup for predictable failure.
Last edited:

My friend, this was and still is extremely common at ASCs.Pt reportedly had BMI 40 and used CPAP for OSA. No reason to do that case at a freestanding surgicenter.
At my old practice, we had to fight extremely hard for BMI limits. At one orthopedic site, it was 45 for generals (GETA) and 50 (!!!) for MAC. Complications happened requiring EMS transfers to hospitals (mostly interscalene blocks and respiratory compromise). The center didn’t much care and gave us immense trouble when we tried to axe a case - “come on, it’s just this one case / it’ll be quick / it’s a VIP / my equipment and staff are all here surgical outcomes are best with that…” We finally left that dump as we grew tired of the constant pushing at the limits.

This guy didn't die because his BMI was 40. That's not really pushing the envelope for a surgicenter.Pt reportedly had BMI 40 and used CPAP for OSA. No reason to do that case at a freestanding surgicenter. Description says pt was mask ventilated, was there even an anesthesia machine and advanced airway devices in the room? If not it was a setup for predictable failure.
If the article is to be taken at face value, this was a problem of monitoring and resuscitation.
So did the anesthesiologist start the case and then leave the monitoring to a ‘sedation nurse’, not a CRNA? Is this a common model?

My friend, this was and still is extremely common at ASCs.
At my old practice, we had to fight extremely hard for BMI limits. At one orthopedic site, it was 45 for generals (GETA) and 50 (!!!) for MAC. Complications happened requiring EMS transfers to hospitals (mostly interscalene blocks and respiratory compromise). The center didn’t much care and gave us immense trouble when we tried to axe a case - “come on, it’s just this one case / it’ll be quick / it’s a VIP / my equipment and staff are all here surgical outcomes are best with that…” We finally left that dump as we grew tired of the constant pushing at the limits.
That's a bunch of b.s. but not surprised that ortho bros were involved in scheduling them

BMI 40 with sleep apnea is like 95% of my surgery center colonoscopies. The argument this should have been done at a hospital is moot point.
Last edited:
cittykat
Full Member
My friend, this was and still is extremely common at ASCs.
At my old practice, we had to fight extremely hard for BMI limits. At one orthopedic site, it was 45 for generals (GETA) and 50 (!!!) for MAC. Complications happened requiring EMS transfers to hospitals (mostly interscalene blocks and respiratory compromise). The center didn’t much care and gave us immense trouble when we tried to axe a case - “come on, it’s just this one case / it’ll be quick / it’s a VIP / my equipment and staff are all here surgical outcomes are best with that…” We finally left that dump as we grew tired of the constant pushing at the limits.
I know it’s common. That’s why stopped doing freestanding ASCs. They’re driven by money and ignore patient safety. Ironically patients with crappy insurance get shunted to the hospitals that have better equipment and better support. I’m a low BMI ASA2. When I had my own colonoscopy I picked a GI who works out of a hospital attached ASC. Hopefully people will stop doing this.
Last edited:
It's "moot."BMI 40 with sleep apnea is like 95% of my surgery center colonoscopies. The argument this should have been done at a hospital is mute point.
cittykat
Full Member
So did the anesthesiologist start the case and then leave the monitoring to a ‘sedation nurse’, not a CRNA? Is this a common model?
No I think he let the patient die under his direct hands on care. 1st month CA-1 level stuff.
If the same anesthesiologist did the case at the hospital, the patient would still have died. If he had an anesthesia machine, patient still would have died.BMI 40 with sleep apnea is like 95% of my surgery center colonoscopies. The argument this should have been done at a hospital is moot point.
It sounds like an anesthesiologist who works only in a GI center and probably hasn’t intubated in the last 5 years.
Advertisement - Members don't see this ad
BMI 40 with sleep apnea is like 95% of my surgery center colonoscopies. The argument this should have been done at a hospital is mute point.
Certainly that argument would fall on deaf ears.
Bmi 40 and OSA is not an indication to do this case at a hospital...not at all.I know it’s common. That’s why stopped doing freestanding ASCs. They’re driven by money and ignore patient safety. Ironically patients with crappy insurance get shunted to the hospitals that have better equipment and better support. Hopefully people will stop doing this.
This patient died during the procedure (laryngospasm it seems).
The basic treatment for that is the same in a hospital or asc. Hospital doesnt magically make it safer. This patient would have died under the same circumstances in a hospital. Call a code? For what? An ED doc is going to come help you intubate? A pharmacist is going to help you do what? Need an RT to put the stylet in for you?
Mask ventilate, ambu bag, sux, glidescope, ETT. All basics that are available in any basic ASC. Just need a competent nurse.
Need to have legitimate reasons to cancel a case and send it to a hospital. Being scare of big patients isnt a reason. Any EGD could easily larygospasm just like this. Should we send all egds to hospitals too?
BMI limit is 50 in one of the ASCs I work. People are fat. Generally they don’t die from it acutely. I don’t understand parts of this article. That isn’t surprising.
Bmi 40 and OSA is not an indication to do this case at a hospital...not at all.
This patient died during the procedure (laryngospasm it seems).
The basic treatment for that is the same in a hospital or asc. Hospital doesnt magically make it safer. This patient would have died under the same circumstances in a hospital. Call a code? For what? An ED doc is going to come help you intubate? A pharmacist is going to help you do what? Need an RT to put the stylet in for you?
Mask ventilate, ambu bag, sux, glidescope, ETT. All basics that are available in any basic ASC. Just need a competent nurse.
Need to have legitimate reasons to cancel a case and send it to a hospital. Being scare of big patients isnt a reason. Any EGD could easily larygospasm just like this. Should we send all egds to hospitals too?
Some places won’t carry sux.
cittykat
Full Member
Carry it yourself. Or roc/suggamadexSome places won’t carry sux.
Videoscope are common place in 2025/2026
They weren’t that common in asc in 2018
We didn’t get videoscope until 2019 at a stand a lone asc with peds I covered. And it was one of those copilot orange ones. I forgot the price at the time but certainly cheaper than glidescope
I don’t know the reason for failure to resuscitate for 22 minutes.
They weren’t that common in asc in 2018
We didn’t get videoscope until 2019 at a stand a lone asc with peds I covered. And it was one of those copilot orange ones. I forgot the price at the time but certainly cheaper than glidescope
I don’t know the reason for failure to resuscitate for 22 minutes.
Every ASC needs to have sux.Some places won’t carry sux.
If it doesnt have sux..i doubt it would have sugamm.
Big risk if you dont have it. All it takes is one laryngospasm that doesn't break... like this case
Disagree. An endo center in my corner of the world has rocuronium and suggamadex. I would be fine working there.Every ASC needs to have sux.
If it doesnt have sux..i doubt it would have sugamm.
Big risk if you dont have it. All it takes is one laryngospasm that doesn't break... like this case
Why would they pay for sugammadex and not succ?Disagree. An endo center in my corner of the world has rocuronium and suggamadex. I would be fine working there.
Don't need an MH cart/Dantrolene.Why would they pay for sugammadex and not succ?

I sometimes do Gi at an ASC. No anesthesia machine in the room. I make sure ambubag is avail, suction and my Mcgrath is on the cart. I keep a fresh, unopened bottle of sux next to my McGrath. I can tell 97% of the time when a patient will be difficult in terms of airway/apnea and I let the staff know in a calm, reassuring manner. IMHO, Sux is superior to Roc in these situations/patients in terms of efficacy and time of response.If the same anesthesiologist did the case at the hospital, the patient would still have died. If he had an anesthesia machine, patient still would have died.
It sounds like an anesthesiologist who works only in a GI center and probably hasn’t intubated in the last 5 years.
What concerns me more than the airway (which I prepare for in advance) are the micro-aspirations which sometimes happen on the BMI of 38++ patients.
I can't control that aspect of an EGD/Colonoscopy even if the Gi doc sucks out the gastric secretions quite well.
It's a rare/never used drug in a GI center. Couple vials on hand. Negligible cost ... vs succ plus a MH cart full of expensive drugs that expire - and that has to be checked/maintained by a person every so often.Why would they pay for sugammadex and not succ?
cittykat
Full Member
I sometimes do Gi at an ASC. No anesthesia machine in the room. I make sure ambubag is avail, suction and my Mcgrath is on the cart. I keep a fresh, unopened bottle of sux next to my McGrath. I can tell 97% of the time when a patient will be difficult in terms of airway/apnea and I let the staff know in a calm, reassuring manner. IMHO, Sux is superior to Roc in these situations/patients in terms of efficacy and time of response.
What concerns me more than the airway (which I prepare for in advance) are the micro-aspirations which sometimes happen on the BMI of 38++ patients.
I can't control that aspect of an EGD/Colonoscopy even if the Gi doc sucks out the gastric secretions quite well.
The microaspirations and macro aspirations likely trigger some of those airway events. You could easily prevent aspiration by intubating those patients. But I know you gotta move the meat.
Last edited:
Advertisement - Members don't see this ad
Lol..intubate colonoscopies??The microaspirations and macro aspirations likely trigger some of those airway events. You could easily prevent aspiration by intubating those patients. But I know you gotta move the meat.
Ahh i see. Thats fine then.It's a rare/never used drug in a GI center. Couple vials on hand. Negligible cost ... vs succ plus a MH cart full of expensive drugs that expire - and that has to be checked/maintained by a person every so often.
cittykat
Full Member
Lol..intubate colonoscopies??
I was referring more for uppers but I’ve put in LMAs for colonoscopies in patients with unfavorable airways or body habitus. It’s no big deal because I work in a hospital with anesthesia machines in our endo suite. It is safer and a lot less stressful than the other option which is a natural airway GA. Some patients are unsuitable for natural airway GAs. The reason people dislike GI is because they allow themselves to be pressured into compromising patient safety. If you don’t compromise they are really easy stress free cases.
Last edited:
It absolutely is. But Roc is good enough. A reasonable choice in the actual world in which we live where costs are (almost) everything.IMHO, Sux is superior to Roc in these situations/patients in terms of efficacy and time of response.
The microaspirations and macro aspirations likely trigger some of those airway events. You could easily prevent aspiration by intubating those patients. But I know you gotta move the meat.
intubating people doesn't prevent aspirations. It prevents them during the procedure. They can still aspirate after you extubate them.
the not funny thing about this particular case is the fact it was performed in an ASC probably did not contribute to the bad outcome. The bad outcome was a direct result of who the people in the room were. If those individuals were doing it in a hospital the same thing would have happened.

Arch Guillotti
Senior Member
Staff member
Administrator
Volunteer Staff
Lifetime Donor
20+ Year Member
its moot pointBMI 40 with sleep apnea is like 95% of my surgery center colonoscopies. The argument this should have been done at a hospital is mute point.
cittykat
Full Member
intubating people doesn't prevent aspirations. It prevents them during the procedure. They can still aspirate after you extubate them.
Of course that is possible.
Intubating an egd would be overkill and not necessarily safer vs giving a lighter sedative and spraying cetacaine, as one example. You are still intubating a potentially difficult airway... certainly not risk free. Would be reserved for very unusual cases. We occasionally see that done with the new grads until they get comfortable and a bit more experiencedI was referring more for uppers but I’ve put in LMAs for colonoscopies in patients with unfavorable airways or body habitus. It’s no big deal because I work in a hospital with anesthesia machines in our endo suite. It is safer and a lot less stressful than the other option which is a natural airway GA. Some patients are unsuitable for natural airway GAs. The reason people dislike GI is because they allow themselves to be pressured into compromising patient safety. If you don’t compromise they are really easy stress free cases.
Using an LMA for a colonoscopy just suggests a lack of expertise/experience in handling those cases. LMAs may dislodge, dont seat well, and require larger sedative doses to place. Wouldn't work well if GI doc wants to put the patient on their stomach...etc. i have yet to encounter a colonoscopy that needed a LMA in 20 years. I have had probably 2-3 egds that have laryngospasmed in 20 years, needed sux for one and Ambu bag for the others. Pretty simple to handle when you are prepared
Most people like GI if its a production model.
cittykat
Full Member
Intubating an egd would be overkill and not necessarily safer vs giving a lighter sedative and spraying cetacaine, as one example. You are still intubating a potentially difficult airway... certainly not risk free. Would be reserved for very unusual cases. We occasionally see that done with the new grads until they get comfortable and a bit more experienced
Using an LMA for a colonoscopy just suggests a lack of expertise/experience in handling those cases. LMAs may dislodge, dont seat well, and require larger sedative doses to place. Wouldn't work well if GI doc wants to put the patient on their stomach...etc. i have yet to encounter a colonoscopy that needed a LMA in 20 years. I have had probably 2-3 egds that have laryngospasmed in 20 years, needed sux for one and Ambu bag for the others. Pretty simple to handle when you are prepared
Most people like GI if its a production model.
I’m in a production model and I like GI but I do it the way I like. I don’t like doing jaw thrust the whole case or wrestling patients so I don’t. FWIW in 30+ yrs I’ve never put an EGD on their stomach.
50?? Pffft. Amateurs. Ours just increased it to 55. Fun times aheadBMI limit is 50 in one of the ASCs I work. People are fat. Generally they don’t die from it acutely. I don’t understand parts of this article. That isn’t surprising.
Yes, in terms of a patients on their stomach, i said colons not egd.I’m in a production model and I like GI but I do it the way I like. I don’t like doing jaw thrust the whole case or wrestling patients so I don’t. FWIW in 30+ yrs I’ve never put an END on their stomach.
Not sure that making your day easier is an indication to place an lma...but to each his own i guess. Many places don't have vents in GI suites. Requires a different skill set
cittykat
Full Member
Yes, in terms of a patients on their stomach, i said colons not egd.
Not sure that making your day easier is an indication to place an lma...but to each his own i guess.
It’s easier and less stressful because the patient is safer. I can do most cystos and knee scopes without an LMA and during training we were forced to do it that way to develop mask skills but I don’t do it now.
Many places don't have vents in GI suites. Requires a different skill set
How did we as a specialty agree to this?
Give over. An lma for a colon are you for real? Why not put a swan in too?I was referring more for uppers but I’ve put in LMAs for colonoscopies in patients with unfavorable airways or body habitus. It’s no big deal because I work in a hospital with anesthesia machines in our endo suite. It is safer and a lot less stressful than the other option which is a natural airway GA. Some patients are unsuitable for natural airway GAs. The reason people dislike GI is because they allow themselves to be pressured into compromising patient safety. If you don’t compromise they are really easy stress free cases.
Go way with your safety spiel nonsense. You must either be dealing with the sickest patients in the entire world or you have absolutely no skills
I must have done 10000 colons on everything from asa1s to basically dead and never even came close to needing an lma for anyone... never even heard of my colleagues doing one which may push it to 500k colons. this is insane...
50 of prop to put the probe in. Pull the jaws off em to get em to breath. Chill for couple mins and chart. Another 50 to get around the splenic, maybe 30 for the hepatic and youre done.... this is ludicrous
The guy who died had an absolute turnip looking after him
We agreed because its not necessary.It’s easier and less stressful because the patient is safer. I can do most cystos and knee scopes without an LMA and during training we were forced to do it that way to develop mask skills but I don’t do it now.
How did we as a specialty agree to this?
Safer based on what data? Lmas have all sorts of potential complications. Airway trauma, dental trauma, dislodgement, laryngospasm. Not to mention slower procedure times, delayed turnover, increased ponv, increased costs, and the list goes on.
Advertisement - Members don't see this ad
50?? Pffft. Amateurs. Ours just increased it to 55. Fun times ahead
Totally. I have worked at probably 20 different ascs/hospitals over the years...an lma for a colonoscopy would get laughed out of the buildingGive over. An lma for a colon are you for real? Why not put a swan in too?
Go way with your safety spiel nonsense. You must either be dealing with the sickest patients in the entire world or you have absolutely no skills
I must have done 10000 colons on everything from asa1s to basically dead and never even came close to needing an lma for anyone... never even heard of my colleagues doing one which may push it to 500k colons. this is insane...
50 of prop to put the probe in. Pull the jaws off em to get em to breath. Chill for couple mins and chart. Another 50 to get around the splenic, maybe 30 for the hepatic and youre done.... this is ludicrous
The guy who died had an absolute turnip looking after him
What do you produce? 1 colon a day? 2?I’m in a production model and I like GI but I do it the way I like. I don’t like doing jaw thrust the whole case or wrestling patients so I don’t. FWIW in 30+ yrs I’ve never put an EGD on their stomach.

This is spot on. I go to 6+ endo centers and none of them carry suxSome places won’t carry sux.

Can anyone find the actual lawsuit? I don’t want to put blame till I see details but it is an unusual story. An obese 43 year old died from hypoxia? Did he not have the monitors on? Did he try to intubate/lma? Was he just bag masking and ignoring that he wasn’t getting etc02 and waiting for it to come up? 22 minutes to start cpr, was this after he lost a pulse?
Does anyone know what happens when they want more than your policy limit? If he settled out of court they likely took the 3/5M limit, if they had pursued personal assets he might have gone to court. How many of you have umbrella policies?
LMA v gawa: who cares how anyone else does their endo, if it’s that’s strongly looked down upon culturally someone will say something. I’ve done endo in spaces slightly larger than 2 closets with wall O2 where we had to push the bed into the hallway to turn it around for doubles while sitting 5 inches from the GI doc and hospital ones where it’s all asc rejects and complex ercps/nercrosectomies/stents. I think GI guys don’t care as long as their patient is alive and their turnover time is under 10 minutes. And an lma is a supraglottic airway so if you’re against lmas are you also against opas/npas?
Does anyone know what happens when they want more than your policy limit? If he settled out of court they likely took the 3/5M limit, if they had pursued personal assets he might have gone to court. How many of you have umbrella policies?
LMA v gawa: who cares how anyone else does their endo, if it’s that’s strongly looked down upon culturally someone will say something. I’ve done endo in spaces slightly larger than 2 closets with wall O2 where we had to push the bed into the hallway to turn it around for doubles while sitting 5 inches from the GI doc and hospital ones where it’s all asc rejects and complex ercps/nercrosectomies/stents. I think GI guys don’t care as long as their patient is alive and their turnover time is under 10 minutes. And an lma is a supraglottic airway so if you’re against lmas are you also against opas/npas?
Last edited:
Similar threads


- Replies
- 97
- Views
- 7K


