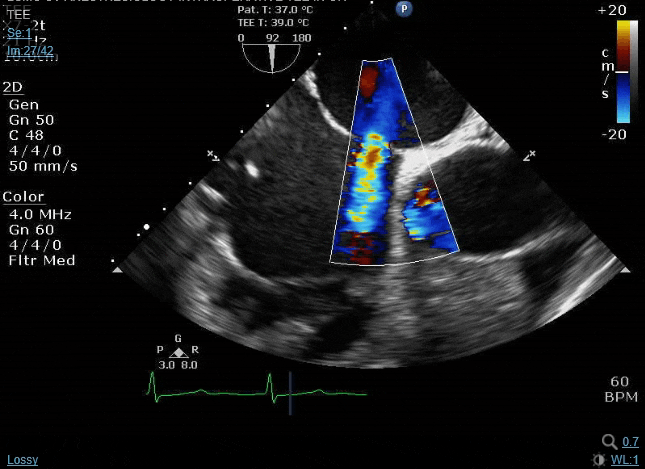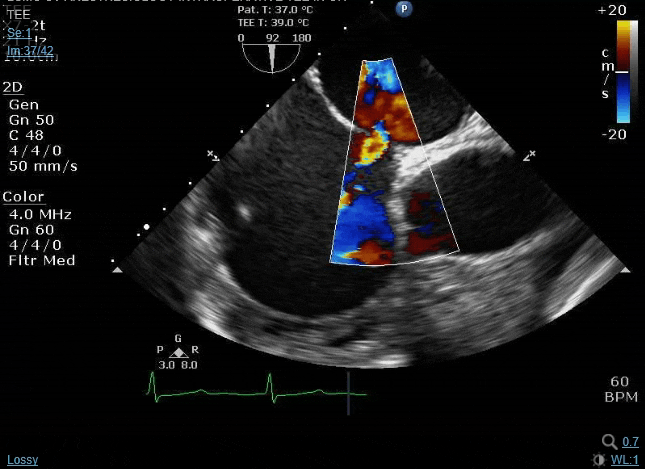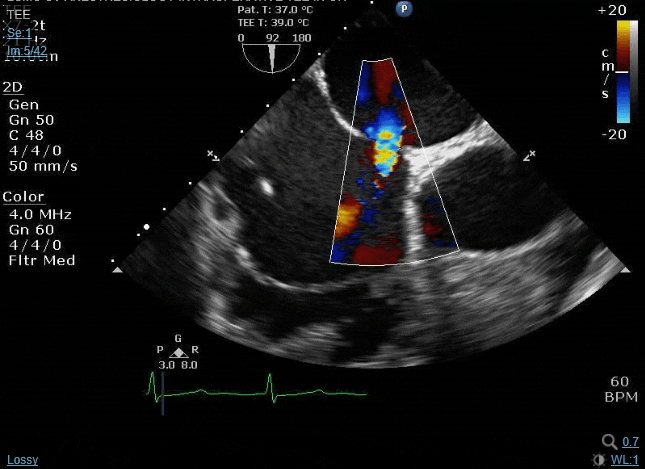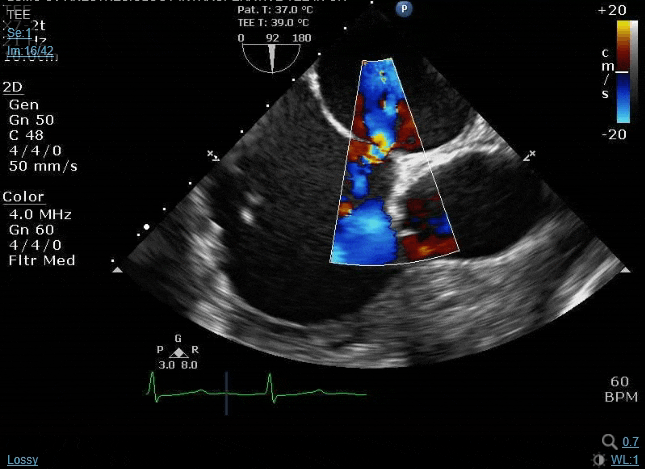
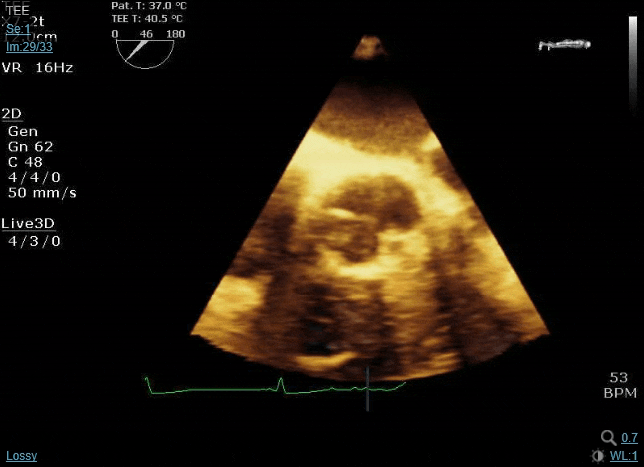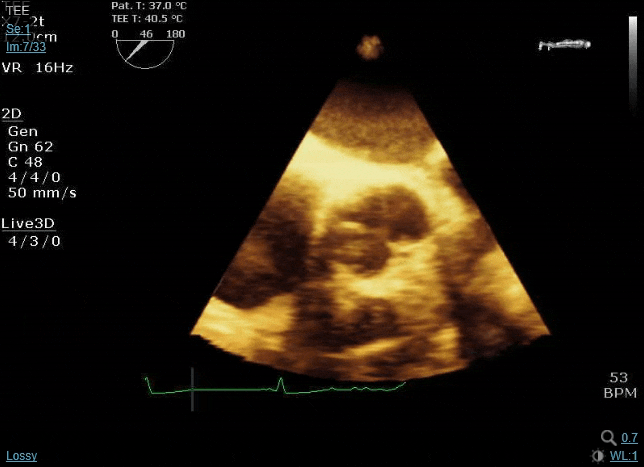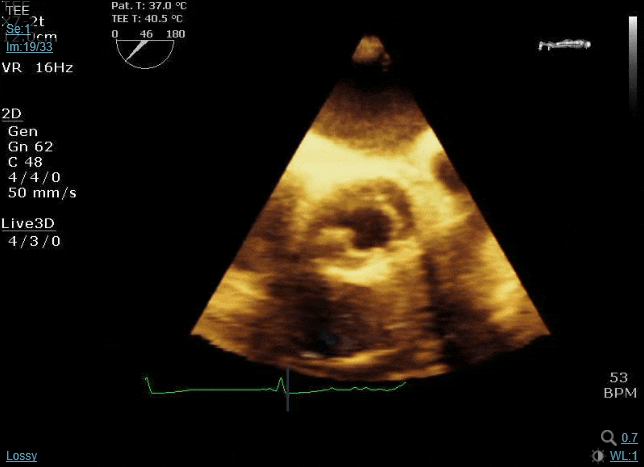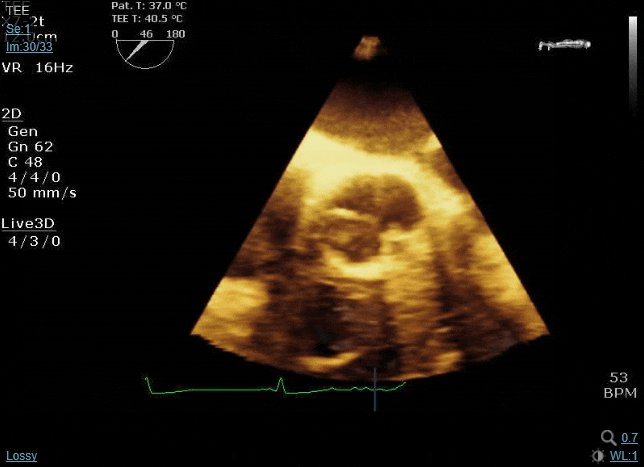
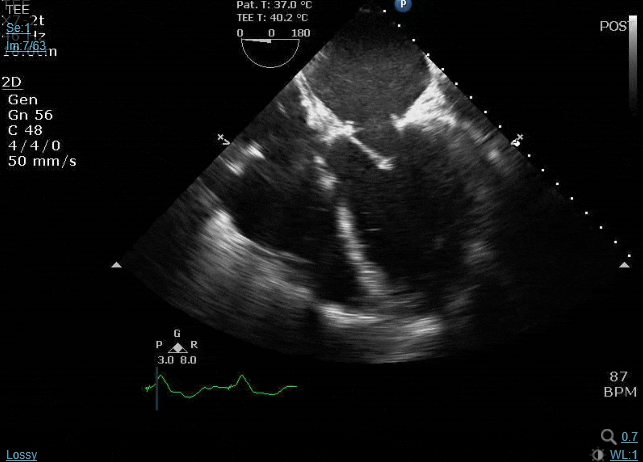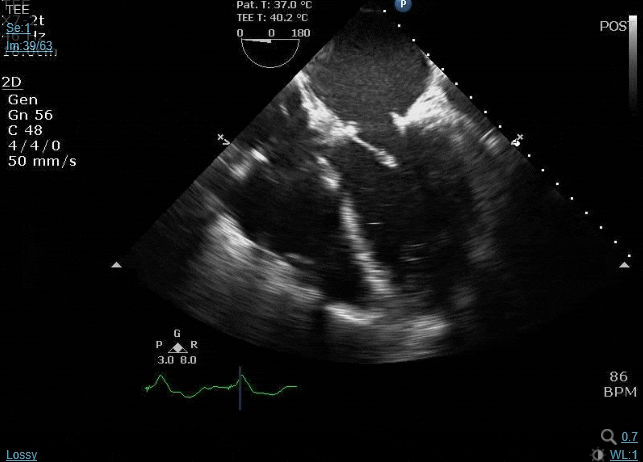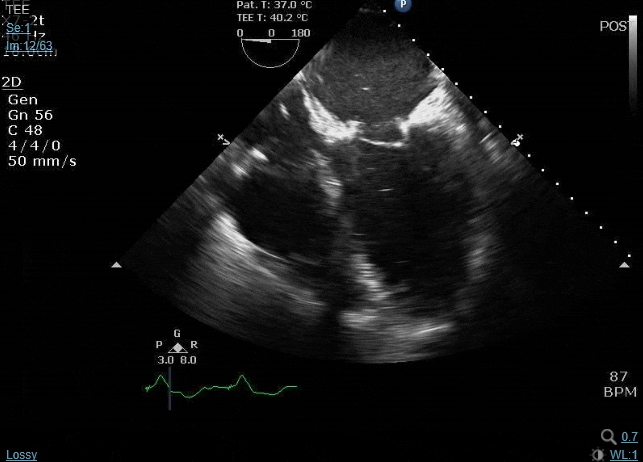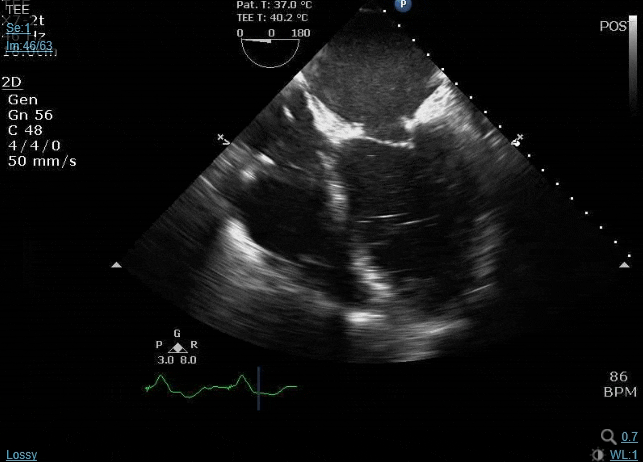
re: @vector2 's case, at first glance I thought you were giving us an off-axis cut (as opposed to a true mid-pap) with the AL pap muscle, and chordal tissue above the PM pap... That being said, the chords do look a bit too hyperechoic. My guess was gonna be neochords placed as part of the MVr, with resection (as opposed to sparing) of the native chordal apparatus leading to altered LV/septal geometry, thus impacting RV function... But not super confident about that assessment without additional views, since the stuff in your second clip looks a bit too hyperechoic for necochords (unless your surgeons are using different material than what I'm used to seeing)
-
CycleTrack and SDN are teaming up to make medical school admissions more transparent and accessible! Read the announcement to learn how we’re supporting the future of CycleTrack’s free application-tracking tools .
You are using an out of date browser. It may not display this or other websites correctly.
You should upgrade or use an alternative browser.
Let's do some echo:
Started by sevoflurane
Get help with your application
Use all the free resources available to you from SDN: articles, guides, expert advising, forums discussions, and school research.
Nope, it's not a neochord. The reason the function is down in the RV and the inferior distribution of the LV is not because of a zebra. It's actually part of the common mnemonics used for things one has to verify before coming off pumpre: @vector2 's case, at first glance I thought you were giving us an off-axis cut (as opposed to a true mid-pap) with the AL pap muscle, and chordal tissue above the PM pap... That being said, the chords do look a bit too hyperechoic. My guess was gonna be neochords placed as part of the MVr, with resection (as opposed to sparing) of the native chordal apparatus leading to altered LV/septal geometry, thus impacting RV function... But not super confident about that assessment without additional views, since the stuff in your second clip looks a bit too hyperechoic for necochords (unless your surgeons are using different material than what I'm used to seeing)
Air embolus into the RCA?Nope, it's not a neochord. The reason the function is down in the RV and the inferior distribution of the LV is not because of a zebra. It's actually part of the common mnemonics used for things one has to verify before coming off pump
![]()
Bingo. That hyperechoic thing on the pap muscle in the first clips is a big chunk of air. This pt had massive left atrial enlargement and some LV dilation, and as much as we try to de-air, sometimes a bunch of residual air that was stuck high in the atrium or in the apex of a boggy LV makes it’s way through only after the pump flow is way down right before separation and more native contractility has returned. And it can be bad news bears.Air embolus into the RCA?
Best thing to do is return to bypass and let the heart rest until all the air has been pushed through and function has recovered a bit, get a bit of inotrope on board if the myocardium got stunned, and then try to separate again.
I just have to say that I love this. Thanks to those taking the time and energy to contribute to this thread. It's appreciated.
Rando clip
What are the types of ASDs? How can they be differentiated on echo?
This is likely a secundum ASD.Rando clip
![]()
What are the types of ASDs? How can they be differentiated on echo?
Other ASDs are primum ASD - lower on the interventricular septum close to the valves.
Sinus venosus ASD - usually more cephalad/superior on the interatrial septum and superior to the crista terminalis.
Coronary sinus ASD - associated with left SVC.
🤔 I think you meant IASThis is likely a secundum ASD.
Other ASDs are primum ASD - lower on the interventricular septum close to the valves.
also you missed one of the most common ones we see - iatragenic ASD.
Yes meant IAS.🤔 I think you meant IAS
also you missed one of the most common ones we see - iatragenic ASD.
Of course iatrogenic - patient history would be important.
🤔 I think you meant IAS
also you missed one of the most common ones we see - iatragenic ASD.
And sometimes people be dumb. People tend to forget that if a patient has a Mitral Clip or a LAA Occlusion Device (aka Watchman), they likely will have an Iatrogenic ASD.
You think that ASD could be from a mitral clip?
I’m not well enough versed in transseptal puncture specifics, but why couldn’t it be? It’s superior enough, perhaps a bit too anterior given proximity to the aorta, but tough to tell with only a 90 degree view. It does appear a bit bigger than what I would expect for mitraclip TSP, but certainly they can vary in size and enlarge over time
Way too anterior. 👊🏽
This was a secundum although it's not in that classic spot one expects. Is this ASD amenable to percutaneous closure? Why or why not?I’m not well enough versed in transseptal puncture specifics, but why couldn’t it be? It’s superior enough, perhaps a bit too anterior given proximity to the aorta, but tough to tell with only a 90 degree view. It does appear a bit bigger than what I would expect for mitraclip TSP, but certainly they can vary in size and enlarge over time
Also, as @sevoflurane says, this spot would've been wayyyyy too anterior for an interventional puncture. We know this because the ascending aorta is in the clip and is no more than a few mm away.
Makes sense. I had assumed you needed the 60 degree view to get a better sense of the anterior/posterior dimension. We don’t do The echo for structural stuff at my fellowship, so it’s not something that I have too much practical experience with.This was a secundum although it's not in that classic spot one expects. Is this ASD amenable to percutaneous closure? Why or why not?
Also, as @sevoflurane says, this spot would've been wayyyyy too anterior for an interventional puncture. We know this because the ascending aorta is in the clip and is no more than a few mm away.
That being said, even I know that this ASD doesn’t have enough of an anterior rim for perc closure (though I know a few cardiologists who would be crazy enough to try...)
D
deleted697535
One of the exclusion criteria for mitraclip is ias shorter than 4.5cm and thats because the tsp has to be at least 4.5 cm from the AoV to be able to steer down on the valve. So thats way too close to the aortic valve to be from a clip. I mean it could be by a clip operator that isnt the best...I’m not well enough versed in transseptal puncture specifics, but why couldn’t it be? It’s superior enough, perhaps a bit too anterior given proximity to the aorta, but tough to tell with only a 90 degree view. It does appear a bit bigger than what I would expect for mitraclip TSP, but certainly they can vary in size and enlarge over time
No, I just meant in general, an ASD could be iatrogenic.You think that ASD could be from a mitral clip?
Perhaps- I’m not disagreeing with your valid points here... Just pointing out fkr the sake of academic discussion that the aortic root and ascending aorta take a curvilinear, arching path over the dome of the left atrium. Without seeing the AV leaflets, esp at 90 degrees, you don’t know what part of the ascending aorta you’re seeing here- the actual valve (which is the anterior landmark) could be a few cm downOne of the exclusion criteria for mitraclip is ias shorter than 4.5cm and thats because the tsp has to be at least 4.5 cm from the AoV to be able to steer down on the valve. So thats way too close to the aortic valve to be from a clip. I mean it could be by a clip operator that isnt the best...
You're right, but separate from the valve landmark is also the operator trying not to hit the ascending aorta at any portion. And yes, while A to P dimension is usually measured at 40-60 degrees, the fact remains that we can see ascending aorta in the clip I posted. This means that the probe is probably not fully clocked right enough to generate a traditional bicaval with the SVC in view, but rather it's projecting a bit more anterior and thus the aorta is in view (as if you're about to generate a ME Asc Ao LAX)Perhaps- I’m not disagreeing with your valid points here... Just pointing out fkr the sake of academic discussion that the aortic root and ascending aorta take a curvilinear, arching path over the dome of the left atrium. Without seeing the AV leaflets, esp at 90 degrees, you don’t know what part of the ascending aorta you’re seeing here- the actual valve (which is the anterior landmark) could be a few cm down
Notice in anatomic orientation, the TSP needs to err in the posterior direction to avoid aorta.
Mid-esophageal AV short axis view showing a Bicuspid AV?
D
deleted697535
Sievers 0? No obvious raphes on that view.
It’s a bit hard to see but there is a raphe between the non and left.Sievers 0? No obvious raphes on that view.
What do you guys do if your 55yo pt is coming for a 3v CAB and you see this?
D
deleted697535
Oh yeah i see it now
Well good question.
1st - look for associated conditions. The precise cutoffs, who knows for sure but probably have to be moderate at least pre intervention
AI, AS (opens well so unlikely), root or ascending dilatation > 4cm, coarct but rare
If AI want to do MPR & detailed exam of valve to VAJ to Sinus to STJ to delineate El Khoury mechanism and assist in repair
LVEDD > 6.5cm
EF < 50
2 - Look at patient - is his operative risk very high?
Does he have a good cardiologist and will he follow up?
Is he a TAVI candidate
How big is the LVOT? What age is he? does he want a mechanical valve? If hes 20 and refuses warfarin then a bioprosthetic would fail in about 10 years so he will have 3 redo's before 50 if he makes it that far
3 - look at surgeon - can he repair an aortic valve?
CABG + AVRt is 6x short term mortality of CABG alone. Not to be sniffed at
All very difficult questions to answer on the fly and independently. We have good rapport with out cardiologists for patients that live in the city and sometimes even call them to the OR to look at these images to make an MDT decision intraop with the surgeon. Thats probably ideal
For patients transferred in from BFE we often see this. Its a total disaster
@Newtwo i would argue you’re making it too complicated. If the valve is stenotic or leaky to the point of meeting criteria for intervention, then replace it. If not, leave it alone and do the CABG (but sure, do a thorough exam to rule out coarct, aneurysm, etc).
Not all bicuspid aortic valves end up becoming problematic. BAV is not uncommonly noted at autopsy as an incidental finding... Plenty of BAVs will last a lifetime without causing issues.
As an academic point, I would point out that TAVR for BAV is far from established. The entire aortic root complex is congenitally abnormal and has weird distorted anatomy. While some patients may have suitable anatomy for perc intervention, many don’t- the majority of cardiologists I’ve spoken to aren’t thrilled about TAVR for most BAV patients. That being said, as the technology improves and the available arsenal of valves continues to expand, this is likely to change
You're absolutely right that we should look for associated conditions to make sure we're not missing anything.Oh yeah i see it now
Well good question.
1st - look for associated conditions. The precise cutoffs, who knows for sure but probably have to be moderate at least pre intervention
AI, AS (opens well so unlikely), root or ascending dilatation > 4cm, coarct but rare
If AI want to do MPR & detailed exam of valve to VAJ to Sinus to STJ to delineate El Khoury mechanism and assist in repair
LVEDD > 6.5cm
EF < 50
2 - Look at patient - is his operative risk very high?
Does he have a good cardiologist and will he follow up?
Is he a TAVI candidate
How big is the LVOT? What age is he? does he want a mechanical valve? If hes 20 and refuses warfarin then a bioprosthetic would fail in about 10 years so he will have 3 redo's before 50 if he makes it that far
3 - look at surgeon - can he repair an aortic valve?
CABG + AVRt is 6x short term mortality of CABG alone. Not to be sniffed at
All very difficult questions to answer on the fly and independently. We have good rapport with out cardiologists for patients that live in the city and sometimes even call them to the OR to look at these images to make an MDT decision intraop with the surgeon. Thats probably ideal
For patients transferred in from BFE we often see this. Its a total disaster
But first things are first. Even by that 3D shot one can see the orifice is wide open. His valve area and gradients were normal and he had no AI. If you look closely at the clip you can see though that there is a big ol' chunk of calcium on the RCC near the NCC/RCC commisure. It's almost certain he is going to have further degeneration of the valve.
But as Hork points out, we are going to get there at some point with TAVR for BAV (or improved minimally invasive technology for SAVR). Do the CAB, let the valve ride, and see what's popped up in 10 yrs.
D
deleted697535
Whats the difference between ME Aortic Short Axis and the RV inflow/outflow? If you can see a TV and PV is that automatically RV inflow/outflow?
Asking for a friend.
Many times the PV does not appear clearly in a ME AV SAX. In addition, you're typically not cutting the AV cusps perfectly en face in a RV IO.Whats the difference between ME Aortic Short Axis and the RV inflow/outflow? If you can see a TV and PV is that automatically RV inflow/outflow?
Asking for a friend.
From a broader anatomic standpoint, look at the following
A theoretically perfect RV IO beam simultaneously cuts directly through the TV septal-anterior leaflet commisure and through the PV left-right leaflet commisure. A perfect ME AV SAX does not when correctly focused on AV structures.
26yo F. Thoughts?
D
deleted697535
Wowza. Pe?
RV been dealing with both volume (L—>R) and pressure work for a while I imagine.More likely to be chronic pulmonary hypertension
Precisely.More likely to be chronic pulmonary hypertension
WHO group 1 PAH, on "triple therapy." Surprisingly still has pretty good functional status.
PA pressures on most recent RHC are 120s/50s (80s). Systemic pressure in pre-op is 90s/50s. First OR pressures were 80s/50s.
Here for a very minor procedure that is usually done in GYN clinic without any anesthetic. What do you want to do about it?
Do it like they do in gyn clinic without any anesthetic.Here for a very minor procedure that is usually done in GYN clinic without any anesthetic. What do you want to do about it?
Patiently reportedly is completely intolerant of any manipulation or exam. Gyn is concerned that cervical manipulation will cause her to vagal (apparently it's pretty common in clinic, especially in women who are higher anxiety). Patient has the inappropriate expectation of being "totally out."Do it like they do in gyn clinic without any anesthetic.
Would you ever consider a saddle block and just skip any major sedation?
Precisely.
WHO group 1 PAH, on "triple therapy." Surprisingly still has pretty good functional status.
PA pressures on most recent RHC are 120s/50s (80s). Systemic pressure in pre-op is 90s/50s. First OR pressures were 80s/50s.
Here for a very minor procedure that is usually done in a GYN clinic without any anesthetic. What do you want to do about it?
Combo minor gyne procedure and heart/lung transplant.
Lemme guess, not ideal airway/body habitus?
Book answer is nothing or full court press. But main thing is to maintain systemic pressures at at least baseline. She’s been living with this for awhile so she’s likely tolerated spikes in PVR regularly.
Titrate your amnestic/sedative du jour (perhaps touch of versed/ketamine combo) to mainly provide amnesia. Have push dose pressor and Epi handy as well as being ready to tube if badness happens to control PaCO2 but again, she sees spikes regularly and SBP (or more accurately DBP) maintenance is the key here.
She’ll do fine.
Versed, ketafol drip, +\- pressor du jour (Norepi would be the easiest choice) with Epi available in case things really hit the fan. Which won’t happen for a minor procedure usually done in the GYN office unless you do something that allows for systemic hypotension/significant hypoxia or hypercarbia that will precipitate RV ischemia and PH death spiral. Maintaining coronary perfusion pressure is the name of the game (as always)
Did we just become best friends?Versed, ketafol drip, +\- pressor du jour (Norepi would be the easiest choice) with Epi available in case things really hit the fan. Which won’t happen for a minor procedure usually done in the GYN office unless you do something that allows for systemic hypotension/significant hypoxia or hypercarbia that will precipitate RV ischemia and PH death spiral. Maintaining coronary perfusion pressure is the name of the game (as always)
YUP
Prop, sux, ecmo
Actually, quite thin, reassuring airway exam. What's not reassuring is that 1 yr ago, said individual underwent wisdom teeth removal under GA with what appeared to be a very reasonable, gentle anesthetic. 20 minutes in, she was started on 0.5 of milrinon and 0.07 of Epi and required numerous vaso boluses. All in all, I wanted to stay very far away from that.Lemme guess, not ideal airway/body habitus?
Book answer is nothing or full court press. But main thing is to maintain systemic pressures at at least baseline. She’s been living with this for awhile so she’s likely tolerated spikes in PVR regularly.
Titrate your amnestic/sedative du jour (perhaps touch of versed/ketamine combo) to mainly provide amnesia. Have push dose pressor and Epi handy as well as being ready to tube if badness happens to control PaCO2 but again, she sees spikes regularly and SBP (or more accurately DBP) maintenance is the key here.
She’ll do fine.
We did a spinal. 1mL of 0.75% heavy bupivacaine. Stayed sitting up for 3 minutes to get a nice saddle block (no lower extremity blockade appreciable at all). BP coasting 80s/50s (often normal for her). She had received 2mg midazolam and was totally unphased. BP continues to be good. crna gives 10mg propofol to see what kind of effect we get. Next BP 1 minute later is 60s/40s. She then got numerous small bumps of Epi and a couple units of vaso until BP stabilized. Man that sucked. Maybe that drop was related to the spinal? but it was quite delayed when we had previously had no changes. But 10mg propofol seems so unlikely to cause this profound of a drop. Honestly not certain.
Not gonna lie, doing a spinal (even a saddle) without an aline and then giving any amount of propofol to someone whose baseline sbp is 80/50 and whose baseline pap is 120 wouldn't have been my first plan.Actually, quite thin, reassuring airway exam. What's not reassuring is that 1 yr ago, said individual underwent wisdom teeth removal under GA with what appeared to be a very reasonable, gentle anesthetic. 20 minutes in, she was started on 0.5 of milrinon and 0.07 of Epi and required numerous vaso boluses. All in all, I wanted to stay very far away from that.
We did a spinal. 1mL of 0.75% heavy bupivacaine. Stayed sitting up for 3 minutes to get a nice saddle block (no lower extremity blockade appreciable at all). BP coasting 80s/50s (often normal for her). She had received 2mg midazolam and was totally unphased. BP continues to be good. crna gives 10mg propofol to see what kind of effect we get. Next BP 1 minute later is 60s/40s. She then got numerous small bumps of Epi and a couple units of vaso until BP stabilized. Man that sucked. Maybe that drop was related to the spinal? but it was quite delayed when we had previously had no changes. But 10mg propofol seems so unlikely to cause this profound of a drop. Honestly not certain.
One challenge was management of the patient's expectations. Plan was for the art line. She refused. So it turned into "art line and ultrasound available at bedside and if things go sideways it's going in."Not gonna lie, doing a spinal (even a saddle) without an aline and then giving any amount of propofol to someone whose baseline sbp is 80/50 and whose baseline pap is 120 wouldn't have been my first plan.
Pt sounds like a nightmare, however she didn’t refuse an awake IV, and an a-line with local and U/S is about as painful- so I’m hoping you all said “we need to do this relatively painless procedure for strict monitoring so we can increase the odds that you don’t die during this anesthetic because we’ll be immediately treating any instability stemming from your sick, sick-ass heart and lungs” .... and then pressed the issue repeatedly. Ultimately, she can refuse whatever she wants, but that doesn’t compel me to do an unsafe anesthetic without the monitors I deem necessary, especially for something that could be done in the office under local.One challenge was management of the patient's expectations. Plan was for the art line. She refused. So it turned into "art line and ultrasound available at bedside and if things go sideways it's going in."
The thing about the “ready at bedside plan” is that many times the RV ischemia vicious circle becomes intractable within seconds. She happened to respond to aggressive treatment after the fact, but that IMO is an outcome based on luck. Her pressure may have come up after treatment when her cuff was registering 60/40, but the next cuff cycling could’ve just as easily been weak pulsation followed dropping ETCO2- no matter how much epi and vaso you were giving.
You are not wrong. We pushed pretty hard. We discussed the previous anesthetic and the measures required to care for her. She described herself outright as a "difficult patient" which was more than true. We pushed the arterial line and went round and round without success. It was basically "only if I'm doing really really badly."Pt sounds like a nightmare, however she didn’t refuse an awake IV, and an a-line with local and U/S is about as painful- so I’m hoping you all said “we need to do this relatively painless procedure for strict monitoring so we can increase the odds that you don’t die during this anesthetic because we’ll be immediately treating any instability stemming from your sick, sick-ass heart and lungs” .... and then pressed the issue repeatedly. Ultimately, she can refuse whatever she wants, but that doesn’t compel me to do an unsafe anesthetic without the monitors I deem necessary, especially for something that could be done in the office under local.
The thing about the “ready at bedside plan” is that many times the RV ischemia vicious circle becomes intractable within seconds. She happened to respond to aggressive treatment after the fact, but that IMO is an outcome based on luck. Her pressure may have come up after treatment when her cuff was registering 60/40, but the next cuff cycling could’ve just as easily been weak pulsation followed dropping ETCO2- no matter how much epi and vaso you were giving.
This whole case stressed me out. I was dissatisfied with the progression of the events. Hard to provide the best care you can when the patient is not onboard. I appreciate the criticisms though, as I'm open to feedback so I can make it a better experience the next time.