
Seems pretty financially toxic to do that at a place like mdacc or sloane... Could easily be well into the 5 figuresI admittedly do not treat much breast... but it is 6 Gy x 5, right?
With this dose, it seems very reasonable to use more precise targeting and image guidance, and charge as such.
-
CycleTrack and SDN are teaming up to make medical school admissions more transparent and accessible! Read the announcement to learn how we’re supporting the future of CycleTrack’s free application-tracking tools .
You are using an out of date browser. It may not display this or other websites correctly.
You should upgrade or use an alternative browser.
You should upgrade or use an alternative browser.
Get help with your application
Use all the free resources available to you from SDN: articles, guides, expert advising, forums discussions, and school research.

you can charge for the image guidance w/ IMRT but not the SBRT 😉I admittedly do not treat much breast... but it is 6 Gy x 5, right?
With this dose, it seems very reasonable to use more precise targeting and image guidance, and charge as such.
Only freestanding i think?you can charge for the image guidance w/ IMRT but not the SBRT 😉
No, you can't even bill the prof IGRT on the SBRT because you get the higher prof for that SBRT codeOnly freestanding i think?
No i mean charge for igrt in imrt pts....No, you can't even bill the prof IGRT on the SBRT because you get the higher prof for that SBRT code
With IMRT the professional component of IGRT is billable but not the technical component I believe.
Unless in freestanding settingWith IMRT the professional component of IGRT is billable but not the technical component I believe.

This is so amazingly well-written and argued. Aside from the analysis of rad onc issues, I enjoyed the flow, the selection of words and the logic. You are talented.It's a fairly common attitude, especially in those who have mindlessly chugged along through the leftist academia machine without asking questions or notice the overt indoctrination and gaslighting. (take a look at the big rad onc woke twitterati names if you want to see the nauseating brainwashed end product of this pipeline)
America's cities are quickly becoming unlivable hellscapes. Yet somehow, the problem is with the blue collar workers in red states without 4 year degrees who have irritatingly somehow achieved a middle class life anyway with jumping through their hoops and are frustratingly difficult to get fired/cancelled if they disagree with you on social media.
Why anyone would actually WANT to live there as a rad onc is beyond me. So what's the alternative?
Anyway, let me give you a perspective from the exact opposite in nowhere-ville...
Hospital systems, especially rural hospital systems, only care about the short term. As in, how can we pay out as little as possible tomorrow, not how can we invest to make higher profits later and deliver higher quality care. As such, they will promise the world to naive young recruits. It's all smoke and mirrors. Large signing bonuses are tied back to 5-10 year repayment plans. wRVU bonuses are unattainable because wRVU numbers are fudged and you can't see the books, 4 day workweeks are promised but you show up and are told to work fridays anyway or else the patients can't get treatment, you are told you will have control over your clinic but your staff questions everything you do because they are used to locums doctors who don't care and do whatever they want and approve crappy plans, you discover 401(k) matches don't vest until being there for 5 years, there is an inappropriate reliance on midlevels to the point that they are considered equals and the term midlevel is banned, the staff are not replaceable because the hospital refuses to pay fair market wages to hire good outside talent and instead prefer to underpay whatever the local community college churns out, the EMR and IT are ancient bottom-dollar relics that hinder your producitivity, perks promised during recruitment (cellphone, housing/relocation assistance, recruitment bonuses for referring new doctors) are never delivered upon, and if you question any of this to the admin you will be patronized, gaslighted, and called a liar for calling them a liar. The fight to try and keep them honest is exhausting. They are penny-wise and pound-foolish and will gladly shoot themselves in the foot and go back to the locums model rather than give you even a fraction of the 8 figures of global you are generating for them.
There is basically nowhere to go in this field. There may be a few opportunities to start your own center, but those are rapidly evaporating as the large university systems try and establish monopolies in the states. Once that final plan has been realized, we will all be contour monkeys following their care pathways and having most of our professional fees skimmed off to support the inefficiencies of the system. Technical revenues? GTFO.
I can't imagine going into debt as a 22 year old now to pursue a career in medicine. In what field can you really hang out your own shingle and make your own way these days without the parasites leeching as much as they can off you without killing you? Psych maybe? I can't believe I gave up the prime decade of my life to end up more miserable than when I started. I went to medical school essentially to have a valuable hard-to-replace skill and not have to worry about getting laid off in corporate america. It turns out hospital systems are happy to save a buck on a "provider" who delivers lower quality care just the way corporate America will gladly outsource your job to China to save a fraction of a percent.
so you thought you had it made and were gonna make bank and it all turned out to be a total lie? Sad story but cannot say I am surprised. The field is so ripe with conmen, the weight of the fruits is breaking the branches. The smell of rotting fruit fills the air. Be very careful out there folks! Sometimes the swamp you know is the best swamp.
have heard THIS exact thing from two of my buddies who went private after residency. JanusI’ve seen this happen to people in PP too. The interview is all cheerful, democratic- we don’t stab each other in the back, we don’t steal your patients, everyone is involved with decisions in the practice, everyone partners on time- then decisions are made behind your back without your input controlling your life, patients are stolen from you or alternatively dumped on you (but oh we’re fair everyone gets the same pay- not fair when some people don’t work and others are driven like oxen), partnering is delayed...the hospitals have always done this crap, some toxic PP have always done it, but more and more people are going to get away with it for longer (meaning they will hold on to the doctors for longer because it will be harder for those doctors to make lateral moves) with a bad market....but at least in a larger city getting and holding onto strong physics is easier...again not saying all physicists in small towns are bad, just that they will be harder to replace if they are bad or they leave.
OK obviously my comment was sarcastic... cuz I get pretty teed off whenI think people have their preferences on whether they want to live in a big city, are agnostic, or specifically DON'T want to live in a big city. I believe having any of those 3 preferences does not inherently make you any sort of thing.
If people have a preference to live in a big city, that does not make them an evil person, just as a person who enjoys living in rural areas does not make them an evil person.
Regardless of your opinions and preferences on living and working in an urban, suburban, or rural environment, please do not directly insult other SDN members. One user warned.
so... if you look around in the spectacular stellar amazing spellbinding academic RVU-incentivising cancer centres around you... in the glamorous big cities... you will find PLENTY of pT1bN0M0 breasts receiving 50.4 Gy followed by a 2-week boosts... 15-day whole brains...I have zero concern with patients referring palliative RT cases to the community -why would I want to make a patient with metastatic cancer spend so much time traveling? With definitive or quasi-definitive cases, I have to concerns that occasionally cause me pause:
1) technology/physics support. Not all PP clinics by me have a 4D CT, not all use daily CBCT for thoracic/abdominal cases. Truth is, I know a few that are top notch, I know a few that have horror stories, and the rest are an unknown
2) I will often offer an aggressive/complex treatment with hypofractionated dose painting/SIB (usually in the context of a patient with a big tumor who can’t get chemo... or has oligoprogression). I can’t be certain that any other doctor (PP or academic) would offer the patient what I offered, because it is commonly “outside the box”. For some reason, these patients make up a decent chunk of my census and may actually be becoming my niche
I have no doubt (especially from conversations here) that there are some excellent physicians in private practice, many of whom are far better clinicians than myself... but there are some legit unknowns and I don’t have time to research every clinic in 100 mile radius.
I don’t know what the solution is. Maybe I should reach out to them or they should reach out to us. I just wanted to let you know that it isn’t “elitism”, at least speaking personally... it’s more that PP is a bit of a black box... and we can’t always be sure that another competent physician in a different practice would approach things the same way. If the patient wants a second opinion, that’s just fine... but often they want to feel like their whole team is in agreement.
you have to research EVERY and ANY doc you send your pt to. There are plenty of rad onc scum.

Technical revenues? GTFO.
This right here. Sums it up. My naïveté as a med student, resident, and fresh attending destroyed by knowing there is such a thing as technical revenues and knowing it is the bulk of the payment.
I thought there weren't as many radiation oncology crooks as that... my residency...My saddest experiences as a rotating student were from a chairman who should not have been teaching residents.
He would use metal needles in his Syed cases and had very poor understanding of the female anatomy and would routinely spear the rectum (as he put in all his needles blind in the OR without any CT or US guidance then would adjust in the CT sim). Couldn’t see anything in the mess of needles and no MRI fusion so he routinely ran dose through the needles in the rectum. He never saw his patients in follow up so always assumed he was perfect.
I rotated on Gyn Onc and saw all of the aftermath. One patient developed a fistula and got an exenteration. Then she got a nodal recurrence from a marginal miss of a tiny gross node.
Gyn onc doesn’t like awkward conversations thus the chairman still thinks he’s a great rad onc.
I am not happy to hear that patients far and wide are treated as poorly and badly as they were in my residency.
you are quite mistaken. A lot mistaken. A palliative consult is 200% more complex than a "regular one" - there is no prescription to follow. You have to incorporate evidence, pt prognosis, pt preferences - much more complex.Inpatient RadOnc consults are, on balance, a waste of time. A PA can do them. However, deep down, I kind of like going up there and pretending to be a real doctor.
A run-of-the mill cT1b breast... that I can do from my couch while laughing at the recent poll in the Red Journal and petting my dog
Yes rad Onc scum physicians are definitely everywhere and particularly so in competitive highly attractive large cities- with some PP (Chicago area and NOVA) opening up fellowships...I was however specifically referring to PHYSICISTS. They have way more options- so if you don’t have good physics in a small town or you lose good physics it is very hard to recruit them unless you pay well which many hospitals don’t want to do so (and even then it’s hard)...again not all small town physicists are like that- just saying a search for one can be very difficult)... rad Onc doctors are scummy everywhere. I was so naive in med school when I was starry eyed and thought they were so nice and cared so much about the cancer patients. But my post is not so useful- I’ve already stated both of these issues.OK obviously my comment was sarcastic... cuz I get pretty teed off when
so... if you look around in the spectacular stellar amazing spellbinding academic RVU-incentivising cancer centres around you... in the glamorous big cities... you will find PLENTY of pT1bN0M0 breasts receiving 50.4 Gy followed by a 2-week boosts... 15-day whole brains...
you have to research EVERY and ANY doc you send your pt to. There are plenty of rad onc scum.
D
deleted605854
The amount of self righteous nonsense on Twitter these days has reached lethal doses. In rad Onc and in other facets of life
I really wish Twitter would go the way of myspace
Sorry about that ,had to vent
I really wish Twitter would go the way of myspace
Sorry about that ,had to vent
Myspace disappeared because something worse came along.The amount of self righteous nonsense on Twitter these days has reached lethal doses. In rad Onc and in other facets of life
I really wish Twitter would go the way of myspace
Sorry about that ,had to vent
I still remember friendsterMyspace disappeared because something worse came along.
D
deleted605854
Myspace disappeared because something worse came along.
Good Lord, that sent a shiver down my spine.
What can I say except : "stay thirsty my friends"

Pretty good response rate!
I haven't read the paper in depth yet, but man - 16% either had only an offer (no contract) or no offer at all in May/June??? Obviously the timing of COVID probably played into that, but yikes. I'm also very curious about the 6% of people who didn't respond...my knee-jerk reaction to that is things might not have gone well for them and they were reluctant to immortalize that forever (similar to how most people aren't out here telling stories of their failures).
View attachment 317555
View attachment 317556
Pretty good response rate!
I haven't read the paper in depth yet, but man - 16% either had only an offer (no contract) or no offer at all in May/June??? Obviously the timing of COVID probably played into that, but yikes. I'm also very curious about the 6% of people who didn't respond...my knee-jerk reaction to that is things might not have gone well for them and they were reluctant to immortalize that forever (similar to how most people aren't out here telling stories of their failures).
Looking at these Tweets again, maybe the paper isn't out yet - they subtweeted an ARRO post about the Red Journal Editorial which was just published on Medical Education. Guess we need to wait for Virtual ASTRO 2020...
84% had a contract, of which, 89% were being honored.
That means 76% of respondents had "A" job to start upon graduation. No idea how many were fellowships or part time. Just A job.
That means 76% of respondents had "A" job to start upon graduation. No idea how many were fellowships or part time. Just A job.
Rad Onc, home of 24% unemployment for graduating residents.
Rad Onc, home of 24% unemployment for graduating residents.

View attachment 317555
View attachment 317556
Pretty good response rate!
I haven't read the paper in depth yet, but man - 16% either had only an offer (no contract) or no offer at all in May/June??? Obviously the timing of COVID probably played into that, but yikes. I'm also very curious about the 6% of people who didn't respond...my knee-jerk reaction to that is things might not have gone well for them and they were reluctant to immortalize that forever (similar to how most people aren't out here telling stories of their failures).
I mean I signed my contract in february. If I had waited longer I might've had the offer rescinded by mid March. So I'm not surprised that let's say 30% of residents had not signed by March, and only half of them were able to secure something by May/June in the midst of COVID.
Likely that most of 6% who didn't respond had a negative experience, but unable tos ay for sure. 94% RR on a survey from graduating residents.... but academic attendings will tell you everything is still just fine and that there's nothing to worry about.

but academic attendings will tell you everything is still just fine and that there's nothing to worry about.
Not all of us.
Had a medical student who is thinking about rad onc join me in clinic the other day. Medical student asked me about job market and we had a very brief discussion. I opened with:
"Did anyone else tell you there were job market issues?"
The response: "Yeah a couple people around here told me."
Residents and junior attendings are well in the know. This issue didn't just start this year.
I wish fellowships had not been counted in this survey as "jobs," even for those who elected to pursue them. I feel like when we talk about Rad Onc jobs, we're not talking about training that also happens to provide a salary. We don't say that med students are findings "jobs"...we say they match in residency.84% had a contract, of which, 89% were being honored.
That means 76% of respondents had "A" job to start upon graduation. No idea how many were fellowships or part time. Just A job.
I can hear the chorus now: Plenty of paying job opportunities for graduation Rad Onc residents!
Verbal slight of hand if those jobs opportunities are a bevy of new of predatory, unnecessary fellowships that pay $70,000/year
Fellowships = 💩I wish fellowships had not been counted in this survey as "jobs," even for those who elected to pursue them. I feel like when we talk about Rad Onc jobs, we're not talking about training that also happens to provide a salary. We don't say that med students are findings "jobs"...we say they match in residency.
I can hear the chorus now: Plenty of paying job opportunities for graduation Rad Onc residents!
Verbal slight of hand if those jobs opportunities are a bevy of new of predatory, unnecessary fellowships that pay $70,000/year
Did the same to a premed high school student doing bme major with an interest in RONot all of us.
Had a medical student who is thinking about rad onc join me in clinic the other day. Medical student asked me about job market and we had a very brief discussion. I opened with:
"Did anyone else tell you there were job market issues?"
The response: "Yeah a couple people around here told me."
Residents and junior attendings are well in the know. This issue didn't just start this year.
LOL.... I was going to post something about the above email from Comphealth Locums. I actually delved a bit further when I opened it yesterday.
Me:
I've actually started a permanent position in MehTown, USA. We actually don't have any needs right now since I filled out the practice but typically we can pick up the slack if needed.
Out of curiosity... how many doctors are out there looking for locums work?
Ruth from Comphealth:
We have a lot of residents from last year avail because of job freezes, Docs who have been furloughed and retired docs.
I cannot give you a exact # but we work with probably 100 docs actively at a given time.
TLDR: Ask your parents if they wouldn't mind letting you sleep in the basement or on the couch for a few years.
Did the same to a premed high school student doing bme major with an interest in RO
My score is 4 so far.
Not all of us.
Had a medical student who is thinking about rad onc join me in clinic the other day. Medical student asked me about job market and we had a very brief discussion. I opened with:
"Did anyone else tell you there were job market issues?"
The response: "Yeah a couple people around here told me."
Residents and junior attendings are well in the know. This issue didn't just start this year.
Sorry - you're right. SOME academic attendings.
I wish fellowships had not been counted in this survey as "jobs," even for those who elected to pursue them. I feel like when we talk about Rad Onc jobs, we're not talking about training that also happens to provide a salary. We don't say that med students are findings "jobs"...we say they match in residency.
I can hear the chorus now: Plenty of paying job opportunities for graduation Rad Onc residents!
Verbal slight of hand if those jobs opportunities are a bevy of new of predatory, unnecessary fellowships that pay $70,000/year
Do we know how many of those jobs are fellowships? If so, perhaps we could have lemmiwinks post the “corrected” job numbers.
Rad Onc, home of 24% unemployment for graduating residents.
I'll be gobsmacked if it's less than 20, which means ~10%. So real number could be 10+24 = 34% or more.Do we know how many of those jobs are fellowships? If so, perhaps we could have lemmiwinks post the “corrected” job numbers.
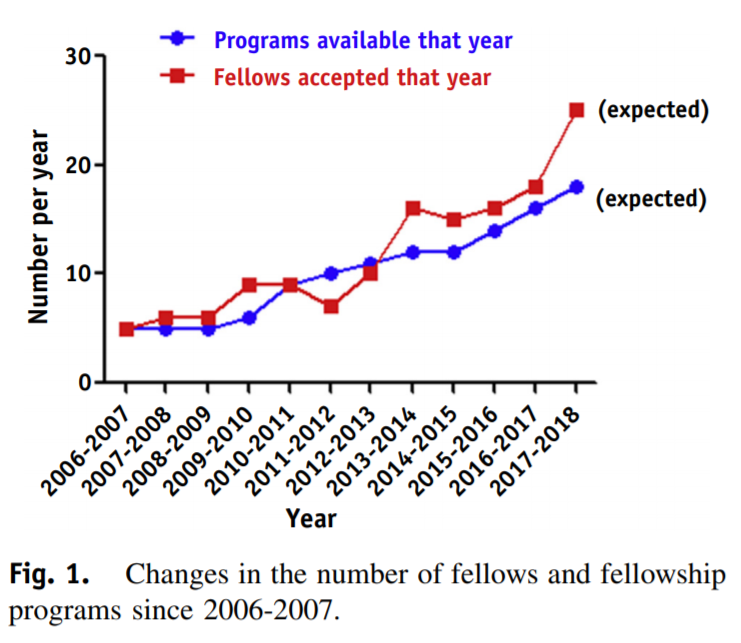
Do we know how many of those jobs are fellowships? If so, perhaps we could have lemmiwinks post the “corrected” job numbers.
Only 2 reported.
Perhaps some were 'instructor' positions paying 100-150k/year.
Only 2 reported.
Perhaps some were 'instructor' positions paying 100-150k/year.
You're saying 2/179 were fellowships (don't easily/readily see that). If so, fellowship numbers have fallen off a cliff, but why.

Fellowships = 💩
You see doo doo, chairs and PDs see delicious chocolate ice cream!
Seems highly unlikely. Would think between mskcc mdacc and Harvard would have more than that- will easily be able to verify on internet soonYou're saying 2/179 were fellowships (don't easily/readily see that). If so, fellowship numbers have fallen off a cliff, but why.
it's no big dealYou see doo doo, chairs and PDs see delicious chocolate ice cream!
so something's rotten in Denmark re: this data right off the batSeems highly unlikely. Would think between mskcc mdacc and Harvard would have more than that- will easily be able to verify on internet soon
You're saying 2/179 were fellowships (don't easily/readily see that). If so, fellowship numbers have fallen off a cliff, but why.
Ah, if they only had 2 people say they were going into Fellowships - I bet the other Fellows are in the non-responder category. There are definitely more than 2 RadOnc Fellows from that class, lol.
Seems highly unlikely. Would think between mskcc mdacc and Harvard would have more than that- will easily be able to verify on internet soon
I presume that most fellowship positions are not filled by American RO graduates. ALternate ABR pathway is valuable.
They had ~20 non responders nationwide TOTAL. Not so sure re: the 94% response rate. They had 179 responses, implying 179*(1/0.94)=190 residents total nationwide. I thought more than 190 graduated this year. Maybe 200? So maybe ~20 non-responders? I don't know. I can't immediately makes heads or tails of it, esp re: 2/179 "fellowship rate."Ah, if they only had 2 people say they were going into Fellowships - I bet the other Fellows are in the non-responder category. There are definitely more than 2 RadOnc Fellows from that class, lol.
They had ~20 non responders nationwide TOTAL. Not so sure re: the 94% response rate. They had 179 responses, implying 179*(1/0.94)=190 residents total nationwide. I thought more than 190 graduated this year. Maybe 200? So maybe ~20 non-responders?
Hopefully we get all the granular data after they present (I made my institution cough up the registration fee for me, so I can get the presentation if it's not published).
But, I would also assume around 200. If that assumption is not correct, that means a handful of people were not eligible for the survey, implying they left or were fired from residency? What other reasons could there be?
Obviously ARRO is usually amazing about being transparent with their methods so we'll only have to speculate till October 27th.
Even in the best days of the speciality, there were more than 2 American fellows- brachy, peds, protons etcI presume that most fellowship positions are not filled by American RO graduates. ALternate ABR pathway is valuable.
...Ruth from Comphealth:
We have a lot of residents from last year avail because of job freezes, Docs who have been furloughed and retired docs.
I cannot give you a exact # but we work with probably 100 docs actively at a given time.
TLDR: Ask your parents if they wouldn't mind letting you sleep in the basement or on the couch for a few years.
OK,
The solution is straightforward.
A surgeon told me this years ago: "We surgeons, we own the patients, we fix the problems we created...".
Since the job crisis is mfg'd by the many chairs/vice-chairs/PDs.
Whoever (chairs/vice-chairs/PDs) feeling that they are responsible for this job crisis should resign, effective immediately.
This should open up around 90-100 positions in the country.
This is a patriotic duty. In other words...
MROGA: Make Rad Onc Great Again!
I agree - something seems a little off with those numbers. I personally know three residents from two different but well-known Rad Onc programs who are now starting fellowship this month. I am wondering if ARRO maybe did not contact/could not reach all ACGME and ACR accredited Rad Onc residency programs? Seems unlikely, but it would explain that discrepancy; no way to "not respond" if you weren't contacted to begin with. At such a preliminary stage, I am just going to give ARRO the benefit of the doubt and assume that I'm not crunching the numbers correctly. Eagerly awaiting release of full methods and results @ ASTRO. I am very glad that this survey was done. It at least legitimizes the issue as something residents clearly care about.Hopefully we get all the granular data after they present (I made my institution cough up the registration fee for me, so I can get the presentation if it's not published).
But, I would also assume around 200. If that assumption is not correct, that means a handful of people were not eligible for the survey, implying they left or were fired from residency? What other reasons could there be?
Obviously ARRO is usually amazing about being transparent with their methods so we'll only have to speculate till October 27th.
Pessimistic prediction: Study results will give credence to worsening Rad Onc employment market, but much dismissal from the seniors in field that "job prospects no where near as bad as forecasted" and and passing the buck to the "extenuating circumstances" of COVID19 pandemic. Also no prior years for baseline comparison.
I want this same survey to be sent out to every graduating Rad Onc class from here on out, and potentially to PRIOR classes over the past 10 years.
They had ~20 non responders nationwide TOTAL. Not so sure re: the 94% response rate. They had 179 responses, implying 179*(1/0.94)=190 residents total nationwide. I thought more than 190 graduated this year. Maybe 200? So maybe ~20 non-responders? I don't know. I can't immediately makes heads or tails of it, esp re: 2/179 "fellowship rate."

2014-2015 Interview Gossip/Chit-Chat
I feel like having the interview Google Doc this year has taken the place of the annual interview gossip/chit-chat thread. Starting it in hopes of having a place for people to have casual conversation amid the craziness. Links to threads from previous years: 2013-2014 Interview...
 forums.studentdoctor.net
190 seems about right for graduates if the old google doc from that cycle is correct. Agree the fellowship rate is probably higher than 2/190, secondary to non-responders.
Last edited:
There’s quite obviously more than 2 fellows coming out. I hope ARRO fixes their analysis prior to presentation.
