Unsolicited Jobs Thread

Started by Gfunk6
This forum made possible through the generous support of SDN members, donors, and sponsors. Thank you.
Get help with your application

Use all the free resources available to you from SDN: articles, guides, expert advising, forums discussions, and school research.

Advertisement - Members don't see this ad
Not unreasonable under the right circumstances, but definitely will cost millions. If a hospital can't even offer contrast for sims it makes me question the general financial health of the hospital. Asking for an ROI on millions of dollars of capital investment is kinda business 101.
 
A hospital in this location needs to paying 600k+ to attract decent candidates, but it sounds like they want 2 docs, so the rvus just won’t be there. In this speciality, often rural places offer less rvus/consults while in just about every other field they offer more. Personally, I want to be busy in the middle of nowhere, not seeing 4 consults a week.
Cheyenne was paying low 500s I think.

But yes should be well over 600. You can make that in any decent sized Midwest city. Why would you go to BFE to make the same or less? They should be subsidizing heavily out of the technical to get you to 800-900. Unfortunately the locums market allows them to tread water until a sucker takes a low offer.

Edit: there is some naïveté on the part of new grads who expect to go to some podunk hospital and expect to immediately have all the same toys they had in training. It’s hard to understand just how poorly managed and financially troubled some of these places are. Yes the rad onc department makes a lot thru fat facility fees, but they are dependent on those to keep the lights on elsewhere.
 
Last edited by a moderator:
A hospital in this location needs to paying 600k+ to attract decent candidates, but it sounds like they want 2 docs, so the rvus just won’t be there. In this speciality, often rural places offer less rvus/consults while in just about every other field they offer more. Personally, I want to be busy in the middle of nowhere, not seeing 4 consults a week.
Which is where virtual/NP supervision makes a lot of sense here. 3 days on-site for the doc for $5-600k is a whole different ballgame
 
Advertisement - Members don't see this ad
Which is where virtual/NP supervision makes a lot of sense here. 3 days on-site for the doc for $5-600k is a whole different ballgame
Yup. If they’re not giving you some of the tech they should be open to 3 days on site for a sleepy clinic. Any sane administrator would make that deal in a second.
 
"Control. The non clinical admin want total control. Each physician has asked for the same things: patient safety, QI projects, building out cancer center (nurse navigator, tumor board, subspecialists)

Items rejected include cones for SRS, contrast for sim, DIBH, HN scopes since there's no ENT in town anymore, less call (rad onc is the safety blanket since no urgent neurosurgery or ortho spine), ACR accreditation, additional training for therapists and dosi, brachy afterloader, new CT sim.

If it has an upfront cost it needs an ROI. No ROI, then not happening."

I mean, I hate hospitals and hospitals ceos as much as anyone, but if all the docs are making demands like this of some community hospital in the middle of nowhere I'm not entirely surprised they were let go.
There's a huge difference of a request and a demand. Disposable scopes pay for themselves and without ENT in town it is essential to treat HN. The CT sim is ancient, does not have OMAR and RPM system is down most of the time. There was a brachy afterloader at end of life and without consulting the physician they decomissioned it and didn't get capital for a replacement. SRS cones were purchases 2.5 years ago and never installed because the physicist didnt know how and they didnt want to pay outside help. Identify surface guidance has been installed for 2 years and still no DIBH again because of no physics on site. ACR accreditation was being done and was 80% complete until both physicists left. They provide 26 days PTO but that doesnt count holidays, sick time or the occasional need to leave clinic a couple hours early for a car check etc. I took 1.5 weeks of actual vacation. So no, three physicians were not let go for demanding things. The last two left voluntarily breaking contracts early and paying back all the incentives.
 
Not unreasonable under the right circumstances, but definitely will cost millions. If a hospital can't even offer contrast for sims it makes me question the general financial health of the hospital. Asking for an ROI on millions of dollars of capital investment is kinda business 101.
Not questioning the ROI aspect or that 4 departments support the whole hospital. This radonc department did 15 million in revenue last year, 19k wRVU and cried about ROI for autocontouring (~$7k) when they were only paying a 0.8 FTE dosimetrist. CT sim wont have an ROI, but I did an ROI on already purchased cones, and they were hemorrhaging money.
 
Not questioning the ROI aspect or that 4 departments support the whole hospital. This radonc department did 15 million in revenue last year, 19k wRVU and cried about ROI for autocontouring (~$7k) when they were only paying a 0.8 FTE dosimetrist. CT sim wont have an ROI, but I did an ROI on already purchased cones, and they were hemorrhaging money.
I know of another rad onc department that purchased cones and never commissioned them. These themes are bizarre. Managerial incompetence.

I mean, you have just described the Spirit Airlines of rad onc. So and so's nephew just got a sweet deal on recycled hydraulic fluid from East Congo Airways liquidation. Too many mechanics are testing positive for meth, so going forward all random tests will be on the first of the month. Pilots aren't allowed to get the free pretzels to cut annual costs by $749.34 across the business. Actually, why is anyone getting pretzels? (Raise your hand if you've worked in a clinic where coffee cups were removed from the waiting room to save costs)...
 
I will never understand how so many people out there are objectively bad at their administration jobs and they somehow never get fired.

Those folks are entirely replaceable, more than any clinician. I’ve met very few non clinical administrators that seem to have real talent in this space.

And yet.
Have you met upper level admins who care more about appeasing the lower level managers than the doctors? I have.
 
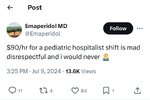
I guess we shouldn’t complain too much about $200-250/hr jobs… it could always get worse!
Jokes aside, pediatricians really deserve better.
 

Attachments

  • IMG_9317.jpeg
    IMG_9317.jpeg
    119.7 KB · Views: 157
I honestly think pediatricians deserve more money than RadOncs, and I think they will make more money than us eventually. We work 4 days a week and I am getting **** for questioning people about supervision. This field is cooked.
They will never get it. Kids don't vote. Peds, teachers etc get paid the lowest
 
Yeah dude, let this live in infamy.

This guy thinks RadOncs don't need to work. "Which is where virtual/NP supervision makes a lot of sense here. 3 days on-site for the doc for $5-600k is a whole different ballgame"-MedGator. This guy is a high earning RadOnc that wants RadOncs to work less, I agree, let's get RadOnc pay down.
Is that you Ralph W?
 
I honestly think pediatricians deserve more money than RadOncs, and I think they will make more money than us eventually. We work 4 days a week and I am getting **** for questioning people about supervision. This field is cooked.
Supervision boat sailed years ago. Why are you trying to beat the dead 🐴? Esp without evidence to back it up. Honest question. @NotMattSpraker posted earlier today that the general movement has been towards virtual in multiple specialties.
 
Yeah dude, let this live in infamy.

This guy thinks RadOncs don't need to work. "Which is where virtual/NP supervision makes a lot of sense here. 3 days on-site for the doc for $5-600k is a whole different ballgame"-MedGator. This guy is a high earning RadOnc that wants RadOncs to work less
Are you working "hard" when that last breast pt shows up, your clinic is over and you've run out of cat videos to watch on YouTube but you couldn't leave early to see that inpatient consult at the hospital because of "direct supervision" rules meant to allow us to graduate extra residents every year?
 
Advertisement - Members don't see this ad
Honestly Gator I love you, you're an awesome dude. Let's go through with this. RadOncs do make too much, pediatricians work very hard and I really do think Ralph was correct @medgator
With all the crap applicants pouring into this field today, can you imagine the kind of residents coming onboard when salaries fall in line with peds? In all honesty, radonc “deserves” more pay/less work presently given the risky future.
 
With all the crap applicants pouring into this field today, can you imagine the kind of residents coming onboard when salaries fall in line with peds? In all honesty, radonc “deserves” more pay/less work presently given the risky future.

It seriously feels like we are pro athletes. Will we make 7 figures for 2 years or 20? Will we have a career ending injury tomorrow and have to stretch our savings for the rest of our life? Will our only option after we blew all of our money on lambos and blackjack the first couple of years be moving to Kazakhstan to play semi pro ball for $30k/year?

Graduating residents taking low paying partnership track positions or prioritizing desirable locations at any cost are taking enormous risk. I wouldn't do it.
Residency expansion, hypofrac and ommission were enough of a black cloud before supervision appeared.
 
Graduating residents taking low paying partnership track positions or prioritizing desirable locations at any cost are taking enormous risk. I wouldn't do it.

This implies their only motivation should be money. For some, the improved quality of life that private practice or a desirable location can bring outweighs money. It seems that's not the case for many on this board, but I wouldn't discount that.
 
This implies their only motivation should be money. For some, the improved quality of life that private practice or a desirable location can bring outweighs money. It seems that's not the case for many on this board, but I wouldn't discount that.

It is true that some (many?) have the luxury of generational wealth and achieving financial independence is not a worry. I am also jealous that your experience in private practice came with improved quality of life. That was not my experience. If I were a 30-something starting out with negative 400k of net worth and non-wealthy parents, I would take the highest paying non-profit independent hospital job with tolerable admin I could, negotiate the loan assistance as a signing bonus and stay there until PSLF is done. But I'm risk averse, and nobody not independently wealthy going into rad onc these days is risk averse essentially by definition. So swing for the fences I guess.
 
It is true that some (many?) have the luxury of generational wealth and achieving financial independence is not a worry. I am also jealous that your experience in private practice came with improved quality of life. That was not my experience. If I were a 30-something starting out with negative 400k of net worth and non-wealthy parents, I would take the highest paying non-profit independent hospital job with tolerable admin I could, negotiate the loan assistance as a signing bonus and stay there until PSLF is done. But I'm risk averse, and nobody not independently wealthy going into rad onc these days is risk averse essentially by definition. So swing for the fences I guess.

I think anyone making 300-400k per year, even with 400k of educational debt, doesn't need to really worry long term about finances. You will not die in debt or with negative equity. You may not leave millions to your children, but you will be fine financially.

Private practice absolutely has come with a better lifestyle. I think there are always exceptions, but few on this board who have been employed, academic, and private would argue that they worked more as a private practice doc and had less freedom or autonomy.
 
With all the crap applicants pouring into this field today, can you imagine the kind of residents coming onboard when salaries fall in line with peds? In all honesty, radonc “deserves” more pay/less work presently given the risky future.
Sorry but this is such a trash take. Just because someone didn’t score 260 on the step 2 or didn’t graduate from Harvard doesn’t mean they’re “crap applicants”. There’s zero evidence showing higher step score correlates with becoming a better physican. Don’t **** on the applicants who are passionate about the field.
 
I think anyone making 300-400k per year, even with 400k of educational debt, doesn't need to really worry long term about finances. You will not die in debt or with negative equity. You may not leave millions to your children, but you will be fine financially.

Private practice absolutely has come with a better lifestyle. I think there are always exceptions, but few on this board who have been employed, academic, and private would argue that they worked more as a private practice doc and had less freedom or autonomy.

I guess I'm one of the few then. However I did not have technical ownership. Maybe we're comparing apples to oranges.

Edit: Arguing whether 300-400k/year indefinitely for a highly educated subspecialist physician starting a career in early 30s with 400k in debt in a VHCOL area like SF, SoCAL, NOVA, or NYC constitutes "financial fineness" does not seem like it's going to be productive.
 
Last edited by a moderator:
Sorry but this is such a trash take. Just because someone didn’t score 260 on the step 2 or didn’t graduate from Harvard doesn’t mean they’re “crap applicants”. There’s zero evidence showing higher step score correlates with becoming a better physican. Don’t **** on the applicants who are passionate about the field.
Some of the folks matching now can't even secure pgy1 positions and have had to take step exams multiple times to pass. Not sure what else you call that. EM and rad onc had the most unfilled slots going into the SOAP the last few years.

Psych used to be very uncompetitive 10-20 years ago and it has literally switched places with RO in terms of step scores of the matched candidates and difficulty in terms of matching
 
Sorry but this is such a trash take. Just because someone didn’t score 260 on the step 2 or didn’t graduate from Harvard doesn’t mean they’re “crap applicants”. There’s zero evidence showing higher step score correlates with becoming a better physican. Don’t **** on the applicants who are passionate about the field.
I am not universally condemning all applicants. there undoubtedly would be some passionate abt radonc among the specialty refugees. I am actually pretty passionate abt this field, but couldn’t see myself applying based on the existential job risk in 15-20 years. Even a 10-20% risk is disasterous in my opinion. Plenty of great specialties out there and it is hard to believe there is not a single other specialty that an applicant couldn’t embrace with similar passion. No one was born to be a radonc.
There are some terrible applicants in last several years and we are not talking an average step score from an average med schooll, who should make a fine radonc. Avg applicant may very well be equal in ability/ competency to “top” applicants (this has been my experience) but it does not follow for the bottom applicants.
 
Last edited:
I am not universally condemning all applicants. there undoubtedly would be some passionate abt radonc among the specialty refugees. I am actually pretty passionate abt this field, but couldn’t see myself applying based on the existential job risk in 15-20 years. Even a 10-20% risk is disasterous in my opinion. Plenty of great specialties out there and it is hard to believe there is not a single other specialty that an applicant couldn’t embrace with similar passion. No one was born to be a radonc.
There are some terrible applicants in last several years and we are not talking an average step score from an average med schooll, who should make a fine radonc. Avg applicant may very well be equal in ability/ competency to “top” applicants (this has been my experience) but it does not follow for the bottom applicants.
At this point, if you’re a med student and you’re tied to certain location or wants to live in big metro cities, you absolutely shouldn’t go into rad onc. But not everyone wants to live NYC, San Fran, Miami etc. let’s say you’re from Pittsburgh and okay with living within 1-2 hours, you can easily find a rad onc employed position that pays $500-600k for 4-5 days 8-4 with no calls! That’s literally dream job for many people! Also if you wanna go into academic, most places that I checked rad onc assistant professor gets paid more or equal to med onc, Rads, Anesthesiologist assistant professor. At the big university in my home town, rad onc assist prof salary is 1.5x of med onc assist prof.
As I said, there’s zero evidence showing any correlation between the step score, MD vs. DO, number of research or the med school prestige “rank” and how succesful of a physician someone becomes. So calling anyone “a crap applicant” is just disrespectful after all they’ve accomplished.

This has always and probably will always be true (assuming everyone gets a job). I hope people dont think geographic restriction goes away in "good" years.

The difference between a good and bad year for me has been if there is or is not a job in the city I want to live in. My graduation year was a bad year.
 
I think I've had this one emailed to me before, I bet it could be a really sweet gig if it's 3-4 days a week in the office:

Hello Dr. Gator

I hope you are having a great day!

If you are looking for ways to improve your work-life balance, live a laid-back Midwest lifestyle, receive great benefits and competitive pay (up to $653,000 includes $100,000 sign-on bonus) - MercyOne North Iowa Medical Center is the place for you!

Check out our hospital employed full-time BC/BE Radiation Oncology physician position we have available. There's some great info about the opportunity, compensation package, our organization / community and much more.

I'd love to learn more about your career goals/needs and thoughts on joining our team— any chance you have time next week to chat with Morgan Staley at 641-428-6631 to learn more about this amazing opportunity at MercyOne North Iowa?

Have a great day,

Sue Armour

MercyOne North Iowa Medical Center
1000 4th St. SW
Mason City, IA 50401
 
As I said, there’s zero evidence showing any correlation between the step score, MD vs. DO, number of research or the med school prestige “rank” and how succesful of a physician someone becomes. So calling anyone “a crap applicant” is just disrespectful after all they’ve accomplished.

What have they accomplished? You know, the DO applicants with low step scores from Caribbean med school with bad grades and no research papers? Fill me in on how to identify passionate trainees so I can recruit them when they graduate.
 
Advertisement - Members don't see this ad
The only thing missing from this ad is the fact that you get an additional 4 weeks off every year (along with the patients and staff) due to annual hurricane season which is only getting worse. Plus, even if you don't evacuate you can enjoy the warm weather and sunshine without electricity for a few days each time the hurricane knocks out the power lines.
 
The only thing missing from this ad is the fact that you get an additional 4 weeks off every year (along with the patients and staff) due to annual hurricane season which is only getting worse. Plus, even if you don't evacuate you can enjoy the warm weather and sunshine without electricity for a few days each time the hurricane knocks out the power lines.

The salary is also missing
 
The only thing missing from this ad is the fact that you get an additional 4 weeks off every year (along with the patients and staff) due to annual hurricane season which is only getting worse. Plus, even if you don't evacuate you can enjoy the warm weather and sunshine without electricity for a few days each time the hurricane knocks out the power lines.
Not quite the perk of the Career Center posted UNC satellite clinic in Smithfield, NC that comes replete with the smell, sounds, and runoff into ground water taste of hog slaughter. Most of your patients will have 8 or less fingers and a weird, novel virus from working the line. But at least, you also get to cover 4 other clinics in the division. Not main campus, of course.
 
Last edited:
Dude, they're looking for providers who put patients first. If you have to ask about money up front then this job is probably not for you.
I need to know how many consults are referred to the clinic and what the mix of cases is. Then we can negotiate a RVU rate. This is the most important information I need to know when evaluating a JOB. Is this a volunteer position? Who knows!
 
Dude, they're looking for providers who put patients first. If you have to ask about money up front then this job is probably not for you.
You forgot also move to the community (McAllen Texas) and live there and become engaged in local civic activities rotary club, volunteer your Saturdays to do local radio shows, etc). We’re holding out for the right fit for someone who wants to move here (far flung border town on the edge of Texas) and never leave because it’s heaven. Maybe you can go to the beach in Galveston for a week in July.
 
You forgot also move to the community (McAllen Texas) and live there and become engaged in local civic activities rotary club, volunteer your Saturdays to do local radio shows, etc). We’re holding out for the right fit for someone who wants to move here (far flung border town on the edge of Texas) and never leave because it’s heaven. Maybe you can go to the beach in Galveston for a week in July.

There looking for a candidate who wants to live rural and is satisfied with a low salary
 
I never understand people who take low salary jobs in VHCOL locations. $380k in Brooklyn, you might as well continue to live like a resident. Would you even be able to afford a 2+ bedroom house/apartment? International vacations? Semi luxury car? High 7-figure net worth after retirement?
 

Attachments

  • IMG_9365.jpeg
    IMG_9365.jpeg
    126.3 KB · Views: 163
Doctor couple
Wife/husband completing fellowship
People that think north Jersey is the boonies
Independently wealthy

I wonder what pagny pays med onc.
I looked at their other jobs postings… intersting!
Hem/Onc $300k
Gyn/Onc $340k
Gastroenterolgy $350k
Cardiologist $300k
Neuro-epilepsy $270k
General Ob/Gyn $270k
Neuro interventional radiologist $475k
Radiology - breast imaging $430k
Rheumatology $215k
Hospitalist $200k
PCCM $285k
Anesthesiologist $400k
 
Last edited:
Advertisement - Members don't see this ad
Gas: $480k in Manhattan NY
Rad onc: $500k Sterling CO (13k population, 2-hour drive to Denver)

How do I put it… this is … NOT good!

P.s. we really need a website like gaswork. Astro career website has more RT and hem onc jobs than rad onc!
 

Attachments

  • IMG_9383.jpeg
    IMG_9383.jpeg
    101.1 KB · Views: 219
  • IMG_9382.jpeg
    IMG_9382.jpeg
    135.4 KB · Views: 202
Gas: $480k in Manhattan NY
Rad onc: $500k Sterling CO (13k population, 2-hour drive to Denver)

How do I put it… this is … NOT good!

P.s. we really need a website like gaswork. Astro career website has more RT and hem onc jobs than rad onc!

PAGNY paying 300K for RO
Definitely not good
 
Gas: $480k in Manhattan NY
Rad onc: $500k Sterling CO (13k population, 2-hour drive to Denver)

How do I put it… this is … NOT good!

P.s. we really need a website like gaswork. Astro career website has more RT and hem onc jobs than rad onc!

503k + production is meaningless.

If this clinic does 18k wRVU/yr and will pay you $70/wRVU (min for ultra rural), the first number doesn’t matter. But…. They are probably doing 7-8 k wRVU. Brush up on your Netflix watching skills.

Look at an inflation calculator to see what these numbers were worth 4-5 years ago. We’ve all taken a 25% pay cut since then.
 
Brush up on your Netflix watching skills.
Wild that anyone would have a dream to become a doctor as a kid and try hard in junior high, take advanced classes in high school, go to college and do all the things necessary to get into med school, go to med school and almost kill yourself studying and working there, and then do a 5 year medical residency…

All so a person could get a job watching Netflix.

Soul crushing to a person if the person didn’t know that was the endgame. But a fair number of kids have to know this might be the endgame, now. And they’re still choosing the Netflix and the soul crushing! Again, wild.

Oh, one other observation. Supervision doesn’t save souls, it crushes them.