
-
CycleTrack and SDN are teaming up to make medical school admissions more transparent and accessible! Read the announcement to learn how we’re supporting the future of CycleTrack’s free application-tracking tools .
You are using an out of date browser. It may not display this or other websites correctly.
You should upgrade or use an alternative browser.
You should upgrade or use an alternative browser.
Is there any evidence Whipple's is better than doing nothing?
Started by bigman1

Get help with your application
Use all the free resources available to you from SDN: articles, guides, expert advising, forums discussions, and school research.
Advertisement - Members don't see this ad
I thought overall survival was less than 20% at 5 year mark for all stages head of pancreas.
Where are we in the sabr area for pancreas?
Are you a med student or something? Please don’t tell me your an RO hopeful.
There’s no hope for radiation in pancreatic cancer. That simply isn’t the case with surgery they only known modality with any long term prospect of curr.
No, I'm an RO.Are you a med student or something? Please don’t tell me your an RO hopeful.
There’s no hope for radiation in pancreatic cancer. That simply isn’t the case with surgery they only known modality with any long term prospect of curr.
Never seen anyone cured by Whipple's. Just see immediate relapse. Now whats the current data on sabr pancreas equivalence?

As a RO, you’ll probably only see unresectables, progressions after chemo and local failures. We don’t add anything in the curative adjuvant setting per every study done in the last 30 years so you won’t see those cases anymore (unlike maybe 10 years ago). RT just doesn’t work very well in ablating pancreatic ca but can be useful in a palliative setting especially if chemo options have been exhausted.

The only long term survivors of pancreatic adeno are Whipple patients … they’re not common, but surgery patients have significantly better survivals (and institution doing the Whippling matters too)Or that surgery for that matter alters outcome in upper GI?
Not trolling here at all.
If we are going to give RT zero credit should we also state the obvious?
I've seen some good control 1-2 years out with chemo rt, eventually they all fail and met out though. It's basically aggressive palliation without surgeryAs a RO, you’ll probably only see unresectables, progressions after chemo and local failures. We don’t add anything in the curative adjuvant setting per every study done in the last 30 years so you won’t see those cases anymore (unlike maybe 10 years ago). RT just doesn’t work very well in ablating pancreatic ca but can be useful in a palliative setting especially if chemo options have been exhausted.
no level 1 evidence, but Whipple is better than nothing for the head of the panceeas and distal bile duct.
Ampullary cancers s/p Whipple have excellent outcomes.
Ampullary cancers s/p Whipple have excellent outcomes.
Ive seen a few ampullary that were managed trimodal and all alive.no level 1 evidence, but Whipple is better than nothing for the head of the panceeas and distal bile duct.
Ampullary cancers s/p Whipple have excellent outcomes.
No one is answering me though about the large trials now showing sabr is proving likely equivalence.
Ive seen a few ampullary that were managed trimodal and all alive.
No one is answering me though about the large trials now showing sabr is proving likely equivalence.
There aren’t any and you should know this.
There aren’t any and you should know this.

MASTERPLAN
mFOLFIRINOX And STEreotactic body Radiotherapy (SBRT) for Pancreatic cancer with high-risk and Locally Advanced disease (MASTERPLAN): a multicentre, randomised phase II study.
 gicancer.org.au
Are you trolling me?

Stereotactic ablative radiotherapy (SABR) as primary, adjuvant, consolidation and re-treatment option in pancreatic cancer: scope for dose escalation and lessons for toxicity - Radiation Oncology
Background Stereotactic ablative radiotherapy (SABR) offers an alternative treatment for pancreatic cancer, with the potential for improved tumour control and reduced toxicity compared with conventional therapies. However, optimal dose planning and delivery strategies are unelucidated and...
 ro-journal.biomedcentral.com
MASTERPLAN
mFOLFIRINOX And STEreotactic body Radiotherapy (SBRT) for Pancreatic cancer with high-risk and Locally Advanced disease (MASTERPLAN): a multicentre, randomised phase II study.
Are you trolling me?
Stereotactic ablative radiotherapy (SABR) as primary, adjuvant, consolidation and re-treatment option in pancreatic cancer: scope for dose escalation and lessons for toxicity - Radiation Oncology
Background Stereotactic ablative radiotherapy (SABR) offers an alternative treatment for pancreatic cancer, with the potential for improved tumour control and reduced toxicity compared with conventional therapies. However, optimal dose planning and delivery strategies are unelucidated and...
Are you delusional…this is hardly proof of anything.
A series that size is all you will get unless you are in a fantasy land where you think upper GI surgeons are going to play ball. Results are encouraging.Are you delusional…this is hardly proof of anything.
Given the massive QOL hit from surgery, why aren't you interested in a larger scale trial?
A series that size is all you will get unless you are in a fantasy land where you think upper GI surgeons are going to play ball. Results are encouraging.
Given the massive QOL hit from surgery, why aren't you interested in a larger scale trial?
Why are you asking questions that you already know the answer to?
Advertisement - Members don't see this ad
You are not wrong, just naive. To your point, a Whipple is an extremely morbid procedure and even with it the vast majority of patients eventually recur. It’s fair to question how many patients actually benefit from a Whipple and question the cost/benefit ratio. In that respect, a less morbid alternative is appealing so there is an opening. However, the hurdle is there is no denying that long term survival is seen in about 20% of resected patients and <5% (and that’s being very generous) of unresected patients. Based on the recent PRODIGE data, that ratio in resectable patients may favor surgery even more in the FOLFIRINOX era. If you were a patient in otherwise good condition and had a resectable tumor and a good surgeon would you decline surgery? I wouldn’t. Most of my Whipple patients end up doing pretty well functionally after about 4-6 weeks of recovery.A series that size is all you will get unless you are in a fantasy land where you think upper GI surgeons are going to play ball. Results are encouraging.
Given the massive QOL hit from surgery, why aren't you interested in a larger scale trial?
Testing an alternative to the best known curative therapy requires an extremely high quality rationale which doesn’t yet exist. Even if you got the surgeons to play ball your accrual would probably be very low to non existent. You have to start in the unresectable/borderline group and go from there. And in that setting, a lot is happening. Dose escalated SBRT, SBRT + radio protectors, chemorads followed by IRE, etc. if one of those dramatically improved survival and shows robust, long term local control we might have a testable alternative to surgery. Until then, your not going to see anything vs surgery for resectable patients.
D
deleted1111261
Hmm
Idk. In the early 90s, no thought that RT would replace surgery for early stage lung. Im not saying same, but you have to have some perspective. No one considered that sbrt would allow for 90% local control and survival rivaling surgery.
It takes cowboys/cowgirls (cowx?)
Idk. In the early 90s, no thought that RT would replace surgery for early stage lung. Im not saying same, but you have to have some perspective. No one considered that sbrt would allow for 90% local control and survival rivaling surgery.
It takes cowboys/cowgirls (cowx?)
And good data in patients not eligible for surgery. It’s a great analogy.It takes cowboys/cowgirls (cowx?)

Chris Crane hypofrac regimen is the only pancreatic RT regimen with an ablative dose for unresectable patients.
Is ablative the same thing as curative? If it’s cured, is it ablated? Has a person with unresectable pancreatic adeno ever been cured with RT monotherapy? What is his or her name?
I have 3 patients alive > 5 years after presenting with metastatic disease and getting chemo and RT only. Only 1 of them is NED. I obviously can't give you names. But I will also argue this isn't evidence of anything special regarding chemo or radiation in particular. This is just evidence that some people have good biology. What we need is good evidence of spectacular local control in a majority of patients with some intervention. I think its possible. Just hasn't happened yet.Is ablative the same thing as curative? If it’s cured, is it ablated? Has a person with unresectable pancreatic adeno ever been cured with RT monotherapy? What is his or her name?
Oh now we are curing local AND metastatic pancreatic cancer with local RT 😉I have 3 patients alive > 5 years after presenting with metastatic disease and getting chemo and RT only. Only 1 of them is NED. I obviously can't give you names. But I will also argue this isn't evidence of anything special regarding chemo or radiation in particular. This is just evidence that some people have good biology. What we need is good evidence of spectacular local control in a majority of patients with some intervention. I think its possible. Just hasn't happened yet.
I actually just wanted to know the name of the person who got cured of M0 pancreatic cancer with RT. Now I know there is also a person who got cured of metastatic pancreatic cancer with RT (and chemo, so it’s tough to know if RT did anything imho).
But all facetiousness aside and in all honesty, we don’t cure pancreatic cancer with SABR do we? We don’t cure metastatic pancreatic cancer with SABR do we? (We might “ablate,” which is a term I hate for its subjectivity and not actually reflecting what radiotherapy does… but do we cure?) And if you think we do or have enthusiasm we will, then you should think we do or have enthusiasm we will not just for bread and butter pancreatic adenocarcinomas but for ampullaries and the kind Steve Jobs had too. Shouldn’t the latter be on the cowx radar more so than those stubborn routine pancreatic adnocarcinomas?
The OP asked if there’s any evidence Whipple is better than nothing. The answer is yes. Is there any evidence SABR is better than/equivalent to a Whipple? No, and it’s not even close.
Last edited:

Just saw a note from a med onc on a patient treated with Whipple/CTX 3 yrs ago and still NED, so they are out there.
I think he had series of 20% survival 5 years out ?Chris Crane hypofrac regimen is the only pancreatic RT regimen with an ablative dose for unresectable patients.
Here is an OS I randomly pulled from one of Crane's efforts. Twenty percent survival @5y in unresectable would be pretty amazing. But even if true. It's one guy. At one place. Is anyone else replicating 20% 5y OS in unresectable? I don't even know if a trial of SABR in Whipple-able, pylorus-sparing*-pancreaticoduodenostomy-able patients would have equipoise.I think he had series of 20% survival 5 years out ?
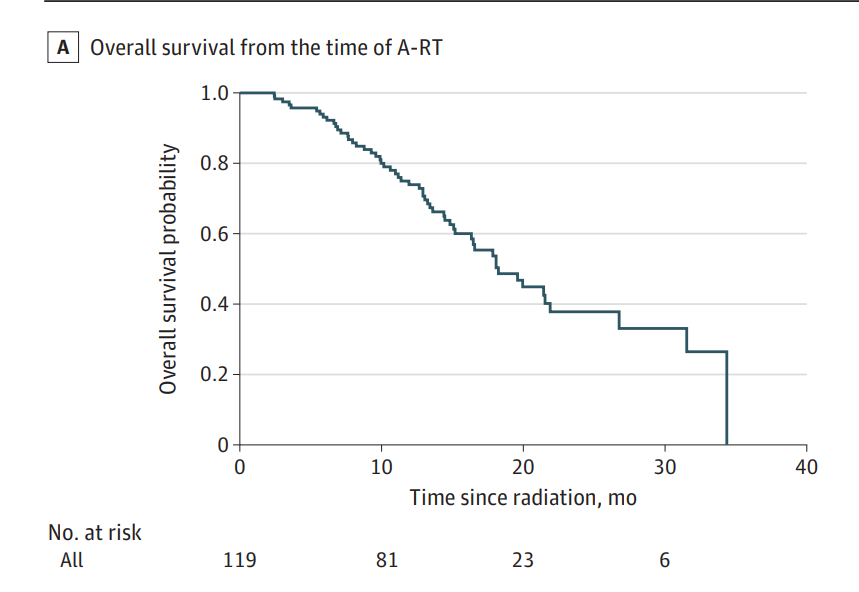
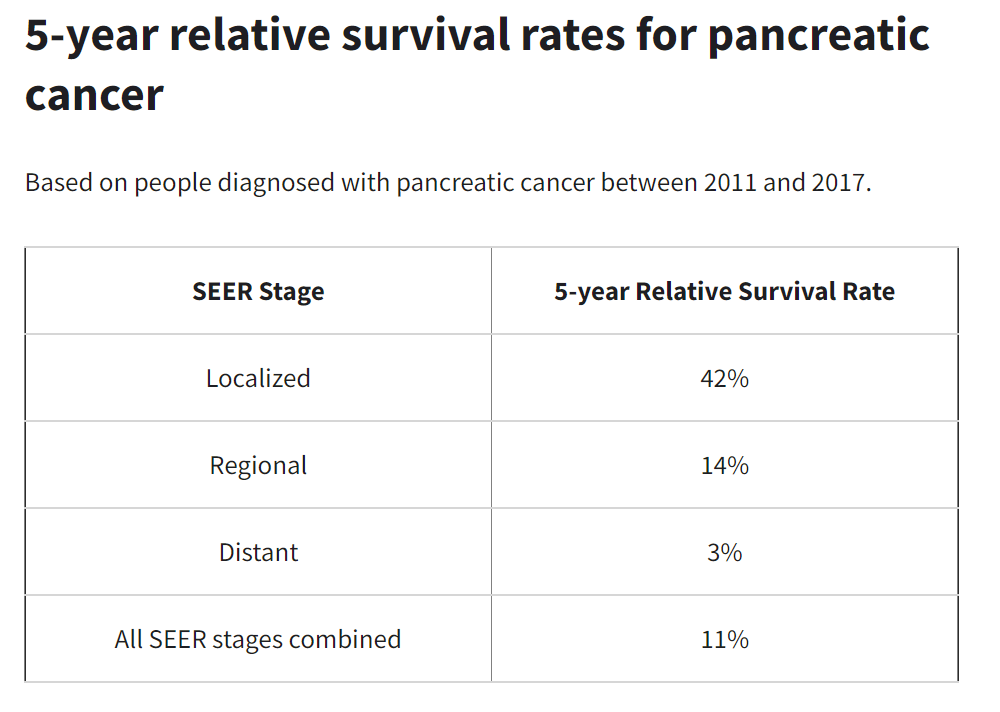
* make sure your surgeons do this
Last edited:
Here is an OS I randomly pulled from one of Crane's efforts. Twenty percent survival @5y in unresectable would be pretty amazing. But even if true. It's one guy. At one place. Is anyone else replicating 20% 5y OS in unresectable? I don't even know if a trial of SABR in Whipple-able, pylorus-sparing*-pancreaticoduodenostomy-able patients would have equipoise.
* make sure your surgeons do this
Admittedly that would be revolutionary…but it’s not gonna happen. Real solid prospective comparisons are just not in the cards. The closest we’re gonna get are matched control or whatever
No, you don’t have equipoise now. You are nicely making my argument here. There is very limited data that maybe, there is a chance something could rise to the 20-30% range in a prospective controlled trial and get us there. Honestly, would probably need to be better than that but that’s getting into the details. At this point there is nothing that rises to that level. But my point to the OP is there are a lot of trials in unresectable that might eventually get us there. And that is where we have to start. We have essentially no proven role in the resectable setting at all. No cooperative group or IRB is going to sign on for an RT vs surgery trial. Nor should they at this point.Here is an OS I randomly pulled from one of Crane's efforts. Twenty percent survival @5y in unresectable would be pretty amazing. But even if true. It's one guy. At one place. Is anyone else replicating 20% 5y OS in unresectable? I don't even know if a trial of SABR in Whipple-able, pylorus-sparing*-pancreaticoduodenostomy-able patients would have equipoise.
* make sure your surgeons do this
I won’t even call it a wager. If we ever have a >100 patient published series in unresectable pancreatic cancer where high dose radiotherapy is a local treatment and the 5y OS is 20% or better, I will pay you and the OP a hundred bucks. If an immunotherapy is a component of treatment in said such hypothetical future series, I will pay you a dollar.No, you don’t have equipoise now. You are nicely making my argument here. There is very limited data that maybe, there is a chance something could rise to the 20-30% range in a prospective controlled trial and get us there. Honestly, would probably need to be better than that but that’s getting into the details. At this point there is nothing that rises to that level. But my point to the OP is there are a lot of trials in unresectable that might eventually get us there. And that is where we have to start. We have essentially no proven role in the resectable setting at all. No cooperative group or IRB is going to sign on for an RT vs surgery trial. Nor should they at this point.
D
deleted1116990
Huh?showing sabr is proving likely equivalence.
You cannot get enough dose in with SBRT without a serious risk of fatal duodenal toxicity. Your only choice is the 75 in 25 regimen with Xeloda if you want to try and ablate it and even that is risky.
5 yr OS 18% unresected. Wallrus almost owes me a hundo.
D
deleted1111261
I’m in for a $100 if ablative RT without immune can treat resectable pancreatic cancer and achieve 20% survival
Advertisement - Members don't see this ad
*Whew* (wipes forehead)Huh?
You cannot get enough dose in with SBRT without a serious risk of fatal duodenal toxicity. Your only choice is the 75 in 25 regimen with Xeloda if you want to try and ablate it and even that is risky.
5 yr OS 18% unresected. Wallrus almost owes me a hundo.
Did you see that KM though:
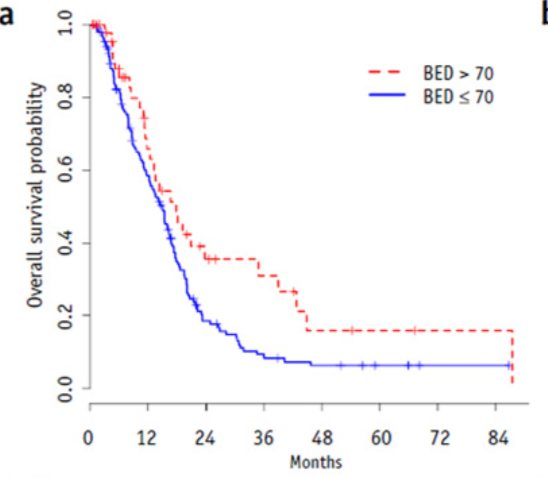
If just one more dude in the BED>70 arm had died at t>=~47mos, that 18% woulda went to hell. That's what I call:
Count me in the camp that “buys in” for dose escalation crane style treatment helping in cholangio or maybe HCC.
Not convinced on pancreas yet.
Not convinced on pancreas yet.
*Whew* (wipes forehead)
Did you see that KM though:
If just one more dude in the BED>70 arm had died at t>=~47mos, that 18% woulda went to hell. That's what I call:
Spot on! When the number of eligible pts at the right side of your survival curve is in the single digits, ignore!!! This data indicates that there may be a survival benefit in the 2-4 year window. There is no meaningful 5 year data here.
Don't even think about those 40-60 pt prospective trials!!
I have one long term survivor from 75/25Count me in the camp that “buys in” for dose escalation crane style treatment helping in cholangio or maybe HCC.
Not convinced on pancreas yet.
As the old "joke" in long-term survivors in GBM goes... I wanna see the path review 😉I have one long term survivor from 75/25
But maybe more importantly I want to have the courage, based on more results, to try this approach in my own patients. Aiming 75 Gy in 25 fractions into the upper abdomen near stomach and bowel would have been considered... tantamount to homicide about 20y ago. So I just want a little more clarity before I try it for the first time.
This data indicates that there may be a survival benefit in the 2-4 year window. There is no meaningful 5 year data here.
5yr OS 18% (95% C.I.: 0-68%)5 yr OS 18% unresected. Wallrus almost owes me a hundo.
fixed it
Last edited:
D
deleted1111261
This is pretty good!I have one long term survivor from 75/25
D
deleted1111261
that paper is showing 31% survival at 3 years for unresectable patients (per methods).
I believe this is better than 50.4+chemo. I've used it. Safe if done properly.
But to think that modern dose escalated RT leads to survival that is nearly the same as resectable pancreatic cancer treated with surgery + chemotherapy, this is hard to .. uh .. stomach.
I believe this is better than 50.4+chemo. I've used it. Safe if done properly.
But to think that modern dose escalated RT leads to survival that is nearly the same as resectable pancreatic cancer treated with surgery + chemotherapy, this is hard to .. uh .. stomach.
I thought overall survival was less than 20% at 5 year mark for all stages head of pancreas.
Where are we in the sabr area for pancreas?
Yeah, in this universe, unresectable will never approach the survival of resectable. But correct me if I'm wrong @bigman1, that was not your premise. I think the premise of the OP was flawed ("I thought overall survival was less than 20% at 5 year mark for all stages head of pancreas"). While resectable pancreatic adenoCA is itself a not common entity, within that group long-term survivors are not that uncommon (if you believe the American Cancer Society e.g.). Not to be a wet dishrag, but the 95% C.I. on that 31% 3y OS would overlap with published chemo-only or chemoRT survivals (roughly only about 10 patients in the BED>70 arm were available for events/censoring by the 3y mark and were the basis for the 31% metric).that paper is showing 31% survival at 3 years for unresectable patients (per methods).
I believe this is better than 50.4+chemo. I've used it. Safe if done properly.
But to think that modern dose escalated RT leads to survival that is nearly the same as resectable pancreatic cancer treated with surgery + chemotherapy, this is hard to .. uh .. stomach.
Last edited:
Take with a grain of salt but 20% overall survival was with adjuvant 5fu. I thought latest trials adding adjuvant xeloda + gem and (maybe folfirinox), we are now in the low 30s?Yeah, in this universe, unresectable will never approach the survival of resectable. But correct me if I'm wrong @bigman1, that was not your premise. I think the premise of the OP was flawed ("I thought overall survival was less than 20% at 5 year mark for all stages head of pancreas"). While resectable pancreatic adenoCA is itself a not common entity, within that group long-term survivors are not that uncommon (if you believe the American Cancer Society e.g.). Not to be a wet dishrag, but the 95% C.I. on that 31% 3y OS would overlap with published chemo-only or chemoRT survivals (roughly only about 10 patients were available for events/censoring by the 3y mark).
Maybe so re: 30%, but I don't think SABRing has synergized or "caused" that ~30% has it? And it's 30% @5y?Take with a grain of salt but 20% overall survival was with adjuvant 5fu. I thought latest trials adding adjuvant xeloda + gem and (maybe folfirinox), we are now in the low 30s?
D
deleted1116990
It is a quite sophisticated technique MSKCC uses with adaptive replanning. They have published on the specifics of it.But maybe more importantly I want to have the courage, based on more results, to try this approach in my own patients. Aiming 75 Gy in 25 fractions into the upper abdomen near stomach and bowel would have been considered... tantamount to homicide about 20y ago. So I just want a little more clarity before I try it for the first time.
I meant adding more active chemo adjuvantly following the whipped. For unresectable pancreas,we have 50 years of evidence that 50.4 does nothing, and some good data from Chris crane that his approach has better than 0 activity, so I use it. Probably have given it to 15 pts so far. Also the volumes from mskcc, they are huge- he is not skimping on anything. Very little toxicity in my experience.Maybe so re: 30%, but I don't think SABRing has synergized or "caused" that ~30% has it? And it's 30% @5y?
Last edited:
Definitely not for the faint of heartIt is a quite sophisticated technique MSKCC uses with adaptive replanning. They have published on the specifics of it.
Ding ding ding. I hinted at this earlier when I said something about probably better would be needed post-PRODIGE. If we are really going to get into the weeds determining equipoise in these very different populations is no simple task. Its hard to compare OS in patients who are resectable vs unresectable given the stark differences in survival between the groups. Doing something with focal therapy (no doubt combined with systemic therapy) to get 20% 5 year OS in unresected patients is a much bigger deal than getting a similar outcome in the resectable setting. Just compare the absolute improvements in survival with FOLFIRINOX in the advanced vs early adjuvant settings. What bar should we be looking for? And if the real question is can SBRT or any form of dose-escalated RT (or whatever experimental therapy is being tried) really be considered ablative, specific evaluation of local control has to be a critical part of that. I obviously don't have the answers as to what we would need. But I can confidently say that even though I like a lot of the approaches being tried and think they have some potential in the unresectable setting, I have seen nothing even close to compelling enough that I would recommend trying it as an alternative to surgery for a friend or loved one.Take with a grain of salt but 20% overall survival was with adjuvant 5fu. I thought latest trials adding adjuvant xeloda + gem and (maybe folfirinox), we are now in the low 30s?
Anecdotally, the minimally invasive whipples have really improved hospital stays over my career. Have an incredibly talented surgeon right now who has 80 year olds out of the hospital within 4-5 days. Also had some pts operated on by lillemoe and they were barely in the hospital.
Advertisement - Members don't see this ad
Ding ding ding. I hinted at this earlier when I said something about probably better would be needed post-PRODIGE. If we are really going to get into the weeds determining equipoise in these very different populations is no simple task. Its hard to compare OS in patients who are resectable vs unresectable given the stark differences in survival between the groups. Doing something with focal therapy (no doubt combined with systemic therapy) to get 20% 5 year OS in unresected patients is a much bigger deal than getting a similar outcome in the resectable setting. Just compare the absolute improvements in survival with FOLFIRINOX in the advanced vs early adjuvant settings. What bar should we be looking for? And if the real question is can SBRT or any form of dose-escalated RT (or whatever experimental therapy is being tried) really be considered ablative, specific evaluation of local control has to be a critical part of that. I obviously don't have the answers as to what we would need. But I can confidently say that even though I like a lot of the approaches being tried and think they have some potential in the unresectable setting, I have seen nothing even close to compelling enough that I would recommend trying it as an alternative to surgery for a friend or loved one.
We would basically have to find a health system willing to do this randomization. One that’s desperate enough to cut costs. Maybe Ukraine?
I mean short course RT even for patients that adamantly refuse surgery or something but are totally resectable.
Sounds like you are saying exactly what I am saying.You are not wrong, just naive. To your point, a Whipple is an extremely morbid procedure and even with it the vast majority of patients eventually recur. It’s fair to question how many patients actually benefit from a Whipple and question the cost/benefit ratio. In that respect, a less morbid alternative is appealing so there is an opening. However, the hurdle is there is no denying that long term survival is seen in about 20% of resected patients and <5% (and that’s being very generous) of unresected patients. Based on the recent PRODIGE data, that ratio in resectable patients may favor surgery even more in the FOLFIRINOX era. If you were a patient in otherwise good condition and had a resectable tumor and a good surgeon would you decline surgery? I wouldn’t. Most of my Whipple patients end up doing pretty well functionally after about 4-6 weeks of recovery.
Testing an alternative to the best known curative therapy requires an extremely high quality rationale which doesn’t yet exist. Even if you got the surgeons to play ball your accrual would probably be very low to non existent. You have to start in the unresectable/borderline group and go from there. And in that setting, a lot is happening. Dose escalated SBRT, SBRT + radio protectors, chemorads followed by IRE, etc. if one of those dramatically improved survival and shows robust, long term local control we might have a testable alternative to surgery. Until then, your not going to see anything vs surgery for resectable patients.
His name
His name was Joey Jo Jo...Shabadoo.Is ablative the same thing as curative? If it’s cured, is it ablated? Has a person with unresectable pancreatic adeno ever been cured with RT monotherapy? What is his or her name?
Yes sir, thats what I mean to say. Thank you.Yeah, in this universe, unresectable will never approach the survival of resectable. But correct me if I'm wrong @bigman1, that was not your premise. I think the premise of the OP was flawed ("I thought overall survival was less than 20% at 5 year mark for all stages head of pancreas"). While resectable pancreatic adenoCA is itself a not common entity, within that group long-term survivors are not that uncommon (if you believe the American Cancer Society e.g.). Not to be a wet dishrag, but the 95% C.I. on that 31% 3y OS would overlap with published chemo-only or chemoRT survivals (roughly only about 10 patients in the BED>70 arm were available for events/censoring by the 3y mark and were the basis for the 31% metric).
Similar threads

- Replies
- 79
- Views
- 7K

