Advertisement - Members don't see this ad
At least they were honest about it. 1 out of 3 said they wouldn't hypofractionate because of decreased revenue.
at least they were honest.
lot of practitoners in the states love to dance around the fact


Use all the free resources available to you from SDN: articles, guides, expert advising, forums discussions, and school research.
At least they were honest about it. 1 out of 3 said they wouldn't hypofractionate because of decreased revenue.
In terms of fractions, we are not doing better in parts of Europe. At all.
Hypo- vs Normofractionated RT in Early Breast Cancer – Patterns of Care in German speaking countries
The majority of the 180 physicians who completed the survey use the normofractionated regimen of RT as standard treatment for early breast cancer (76.6%).
At least they were honest about it. 1 out of 3 said they wouldn't hypofractionate because of decreased revenue.

You ain't kiddin'. Do a job search for "generous vacation package" and "radiation oncology." Goes together like cocaine and waffles. Here's a radiology job that pays 375K a year with 26 weeks annual vacation 😉Med students,
The radiologists at my hospital have double my vacation time, 2/3 of my work hours, and make $200K more than I. Most of the radiology new hires are also either FMG or Caribbean grads.
If you want to take care of cancer patients, become a med onc. You will make twice the salary and have location flexibility.
If you are after the lifestyle or money, go into radiology
If you want respect, become a surgical oncologist
The jobs market in rad onc is bad and going to crash soon. There's 1000 new grads waiting for a job in front of you. My hospital already told me that they are looking to hire FMGs who need visa sponsorship and is thus willing to accept very low salaries. I was told that FMGs can work in a rural area for several years to get a green card so they accept very low salaries. This is the future of rad onc. Be aware!

You ain't kiddin'. Do a job search for "generous vacation package" and "radiation oncology." Goes together like cocaine and waffles. Here's a radiology job that pays 375K a year with 26 weeks annual vacation 😉
When I take a close look at them, the data cited do not appear to support the arguments being made - I would encourage people to read the linked articles closely. I may be misunderstanding the point about lung SBRT, but we do 50 cases in a matter of weeks-to-months! Perhaps we have better relationships with our thoracic surgeons and pulmonologists? Yes, we are observing increasingly high demand and long wait times for brachytherapy. Keep in mind that a lot of pertinent data - e.g., up-to-date local demand - is, of course, important for local market competitiveness and not published.
"My point is that I am now having an even tougher time acceptingMy point is that I am now having an even tougher time accepting people's anecdotes and calculations when they are just so far out of line with reality.
When people started arguing against my claim above, I genuinely was not sure if people were joking or trolling. The subsequent posts led me to believe that people were posting serious responses. I don't even know what to say to that!
For what it's worth, I confirmed against my own case logs, and other residents even thought I was underestimating.
My point is that I am now having an even tougher time accepting people's anecdotes and calculations when they are just so far out of line with reality.
This is exactly what I'm saying. There's only so many ways you can divvy up the care of just ~50,000 Stage I NSCLC patients per year in the U.S., and the surgeons have historically--and still do--dealt with the majority of that ~50,000. Idk what the contribution of the "oligomet bucket" adds to early NSCLC SBRT work. This is unknown to me; I've looked for the data but can't find any reliable data to report. I'd be surprised to find out rad oncs are doing more oligomet SABRing than NSCLC SABRing, but it's possible. Let's say it'sAre we talking about 50 early stage lung or are we including oligomets?
Average of 4 per rad onc does seem low (and 50 seems high), but somethings that may attribute to the low average number of cases:
- Some rad oncs in the community do no have the equipment to do SBRT or are unfamiliar with the technique
- Not a good referral base from pulm or cardiothoracic surgeons.
- Academics that treat breast, prostate, GI, etc - I mean rad oncs wouldn't treat any early stage lungs with SBRT, right?
This is exactly what I'm saying. There's only so many ways you can divvy up the care of just ~50,000 Stage I NSCLC patients per year in the U.S., and the surgeons have historically--and still do--dealt with the majority of that ~50,000. Idk what the contribution of the "oligomet bucket" adds to early NSCLC SBRT work. This is unknown to me; I've looked for the data but can't find any reliable data to report. I'd be surprised to find out rad oncs are doing more oligomet SABRing than NSCLC SABRing, but it's possible. Let's say it's double the NSCLC SABR work though. That'd be a total of 9 SABR patients (NSCLC and oligomets) per rad onc, per year, in the U.S.!

When people started arguing against my claim above, I genuinely was not sure if people were joking or trolling. The subsequent posts led me to believe that people were posting serious responses. I don't even know what to say to that!
For what it's worth, I confirmed against my own case logs, and other residents even thought I was underestimating.
My point is that I am now having an even tougher time accepting people's anecdotes and calculations when they are just so far out of line with reality.

but everyone here does more than 3 lung SBRTs a year.
so what gives? where is the math wrong?
That is for stage I NSCLC only. I do SBRT far more for stage IV disease than I do for Stage I NSCLC. Like if I've done 100 SBRT cases over the years, I'd be surprised if more than 10 of them were stage I NSCLCs.
This is where relying on oligomets to save the field becomes a VERY dangerous game. If a Phase III trial shows no change in OS and worse toxicity, those current treatments may just *poof* into nothing. At least the ones with private insurance. And... you better be able to defend each Medicare case if audited.Same here, I was actually surprised that my SBRT early stage lung numbers were so low because we do about 3-4 a week and 90% are oligomets.
Quite dangerous. I wanted to say this a couple days ago lol but afraid I'd be wah-wah'd. I have been very reticent to dive into the Stage IV spot welding pool. I mean I see a fair number of patients but ain't no way I'm ready to pull the trigger on 750 SABRs a year (to each his own!). The data have been lackluster IMHO. SABR-COMET was a study which to me said don't be SABRing all the mets. And to get a bunch of Stage IV SABR met work, I guess you need med oncs who buy into it. I don't think those people (SABR met patients) are walking in off the street nor are they being plumbed from the depths of our followup visits. So when the referrers (our lord and master med oncs) become uninfatuated with met SABRing, which is a distinct possibility...This is where relying on oligomets to save the field becomes a VERY dangerous game. If a Phase III trial shows no change in OS and worse toxicity, those current treatments may just *poof* into nothing. At least the ones with private insurance. And... you better be able to defend each Medicare case if audited.
That is for stage I NSCLC only. I do SBRT far more for stage IV disease than I do for Stage I NSCLC. Like if I've done 100 SBRT cases over the years, I'd be surprised if more than 10 of them were stage I NSCLCs.
So my math work is still intact 😉Same here, I was actually surprised that my SBRT early stage lung numbers were so low because we do about 3-4 a week and 90% are oligomets.
Case logs bro.So my math work is still intact 😉
Full of arguably palliative, not robustly EBM-based care evidently.Case logs bro.
Nope. 50 stage I lung patients per month on my service.Full of arguably palliative, not robustly EBM-based care evidently.
750 was between my partner and I at least.Quite dangerous. I wanted to say this a couple days ago lol but afraid I'd be wah-wah'd. I have been very reticent to dive into the Stage IV spot welding pool. I mean I see a fair number of patients but ain't no way I'm ready to pull the trigger on 750 SABRs a year (to each his own!). The data have been lackluster IMHO. SABR-COMET was a study which to me said don't be SABRing all the mets. And to get a bunch of Stage IV SABR met work, I guess you need med oncs who buy into it. I don't think those people (SABR met patients) are walking in off the street nor are they being plumbed from the depths of our followup visits. So when the referrers (our lord and master med oncs) become uninfatuated with met SABRing, which is a distinct possibility...
So my math work is still intact 😉
I mean, I hope it does pan out. Not just for us, but for our patients.750 was between my partner and I at least.
I believe the oligomets data- all the studies seem to point in the direction of an OS benefit, and if I were a patient, I'd want it.
You're right in that getting medonc buy-in is the key.

Transparent yes. Not the same however from country to country. And many countries have "bundles". You irradiate a case of adjuvant breast -> you get a fix sum of money, irrelevant of how you do it (as long its according to guidelines).
Well damn....
Numbers just depressing. I wonder how hiring practices change when these disease site reimbursement drops dramatically
Let's all give a great big round of applause to #radonctwitter #radoncrocks for leading students off a cliff last 2 years...
Impact of Patient Stage and Disease Characteristics on the proposed Radiation Oncology Alternative Payment Model (RO-APM)
The proposed Radiation Oncology Alternative Payment Model (RO-APM) released on July 10, 2019, represents a dramatic shift from fee-for-service (FFS) r…www.sciencedirect.com

Not all of them have the bundles, yet.If it’s a fixed payment then why the resistantance to hypofrac?
Mayo worrying about the underserved; now that is rich.Well damn....
Numbers just depressing. I wonder how hiring practices change when these disease site reimbursement drops dramatically
Let's all give a great big round of applause to #radonctwitter #radoncrocks for leading students off a cliff last 2 years...
Impact of Patient Stage and Disease Characteristics on the proposed Radiation Oncology Alternative Payment Model (RO-APM)
The proposed Radiation Oncology Alternative Payment Model (RO-APM) released on July 10, 2019, represents a dramatic shift from fee-for-service (FFS) r…
They don’t want all the surrounding Rural practices to go belly up, because then they’d have to treat those folks.Mayo worrying about the underserved; now that is rich.
Mayo worrying about the underserved; now that is rich.
As much as I hate these academic corporate practices, you’re community hospital probably is gonna face a similar fate. I mean a 22 percent reduction in reimbursement for Head and Neck patients seriously? Probably some of the more challenging and sicker patients I take care of on a daily basis. What do they think is gonna happen in an APM? Think I’m gonna put up with the endless mucositis and dehydration and talking about PEG tubes? No I’m punting that nonsense.
Hospitals will start firing therapist to save $$ then fire attendings.
I heard that hospitals have really soured on the bundling of joints and I’m pretty sure the orthopods have as well.
But oh no I’m rad onc where we embrace whatever the govt proposes!
Worst specialty advocacy on the planet.
its a chicken and egg situation
not enough ppl donate to ASTRO but at same time ASTRO hasn’t shown themselves recently to deserve donations...
It definitely is.The APM is going to lead to big cuts, no matter what formula ends up being published- that's the point. As a result, we will need to make up for reductions in reimbursement per case with increased volume. I'll take ALL those head and neck cases that no one wants.
Our group has 7 radoncs in our city/region, and we met two weeks ago to discuss future plans/strategy/etc. We were unanimous in agreeing that:
a. When one of our older partners retires, we will not be hiring for his replacement and will instead cover his volume ourselves (pending any change in coverage requirements, of course)
b. Any new centers built will be covered by the existing radoncs
c. None of us (other than the single older partner) are going to retire in the next 10-15 years. (Increased residency complement over the last decade means many of us out there practicing are still relatively young.)
In our practice, then, we are anticipating a reduction in our local radonc workforce over the next decade, with zero new hiring to occur. I'm sure this conversation is happening at pp groups all across the country.
The APM is going to lead to big cuts, no matter what formula ends up being published- that's the point. As a result, we will need to make up for reductions in reimbursement per case with increased volume. I'll take ALL those head and neck cases that no one wants.
Our group has 7 radoncs in our city/region, and we met two weeks ago to discuss future plans/strategy/etc. We were unanimous in agreeing that:
a. When one of our older partners retires, we will not be hiring for his replacement and will instead cover his volume ourselves (pending any change in coverage requirements, of course)
b. Any new centers built will be covered by the existing radoncs
c. None of us (other than the single older partner) are going to retire in the next 10-15 years. (Increased residency complement over the last decade means many of us out there practicing are still relatively young.)
In our practice, then, we are anticipating a reduction in our local radonc workforce over the next decade, with zero new hiring to occur. I'm sure this conversation is happening at pp groups all across the country.
?? What does Vanderbilt have to do with this? I'm not aware of Vanderbilt playing a negative role in this.this is the fear and unfortunately clowns online like Vanderbilt radonc bs won’t tell the truth about
?? What does Vanderbilt have to do with this? I'm not aware of Vanderbilt playing a negative role in this.

The APM is going to lead to big cuts, no matter what formula ends up being published- that's the point. As a result, we will need to make up for reductions in reimbursement per case with increased volume. I'll take ALL those head and neck cases that no one wants.
Our group has 7 radoncs in our city/region, and we met two weeks ago to discuss future plans/strategy/etc. We were unanimous in agreeing that:
a. When one of our older partners retires, we will not be hiring for his replacement and will instead cover his volume ourselves (pending any change in coverage requirements, of course)
b. Any new centers built will be covered by the existing radoncs
c. None of us (other than the single older partner) are going to retire in the next 10-15 years. (Increased residency complement over the last decade means many of us out there practicing are still relatively young.)
In our practice, then, we are anticipating a reduction in our local radonc workforce over the next decade, with zero new hiring to occur. I'm sure this conversation is happening at pp groups all across the country.
when did that program start? cant be more than 10-15 years oldread Vandy radonc attending, dept, and residency twitter and you’ll see
biggest cheerleaders of nothing is wrong and SDN just big mad
read Vandy radonc attending, dept, and residency twitter and you’ll see
biggest cheerleaders of nothing is wrong and SDN just big mad
Can you provide some links supporting this? I can't navigate twitter anymore as I can see what people tweet out and the official account doesn't seem to say anything too outrageous, just cheerleading their own department....
xrt jobs are more likely to be posted online than other specialties because radoncs are more likely to be employed by large institutions/academics who have policies that all jobs must be posted. The fact that some of the few jobs online were pre-filled is an even bigger disaster! Divide the number of radonc current jobs by total graduating residents (200) and compare to radiology/IR/neuro/urology/ neurosurgery other specialties and see for yourself we are an order of magnitude off. scarb has done this. Again, those specialties are more likely to have word of mouth jobs than radiation since employers are less dominated by huge instituitions that are required to post jobs, so probably reality is even worse.Update from the front lines:
People I know are seeing more job offers coming in, academic and private (not fellowships).
Would reiterate what I and others have said, that most interviews and offers are coming through word of mouth and that positions are often posted online after they have already been filled, to satisfy HR requirements.
“Most offers coming through word of mouth”xrt jobs are more likely to be posted online than other specialties because radoncs are more likely to be employed by large institutions/academics who have policies that all jobs must be posted. The fact that some of the few jobs online were pre-filled is an even bigger disaster! Divide the number of radonc current jobs by total graduating residents (200) and compare to radiology/IR/neuro/urology/ neurosurgery other specialties and see for yourself we are an order of magnitude off. scarb has done this. Again, those specialties are more likely to have word of mouth jobs than radiation since employers are less dominated by huge instituitions that are required to post jobs, so probably reality is even worse.
That OP is appealing to his self created urban myth of hidden job bank for the well connected is very telling.
Its really hard for OP to get around the basic fact that graduating resident class is double what it was in 2007 just as hypofractionation becomes wide spread, APM on horizon, and declining prostates
This is comparing against peak prostate cancer diagnoses thanks to the advent of PSA testing. Our center and other centers have recently been seeing increasing demand for prostate cancer RT.
Other estimates from better-regarded sources, as I’ve discussed before, actually predict an increase in cancer incidence overall. Other estimates posted here have struck me as surprisingly inaccurate - e.g., current residents would agree with me that someone’s prior claim that MGH treats something like 8 lung SBRTs per year reflects a shockingly low number.
All of my fellow PGY-5s I have talked with - including those at my program and other programs - received offers for jobs that were not publicly advertised or posted. This is of course anecdotal, but nonetheless a large n. Again, we all have jobs, not fellowships, in highly desirable cities.
Just trying to introduce a dose of reality!
So how do you think this is possible. Prostate cancer is, as you know, the most common cancer in men. Number of new cases per year has dropped by ~33% over the last 10y, and we are about 25y out from the advent of PSA testing. The incidence held steady as you can see for many years after this advent (1990-95 time frame).This is comparing against peak prostate cancer diagnoses thanks to the advent of PSA testing. Our center and other centers have recently been seeing increasing demand for prostate cancer RT.

"Better-regarded sources" is weasel wording and a logical fallacy. Who's predicting this increased incidence in the U.S.? Smoking is on the downswing thus lung CA decreasing, prostate CA trends as noted above. You have previously cited one source which says the number of incident cases will increase in America by <1 million over the next 20 years and this will thus equal a ~1% rise in incidence per year. Surely you can realize that if this one single source's modeling is even mildly off... and follows the recent trend...Other estimates from better-regarded sources, as I’ve discussed before, actually predict an increase in cancer incidence overall.
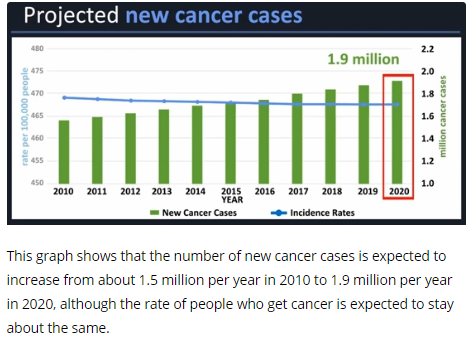
I will call you out for weasel wording again ("would agree with me"... that's nice!), and that "someone" is me. And it wasn't a claim. I was simply citing a source which revealed that at a lung nodule clinic at MGH they saw about 140 patients/year which yielded about 8 lung SBRTs a year. Draw conclusions from that as you will. But I have also cited national data showing that over a 10y period about 30,000 (out of ~150,000) patients at most got lung SBRT which translates to about 3,000 cases per year. We can be very confident that no more than ~15,000 patients per year are getting lung ca SBRT in the U.S. This number is where I get the ~3 lung SBRTs for every rad onc in America (on average) metric.current residents would agree with me that someone’s prior claim that MGH treats something like 8 lung SBRTs per year reflects a shockingly low number.
Back to your "better-regarded sources" and my "claims." Hopefully I have not made any "claims" per se. And my sources here were SEER, the CDC, The Oncologist, the JNCI, and the Red Journal. And a few random internet links for fun. However you have made claims which are, from my end, impossible to falsify. This does give you the virtue of never being provably wrong.Just trying to introduce a dose of reality!

Our mission is to provide students with free, unbiased information, resources, and advising for careers in the health professions. We believe every student deserves access to trustworthy guidance, regardless of background or ability to pay.


