
-
Practice your interview with the new SDN AI Interview Coach. Choose a school, answer by voice or typing, and receive a personalized feedback report. Available now to all SDN members. Try the AI Interview Coach.
You are using an out of date browser. It may not display this or other websites correctly.
You should upgrade or use an alternative browser.
You should upgrade or use an alternative browser.
Step I USMLE images
Started by Zuhal



ok, this is obviously lung tissue.
hx: 2 weeks ago had an MI. presents now with S3, dyspnea of exertion, and sleeps on top of 3 pillows at night

Going to throw this out there but it seems way too easy. Heart Failure cells?

iron-laden due to chf?
Going to throw this out there but it seems way too easy. Heart Failure cells?
not easy, you guys are just super geniuses. 😉
yup, hemosideren laden heart failure cells.
Advertisement - Members don't see this ad

ok, this is obviously lung tissue.
hx: 2 weeks ago had an MI. presents now with S3, dyspnea of exertion, and sleeps on top of 3 pillows at night
Heart failure cells?

so wait, connect the dots for me between the multifocal encephalopathy and aschoff bodies?
last one by me for the night...need to go read...but here you guys go...
two different individuals, just providing you two pictures of the same diagnosis
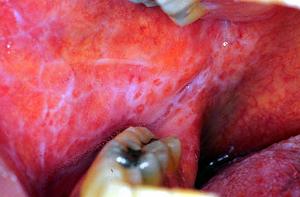
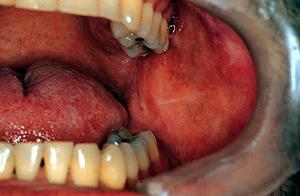
Lichen planus?
at this stage of the condition...mcc of death would be due to what?

Can anyone point out where the caterpillar nucleus anitschkow cell is? Also, I thought aschoff bodies were kind of in a myxoid stroma/edematous looking background. I hope on the NBME question they at least gave you enough background to tell you were in cardiac tissue 😛
Lichen planus?
Yep, wickham's striae iirc
last one by me for the night...need to go read...but here you guys go...
two different individuals, just providing you two pictures of the same diagnosis
Subacute bacterial endocarditis.


combo together?
B2 deficiency:
The 2 C's : Cheilosis of the mouth and corneal vascularization.
Last edited:
combo together?
Chlamydia

combo together?
Kawasaki disease
Advertisement - Members don't see this ad
blowing systolic murmur, best heard at the apex, and the following skin finding:

Dx?
rheumatic fever (erythema marginatum is shown)
Okay...here's my first contribution 😉
infant/young child with failure to thrive, short stature, unsteadiness, and this skin finding:

Last edited:
I'll leave a hint, since I'm about to go to bed. Highlight below if you want the hint.
If the dermatological complication from this disease were found in adults, it would classically be in a necklace distribution.
If the dermatological complication from this disease were found in adults, it would classically be in a necklace distribution.
rheumatic fever (erythema marginatum is shown)
Okay...here's my first contribution 😉
infant/young child with mental ******ation, short stature, and this skin finding:
Hartnup Disease.
That's the Dermatitis of Pellagra right there.
Hartnup Disease.
That's the Dermatitis of Pellagra right there.
nailed it 😛 I guess I need to think of a harder one
Middle-aged adult presents with systolic murmur radiating to carotids and anemia. What's the cause of the anemia?
Middle-aged adult presents with systolic murmur radiating to carotids and anemia. What's the cause of the anemia?
Mechanical destruction...I think. Does this patient have a mechanical aortic valve, or just really bad stenosis?
Mechanical destruction...I think. Does this patient have a mechanical aortic valve, or just really bad stenosis?
A correct answer, but not the one I was thinking of. I'm a bad question-writer 😳
The anemia I was thinking of is coincidental with the cardiac defect (you're right, it's aortic stenosis). There would also be findings upon colonoscopy:
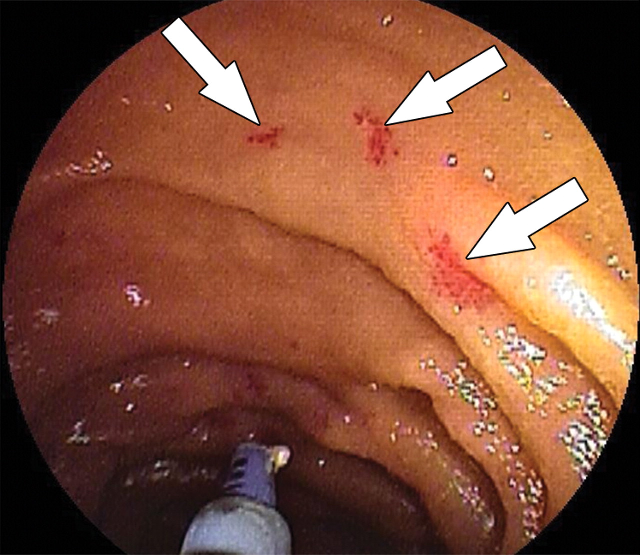
Hopefully that's enough of a hint without giving it away.
Last edited:
A correct answer, but not the one I was thinking of. I'm a bad question-writer 😳
The anemia I was thinking of is coincidental with the cardiac defect (you're right, it's aortic stenosis). There would also be findings upon colonoscopy:
Hopefully that's enough of a hint without giving it away.
lol colon cancer with strep bovis? 😛 edit: didnt see the pic lol
A correct answer, but not the one I was thinking of. I'm a bad question-writer 😳
The anemia I was thinking of is coincidental with the cardiac defect (you're right, it's aortic stenosis). There would also be findings upon colonoscopy:
Hopefully that's enough of a hint without giving it away.
Osler-Weber-Rendu
Osler-Weber-Rendu
good try but that's not it. This came up in my outpatient IM rotation today and was a PBL case at my school
good try but that's not it. This came up in my outpatient IM rotation today and was a PBL case at my school
OK I had to go hunting, but this disease has been cemented in my memory now. I'd never heard of it before.
It's Heyde Syndrome.
OK I had to go hunting, but this disease has been cemented in my memory now. I'd never heard of it before.
It's Heyde Syndrome.
yep 👍 aortic stenosis + vWF deficiency/angiodysplasia/iron-deficiency anemia (iirc it's in gunnertraining, but the name isn't listed, just the symptom associations)
side question: what's a good short-term pharmacotherapy for this, since the bleeding is due to low vWF (straight out of FA/pathoma)?
yep 👍 aortic stenosis + vWF deficiency/angiodysplasia/iron-deficiency anemia (iirc it's in gunnertraining, but the name isn't listed, just the symptom associations)
side question: what's a good short-term pharmacotherapy for this, since the bleeding is due to low vWF (straight out of FA/pathoma)?
Desmopressin.
Desmopressin.
right again! okay...bedtime. I'll try to think of some more contributions tomorrow. But I should probably gtfo of this thread by wednesday when I get my scores back and cant say I'm studying for step1 anymore

Advertisement - Members don't see this ad
yep 👍 aortic stenosis + vWF deficiency/angiodysplasia/iron-deficiency anemia (iirc it's in gunnertraining, but the name isn't listed, just the symptom associations)
side question: what's a good short-term pharmacotherapy for this, since the bleeding is due to low vWF (straight out of FA/pathoma)?
Desmopressin.
Since it's vWF what else could be used to treat this? Straight from UW (I'm pretty sure, at very least 1 of my 4 qbanks).
blowing systolic murmur, best heard at the apex, and the following skin finding:
Dx?
I had no idea what erythema marginatum actually looked like, thanks for this!!!
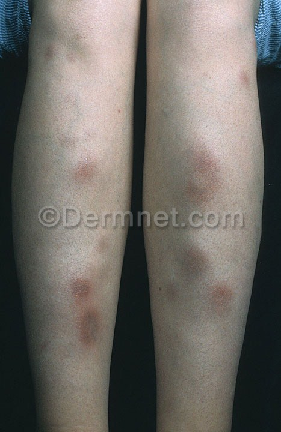
This finding plus this finding
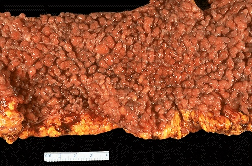 +
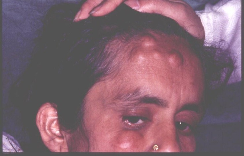
equals what syndrome?
equals what syndrome?
This finding plus this finding
+
equals what syndrome?
turcot syndrome?
This finding plus this finding
+
equals what syndrome?
Crohn's: cobblestone + erythema nodosum
turcot syndrome?
That's a good guess too, as is Gardner's
turcot syndrome?
so close 😛 there's another slightly different syndrome that is the right answer (same family of mutation though). Turcot's would have medulloblastoma or malignant glioma instead of the second picture
Crohn's: cobblestone + erythema nodosum
clever, but this is erythema nodosum (classically on legs)
That's a good guess too, as is Gardner's
that's it! those are osteomas of the face/skull bones
clever, but this is erythema nodosum (classically on legs)
It's amazing how much book knowledge I've obtained for studying for this test but when used in a practical setting I'm just as likely to diagnose Lyme disease for Endocarditis for SJS for Crohn's if someone doesn't tell me what I'm looking at in words. Good job USMLE
It's amazing how much book knowledge I've obtained for studying for this test but when used in a practical setting I'm just as likely to diagnose Lyme disease for Endocarditis for SJS for Crohn's if someone doesn't tell me what I'm looking at in words. Good job USMLE
lol...that's so true in my case too... but this thread has sure helped.
+100000. As someone who never went to lecture, one of the biggest gaps in my knowledge is images. The lectures at my school sucked and left out tons of important, Step 1-testable material...but at least they had lots of pictures. And when you're in third year, knowing what things look like is just as important as knowing lots of facts about it. I think this thread is really important!
27 y/o male just immigrated from Africa shows up with painless ulcerations on his penis that he first noticed 1 week ago. Patient was started on a course of Penicillin G but returned 10 days later when there has been no improvement of his condition.
One of the ulcers is swabbed and the slide below is what is seen in the lab.

What is the arrow pointing to?
What is the disease?
What is the cause of the disease?
Why didn't Penicillin G cure the disease?
(sorry for the Giant picture, especially those of you on phones, but it's a good one and the smaller version lacked)
One of the ulcers is swabbed and the slide below is what is seen in the lab.
What is the arrow pointing to?
What is the disease?
What is the cause of the disease?
Why didn't Penicillin G cure the disease?
(sorry for the Giant picture, especially those of you on phones, but it's a good one and the smaller version lacked)
This finding plus this finding
+
equals what syndrome?
That's a good guess too, as is Gardner's
It's Gardner's right?
FAP + osseous tumors + rentinal hyperplasia?
wow, I have absolutely no idea what that is... damn.27 y/o male just immigrated from Africa shows up with painless ulcerations on his penis that he first noticed 1 week ago. Patient was started on a course of Penicillin G but returned 10 days later when there has been no improvement of his condition.
One of the ulcers is swabbed and the slide below is what is seen in the lab.
What is the arrow pointing to?
What is the disease?
What is the cause of the disease?
Why didn't Penicillin G cure the disease?
(sorry for the Giant picture, especially those of you on phones, but it's a good one and the smaller version lacked)
It's Gardner's right?
FAP + osseous tumors + rentinal hyperplasia?
yes but the mutation is the same in Lynch, not FAP
yes but the mutation is the same in Lynch, not FAP
Are you sure? http://en.wikipedia.org/wiki/Gardner's_syndrome#Cause
Advertisement - Members don't see this ad
yes but the mutation is the same in Lynch, not FAP
FA has it under FAP, same as turcot's. I've gotten enough of these questions incorrect that this is burned in my head
zzz. you are definitely right tiedyeddog/MLT2MT2DO. i thought i was remembering gunnertraining, but i just checked it again and i was wrong
zzz. you are definitely right tiedyeddog. i thought i was remembering gunnertraining, but i just checked it again and i was wrong
no prob,
I think HPNCC/Lynch -> MSH2/MSH1/MSH6/PMS1+2. Doesn't always have polyps. Lots of other cancers.
FAP(and gardner's, turcot) -> APC. Always has hundreds of polyps.
27 y/o male just immigrated from Africa shows up with painless ulcerations on his penis that he first noticed 1 week ago. Patient was started on a course of Penicillin G but returned 10 days later when there has been no improvement of his condition.
One of the ulcers is swabbed and the slide below is what is seen in the lab.
What is the arrow pointing to?
What is the disease?
What is the cause of the disease?
Why didn't Penicillin G cure the disease?
This definitely sounds like Syphillis.. don't know what I'm looking at though; is what you are pointing at intracellular?

Similar threads


- Replies
- 0
- Views
- 73
- Replies
- 0
- Views
- 746
