
You are using an out of date browser. It may not display this or other websites correctly.
You should upgrade or use an alternative browser.
You should upgrade or use an alternative browser.
Costs and figures... startup Solo podiatry office
Started by Feli

Get help with your application
Use all the free resources available to you from SDN: articles, guides, expert advising, forums discussions, and school research.

100%. I used to pay for a service that would push reviews from my provider page over to google, but only if it was a good review.I’m starting to think docs are buying reviews on Google.

I've paid for marketing, the ROI is exceptionally poor.
Unfortunately, the only marketing that pays off is the kind of pound-the-ground putting your face out there that costs you sweat and not dollars. "I can see an ingrown toenail same-week" trumps any 5-star review.
Lately, out of boredom and vanity, I've been posting clinical photos to my instagram page. Patients like that kind of thing. It's tedious but not as time consuming as you would expect. I have few followers, however.
Advertisement - Members don't see this ad
I’m starting to think docs are buying reviews on Google.
I do find it odd that nearly every podiatry practice in our area is 4.7+ stars on Google reviews. Especially given the fact that I have had multiple patients that came from these other practices that hated that practice.
Even our own practice. There's an occasional one or two star because of issues with their bill or us refusing to do the procedure then and there without authorization, etc. But still, I find it weird that we are rated so high (4.9) with all the complaints and yelling I see going on in clinic from patients, lol.
It does make me think that we are incentivising these patients that do leave good reviews with something. I should ask the manager and see what it is.

BeaverBlade
Full Member
Sometimes the best doc’s/surgeons have the worst reviews. It is interesting. 300+ reviews sitting at 4.8 or higher is usually suspicious but patients go for those places

The review game is really funny to me. The simple truth is that if you make no effort to seek reviews - even amazing experienced doctors that patients rave about will basically have very few reviews. All 3 of the orthopedic foot and ankle guys in my town had 15-25 reviews. They are all here for decades. In general, patients mostly describe them as incredible / excellent / life savers etc. I looked up some of the best known general/shoulder/knee ortho guys. None of them have any substantial quantity of reviews. One of them is the best total knee doctor in the area. Described as having amazing results by everyone who sees them. Another is the best sports meds, shoulder etc guy. Can do 8-10 surgeries in a day where the staff say its smooth as butter and he's amazing and friendly and what not. Looked up the best general surgeon for a lap chole. She's got a 5 star review, but she's only got 13 reviews. The techs at both hospitals/surgery centers I go to say hands down she's the best general surgeon in town. Best hands, best decision making.Sometimes the best doc’s/surgeons have the worst reviews. It is interesting. 300+ reviews sitting at 4.8 or higher is usually suspicious but patients go for those places
So - the worst podiatrist in my town historically had about a 2 star review. Had again - maybe 20 reviews. All of a sudden he gets a new website and has almost 200 reviews. But here's the best part of it - even with almost 200 reviews he's still a low 4. And that's interesting to me because another ortho group in my town did the review buying game also. It resulted in almost all of the members of the group being 4.8-4.9. But one of the guys is a known dick and he's like a 4.3.
So here's my joke on the whole thing. Reviews are fake. No one has them unless they chase them. If you are really amazing, you'll have more. There's probably a locality game. If you're in Katy, Texas you probably have to chase reviews/buy them
I suspect if you have a bunch - you are buying them. And if you have a bunch, but you aren't near a 5 star - there's something flawed about you.
This is all conjecture and open to argument, but if we all got reviews for everything we do most of us would probably have near 5 stars because the simple truth is most encounters go fine. I've chased reviews a few times and you have to stick on it because it really seems like the underlying tendency is for patients to not review.
BeaverBlade
Full Member
I don’t have it setup but my emr can email/text patients for reviews after. If they review 5 stars it’ll post it. If they put like 1 star it’ll send them to a “tell me more” and it never gets posted just goes to an email.The review game is really funny to me. The simple truth is that if you make no effort to seek reviews - even amazing experienced doctors that patients rave about will basically have very few reviews. All 3 of the orthopedic foot and ankle guys in my town had 15-25 reviews. They are all here for decades. In general, patients mostly describe them as incredible / excellent / life savers etc. I looked up some of the best known general/shoulder/knee ortho guys. None of them have any substantial quantity of reviews. One of them is the best total knee doctor in the area. Described as having amazing results by everyone who sees them. Another is the best sports meds, shoulder etc guy. Can do 8-10 surgeries in a day where the staff say its smooth as butter and he's amazing and friendly and what not. Looked up the best general surgeon for a lap chole. She's got a 5 star review, but she's only got 13 reviews. The techs at both hospitals/surgery centers I go to say hands down she's the best general surgeon in town. Best hands, best decision making.
So - the worst podiatrist in my town historically had about a 2 star review. Had again - maybe 20 reviews. All of a sudden he gets a new website and has almost 200 reviews. But here's the best part of it - even with almost 200 reviews he's still a low 4. And that's interesting to me because another ortho group in my town did the review buying game also. It resulted in almost all of the members of the group being 4.8-4.9. But one of the guys is a known dick and he's like a 4.3.
So here's my joke on the whole thing. Reviews are fake. No one has them unless they chase them. If you are really amazing, you'll have more. There's probably a locality game. If you're in Katy, Texas you probably have to chase reviews/buy them
I suspect if you have a bunch - you are buying them. And if you have a bunch, but you aren't near a 5 star - there's something flawed about you.
This is all conjecture and open to argument, but if we all got reviews for everything we do most of us would probably have near 5 stars because the simple truth is most encounters go fine. I've chased reviews a few times and you have to stick on it because it really seems like the underlying tendency is for patients to not review.
BeaverBlade
Full Member
This whole insurance thing is mind boggling. Trying to learn which ones need referrals, etc. this stuff is not fun! Definitely what I know least about.
My residency told me that there are no HMOs in their area other than perhaps Tricare or VA.This whole insurance thing is mind boggling. Trying to learn which ones need referrals, etc. this stuff is not fun! Definitely what I know least about.
In my area
BCBS HMO for Teachers, ie. TRS
BCBS for State Employees, police, universities, prison guards etc.
BCBS HMO - plain old normal people with HMO
BCBS Healthcare.gov ie. Blue Advantage HMO
Tricare and VA
I think that's mostly it. There are actually HMOs in my area that don't require a referral - its simply a tactic to ensure you are in network.

So legit buying of reviews is actually illegal and the FTC can heavily fine businesses for it. On top of that, Google's algorithm can find them and permanently suspend your business' profile for it. There are also black market websites who you can pay for reviews for, but then they will hold a ransom over you and threaten to leave serial negative reviews on your profile if you don't pay them enough. Sure a practice can ask their patients to leave them, very legal, but truly buying reviews is one of the stupidest things a business can do.
I didnt know that. A competetor has hundreds of reviews. All 5 stars. Its obvious something inorganic is happening.So legit buying of reviews is actually illegal and the FTC can heavily fine businesses for it. On top of that, Google's algorithm can find them and permanently suspend your business' profile for it. There are also black market websites who you can pay for reviews for, but then they will hold a ransom over you and threaten to leave serial negative reviews on your profile if you don't pay them enough. Sure a practice can ask their patients to leave them, very legal, but truly buying reviews is one of the stupidest things a business can do.

Yes, this is the obvious extension.... widely accepted that about 80% of patients Google their doctors even before accepting a PCP referral, so PCP referral with a poor online presence doesn't mean much....
1) The critical part... hard part... difficult part is the getting PCP refers. That needs 80-90% of your efforts, time, money.
2) The other part is online: Google biz page, getting 5 star ratings, and website. 10-20% of your marketing time/efforts.
People trust the PCP refer, but they will usually do a quick verify by looking at your Google biz profile, your info, star rating. Some go to the website and read your training/bio, some don't. But yeah, you need a good (free) Google biz page with filled-in hours, info, some good pics (can do DIY tripod or bf/gf/etc ones to start, then go professional photog ones later). You need to set up a basic system to get reviews (QR code cards).
The website can also be basic DIY at first (~$200/yr for host + design software on GoDaddy or similar), but it's probably worth it to upgrade to better once clearly profitable ...I think I pay about $2500/yr ($225/mo) for good website (design+hosting+updates) and also FB page with updates.
The SEO part does itself if you have a fully completed Google biz, fairly good website with reasonably dynamic content, then some longevity. Yeah, the ones who pay will be a "top result," but that eats into profits, generally pathetic. Let them have it. SEO, paid ads for social media, etc etc doesn't tend to do one bit of anything if the patient is already referred to you from the PCP, peds, specialist, etc. 😎
Yeah, you can pay companies to do this (FB, IG, etc updates roughly weekly)....Lately, out of boredom and vanity, I've been posting clinical photos to my instagram page. Patients like that kind of thing. It's tedious but not as time consuming as you would expect. I have few followers, however.
If you enjoy it, you can DIY it. Delegating to office staff is a risk for obvious reasons.
...I would maintain that the online ads (paid) are nonsense - for any website. It attracts the wrong crowd.
The free Google biz profile is obvious. The website is cheap and needs to be passable.
The SEO part takes care of itself if you have a fully filled out Google biz and a decent website.
I hate Facebook, but you have to make one to have a biz one. Again, free and not a terrible idea.
__________
So legit buying of reviews is actually illegal and the FTC can heavily fine businesses for it. On top of that, Google's algorithm can find them and permanently suspend your business' profile for it. There are also black market websites who you can pay for reviews for, but then they will hold a ransom over you and threaten to leave serial negative reviews on your profile if you don't pay them enough. Sure a practice can ask their patients to leave them, very legal, but truly buying reviews is one of the stupidest things a business can do.
...A competetor has hundreds of reviews. All 5 stars. Its obvious something inorganic is happening.
...regarding fake Google reviews: yeah many offices, many MANY medical offices and hospitals do them. Many other biz types also. It's especially easy for hospitals where the "reviews" are on their own website (below the doc profile). Most are complete BS; at minimum, they don't show low ratings. A doc who started a month ago will have 100+ five star reviews and a couple 4 star.I’m starting to think docs are buying reviews on Google.
Personally, I can't figure it out why so many ppl buy fake reviews. Google is getting VERY good at removing fake reviews. If they don't delete them right away, they usually will soon. I know "a friend" who tried this years ago (at an employed job, because s/he is dumb), and none of the reviews stuck for any amount of time. There are various services that'll do fake reviews, fake negatives for competitors, removal of your bad reviews. All are money wasted, risks suspension of the biz profile, risks fraud or ID theft (depending how you pay). Basically, Google figures out accounts used for fake reviews, and they'll be deleted (with all reviews given). Google is an incredible company... I own at least 500+ shares (plus tons more via indexes). If you see these fake reviews (generic info, account with low reviews or random reviews in MANY states/areas), flag them to Google "low quality information." They'll get taken down in a month or so typically.
...To gain Google reviews, the best thing to do is just make QR code cards, pass them to patients who've had a positive experience (usually when you PRN them). Have your employees ASK the people directly, "we'd really appreciate a positive review on Google." Everyone has a gmail these days. Many won't leave one, but a good amount will (make it easy with the QR code cards). It is important to like and reply to review to have them more likely to stick (I have had legit reviews wiped by Google sometimes... lame, but it happens). It is not allowed to incentivize reviews; those companies offering gift cards, drawings, etc for positive reviews are breaking Google policy.
There can also be a flowthrough on your website to ask for ratings. You'll obviously get the occasional bad review from sour grapes folks, but you just need enough positives to cover them up overall... anyone scrolling knows nobody and no biz gets all positives, but those few 1 and 2 stars just look like grumpers when there are 10x or 20x as many good reviews. As for other review types (Yelp, HealthGrades, etc), nobody cares about those... you can fill out a profile if you wish - mainly just to claim it, but would not waste much of your time on those.
*A cautionary tale: the supergroup I left made a Bing profile for me (my name, etc)... but they claimed it, managed it, put THEIR number, THEIR website, etc. I had not made mine, so they claimed it. A small percent of ppl have Bing default on their (MicroSoft) phone or laptop or whatever, so some old ppl use Bing search. Microsoft devices always try to default browser to Bing or change it, and many ppl suck at tech. Bing is less than 5% internet searches and just does a bad job of copying Google Maps... but the profiles can be claimed/edited (to different ph, web, etc vs Google profile). Watch out for that. So, I was getting patients who thought they appointed with me, but they were instead on with my old office, directed to new associate who replaced me. Not cool. They did it to a couple other DPMs in the state also (made a Bing places page in those doc names, but routed to their phones). I put in a complaint to state medical board. So do that Bing profile claim and basic info... just so it isn't used against you.
Last edited:
This is crazy bro, that’s like an attorney’s retainer to do nothing. I paid $50 for a domain for 5 years and then $450 for web hosting for 3 years. Once a website is built, it should cost very little.The website can also be basic DIY at first (~$200/yr for host + design software on GoDaddy or similar), but it's probably worth it to upgrade to better once clearly profitable ...I think I pay about $2500/yr ($225/mo) for good website (design+hosting+updates) and also FB page with updates
Sure, but those websites will also get you spammed, hacked, etc much easier. They take your time to log in and update and format... and don't generally look as good as professionally designed ones. I had that type for a year or so; it can do the job. It is not great coming to emails (mostly through your website comments) from various manual and AI spammers every day, though.This is crazy bro, that’s like an attorney’s retainer to do nothing. I paid $50 for a domain for 5 years and then $450 for web hosting for 3 years. Once a website is built, it should cost very little.
It's usually a lot easier to have professional services for those things, any office things - unless you truly enjoy them and/or are good at them. I can make a basic website, and I did... but I don't want to mess with uploading pics, changing content anymore. I mainly realized that I have no idea how to properly secure a website with capcha, etc. The professional one also has substantially more movement, interaction, plays better on mobile phone version. My DIY one was maybe average or a bit below among medical office websites, but the professional one is definitely above average. I am not spending the top dollar that some plastics, derm, pod, IM, etc offices do for the airbrushed and super slick looking websites... but mine is pretty good. So, I am fine spending that cost of roughly one new pt per month for that marketing facet to be well done. I can spend my time on other stuff. My gf probably could do the web/tech part better than me, but her time is twice as valuable as mine (she will do the biz machines networking, clean up comps, wifi troubleshoot, etc from time to time... sometimes... if I am really stuck).
It's a personal choice due to pref and where you're at in the biz. "Price is what you pay; value is what you get." I find the professional website/FB mgmt much simpler now (and yeah, it'd be more like $100-150/mo if I just got the website only... if I did't want the FB updates). $200/mo or so isn't much once you get going; it's a tiny piece of annual budget. I will have a pretty good website update later this year, and I just send it to them... they put it up quick and well. 🙂
Last edited:
BeaverBlade
Full Member
I made my website with Claude it took one day and a $20 subscription. Looks pretty legit too. I’m with @Boba Foot he convinced me to make my own. I know how to update it too it’s really easy.Sure, but those websites will also get you spammed, hacked, etc much easier. They take your time to log in and update and format... and don't generally look as good as professionally designed ones. I had that type for a year or so; it can do the job. It is not great coming to emails (mostly through your website comments) from various manual and AI spammers every day, though.
It's usually a lot easier to have professional services for those things, any office things - unless you truly enjoy them and/or are good at them. I can make a basic website, and I did... but I don't want to mess with uploading pics, changing content anymore. I mainly realized that I have no idea how to properly secure a website with capcha, etc. The professional one also has substantially more movement, interaction, plays better on mobile phone version. My DIY one was maybe average or a bit below among medical office websites, but the professional one is definitely above average. I am not spending the top dollar that some plastics, derm, pod, IM, etc offices do for the airbrushed and super slick looking websites... but mine is pretty good. So, I am fine spending that cost of roughly one new pt per month for that marketing facet to be well done. I can spend my time on other stuff. My gf probably could do the web/tech part better than me, but her time is twice as valuable as mine (she will do the biz machines networking, clean up comps, wifi troubleshoot, etc from time to time... sometimes... if I am really stuck).
It's a personal choice due to pref and where you're at in the biz. "Price is what you pay; value is what you get." I find the professional website/FB mgmt much simpler now (and yeah, it'd be more like $100-150/mo if I just got the website only... if I did't want the FB updates). $200/mo or so isn't much once you get going; it's a tiny piece of annual budget. I will have a pretty good website update later this year, and I just send it to them... they put it up quick and well. 🙂
If you take one or two days to figure it out you can put that money you’re throwing away monthly into the S&P and retire earlier 🙂
Advertisement - Members don't see this ad

I hope everyone else can appreciate the irony that, when viewing the website on mobile and upright like most people will, the group advertising as foot surgeons has the model’s picture cut off at her knees.
BeaverBlade
Full Member
It’s not even that sleek of a website. Claude can make with less than 3 hours of effortI hope everyone else can appreciate the irony that, when viewing the website on mobile and upright like most people will, the group advertising as foot surgeons has the model’s picture cut off at her knees.
Yes, this is the right mindet.... you can put that money you’re throwing away monthly into the S&P and retire earlier 🙂
You also want to get the student loans gone (yeah, buying stock/index is sexier, but you have to do both... unlikely all these 20+% return years last forever).
But these office expenses are smart expenses no matter how you do them...
- good staff ... attract/retain with pay, bonuses, gifts, training, etc
- marketing, website, gifts to refer offices
- quality instruments
- fast internet and good phone + fax + answer service
- decent biz machines: computers, printers, scanners
- efficient EMR
- occasional small OTC gifts to pts (pads, creams, even occasional insoles, etc) to build rapport
...The place to save money (aka avoid "throwing away") would be...
- the big "doctor house" you don't need (tons of interest... even if equity holds or improves over time)
- the lifted truck, boat, atv, trailers to pull them, etc (especially "bought" on a loan, not paid cash)
- the vacation you pay full price on when you could've waited for a sale (or been happy with much less costly more local recreation time)
- the fancy meals and top dollar groceries
- the trophy/sahm/sahd wife/hubs who is financially incompetent
- the many various subscriptions that add up
- expensive sports/concerts/events
- collectibles (endless types, obviously)
- the endless home improvements that add little/nothing
Sure, it's great to save a bit on office supplies, medical supplies, office utilities, get the cheaper malpractice, stuff like that... but those are not the things that delay the retirement to any great extent. Those are all putting your $$ to work, growing it. 🤑
Last edited:
offices do for the airbrushed and super slick looking websites...
😂😂😂 wtf is this?
In seriousness though, I get that it’s not in everyone’s wheelhouse or priority to do their own website, find cheap hosting, etc. I just wanted to point out that you don’t have to do it that way and it can save some coin over time. Was actually inspired by a post on White Coat Investor to do it. At the bare minimum, at least own your own domain and don’t let a marketing company own it. Domain authority gained over time is valuable and you don’t want to have to pay more for it when it’s more valuable due to its authority.

hahahah Dang. That's wild.
On another note, Looks like you can't just be a podiatrist or physical therapist to work there. You must also simultaneously be a model.
2 of them are ABFAS Foot certified. There's something very funny about claiming to be something you aren't.
View attachment 424220
2 of them are ABFAS Foot certified. There's something very funny about claiming to be something you aren't.
Including being well trained.
BeaverBlade
Full Member
Obviously this will be different for everyone but what is a good goal on patient volume per week for the first few months when opening a practice? Let’s assume you are starting cold essentially with no name recognition in the area
You would probably get 10/wk (2/day) for a couple weeks (basically just walk-ins, a few refers from ER or UCare),Obviously this will be different for everyone but what is a good goal on patient volume per week for the first few months when opening a practice? Let’s assume you are starting cold essentially with no name recognition in the area
then ~15/wk for a couple weeks (PCP refers begin to trickle in if you market f2f + bring snacks),
then 20 weekly (4-5/d) for awhile.
I'd expect it to take a year or more to make it up to 20pts/day if you have no foothold or name value or PCP relationships in the area at all at the start. It may take longer if competition is strong, your location is not good, you are timid with marketing, etc.
It depends on the area. Obviously if other podiatry group(s) in the area are not on much of a wait list, it'll take longer. If there is no podiatrist there (refer patterns wide open), it takes less time. Cold start takes awhile, but just gives you plenty of time to work on getting onto insurance plans, optimize your system, streamline your supply prices, market with f2f and go to doc meetings/lounge. You obviously only need one employee for awhile (90% phones). It really does not take much volume at all to pay your utilities and some EMRs have low use rate, though... the employees are the expensive part.
...the best thing to do in that new office situation (owner starting, owner expand / hire associate, or even associate if you have a productivity bonus) is SHORT follow-ups. That is how you fill the schedule faster. The people are in pain... nothing wrong with seeing PF or ankle sprains back 2wks, any XR/test ordered back in 2wks, chronic joint/tendon pain 3wks, skin conditions 3wks, RFC ~65d, etc etc.
Later, when you get established and on wait list (without expand plan), you do basically the opposite: PRN as many as you can, 6wks for most pain/injects, 4-6wks for fractures, 3-4mo for RFC care, etc... gotta make room for new pts and the ones you can't PRN (active wounds, surg healing, injuries, etc). That is what I do now (decided awhile ago no expand/associate/partner)... but half the PRNs seem to come back for something else or send a friend/fam anyways. 😛 Good "problem" to have though.
Last edited:
It depends on the area.
Recently discovered that a colleague that graduated around the same time I did, Started a practice, and now has to shut down (open less than 2 years) because they were unable to get credentialed with enough payers in that market. Wasn't anything fancy, wasn't a build out, just a normal 2 room practice that they put their heart and soul into.....gone!
Conceptually, I always knew that these panels could be closed, but I thought there were ways around it, (IPA's, etc). But to hear firsthand that you can do everything right and still have to shut down is terrifying. The worst part is, it's a practice in a metro with a podiatry school.
So what message does it send to all the prospective students and current students that someone can do everything right and be entrepreneurial and start their own practice, and still have to shut down because of oversaturation?
BeaverBlade
Full Member
or they'll pay 75% of medicare in these saturated areas. and podiatrists are not in demand enough to do direct care/monthly subscriptions like PCP's...... it is very hard out here for podiatristsRecently discovered that a colleague that graduated around the same time I did, Started a practice, and now has to shut down (open less than 2 years) because they were unable to get credentialed with enough payers in that market. Wasn't anything fancy, wasn't a build out, just a normal 2 room practice that they put their heart and soul into.....gone!
Conceptually, I always knew that these panels could be closed, but I thought there were ways around it, (IPA's, etc). But to hear firsthand that you can do everything right and still have to shut down is terrifying. The worst part is, it's a practice in a metro with a podiatry school.
So what message does it send to all the prospective students and current students that someone can do everything right and be entrepreneurial and start their own practice, and still have to shut down because of oversaturation?
AFAIK, I don't think this person was even offered a low rate like that. I think they were just told it's completely closed to all new podiatrists in the area. They tried to make it work for a couple years, but saturation in that market is INSANE!or they'll pay 75% of medicare in these saturated areas. and podiatrists are not in demand enough to do direct care/monthly subscriptions like PCP's...... it is very hard out here for podiatrists
Well, that's a pure failure to do their research before entering the market. That's a myth more often than not.Recently discovered that a colleague that graduated around the same time I did, Started a practice, and now has to shut down (open less than 2 years) because they were unable to get credentialed with enough payers in that market. Wasn't anything fancy, wasn't a build out, just a normal 2 room practice that they put their heart and soul into.....gone!
Conceptually, I always knew that these panels could be closed, but I thought there were ways around it, (IPA's, etc). But to hear firsthand that you can do everything right and still have to shut down is terrifying. The worst part is, it's a practice in a metro with a podiatry school.
So what message does it send to all the prospective students and current students that someone can do everything right and be entrepreneurial and start their own practice, and still have to shut down because of oversaturation?
Frankly, a DPM can do just fine on Medicare only (which all can get onto). MCR will be your top payer in the vast majority of areas (definitely for podiatry, also for many MD/DO specialties). Obvious bonus if you can get onto PPOs in the area (or if PPOs actually outnumber MCR pts... rare but very awesome). But regardless, you could do fine on MCR and only MCR (and cash for any other takers), no joke. MCR will be over half your insurance pays in most areas (other parts of the pie are various MCA and PPOs, MCR adv plans, work comp, etc). My area has MCR as my #2 payer, but I would still do ok if for some reason I could not be on #1 payer (just take more appts for MCR and others).
Truthfully, you can't really fail unless you are so bad you can't get onto hospitals, get kicked off MCR, etc. You could drop me in the middle of NYC or Chi or whatever, and I'd be able to be viable. Would my net per pt be the same? Heck no... most plans probabably pay lower due to 500 or even 1000+ DPMs in those metros, and my rent/staff would be higher and marketing would be MUCH higher. But I'd make it.
...It does happen that PPs "fail," but there is typically much more to the story. Don't let those myths/rumors discourage you.
A few guys here have done PP (after doing hospital/MSG and being sick of crappy admins or wanting better hours/income), and they fold the PP and go back to hospital jobs simply due to not liking how much nails/RFC is in PP. Their offices were financially viable - or well on their way, but the pt/refer mix was not what they wanted. Others might have no idea what they're getting into with the admin aspect. I will admit I don't love admin stuff sometimes, but it was necessary to get better income... it's not hard most of the time (surround yourself with good ppl). Other common themes in "shut down" PPs are nowhere near enough money to start with (and/or too big/expensive too fast), strong competition moves in, ortho moves in, doc is just not likeable (to the point of few refers, bad reviews, even malpractice), etc. It's one's choice at those points to pivot, market more, get creative on revenue streams (or savings), take more stuff in terms of path, or carve out niche (wound care, big surg, whatever)... versus "fold" the practice.
Again, trifecta for successful PP (do well with two, amazing with all three):
- good area payers
- little area competition
- likeable charismatic competent doc
IPA should get them in on a panel regardless, except UHC who doesn't do IPAs. Any idea why they couldn't get in?Recently discovered that a colleague that graduated around the same time I did, Started a practice, and now has to shut down (open less than 2 years) because they were unable to get credentialed with enough payers in that market. Wasn't anything fancy, wasn't a build out, just a normal 2 room practice that they put their heart and soul into.....gone!
Conceptually, I always knew that these panels could be closed, but I thought there were ways around it, (IPA's, etc). But to hear firsthand that you can do everything right and still have to shut down is terrifying. The worst part is, it's a practice in a metro with a podiatry school.
So what message does it send to all the prospective students and current students that someone can do everything right and be entrepreneurial and start their own practice, and still have to shut down because of oversaturation?
All problems in the end are cash flow related. The rest are just details.
Advertisement - Members don't see this ad
Just opened my doors today fellas. Wish me luck!!
Just opened my doors today fellas. Wish me luck!!

You will do well... most ppl do.Just opened my doors today fellas. Wish me luck!!
PP is kinda like picking up dates, making friends, sales... some ppl are naturally good at it. Others, not so much. It's a people game.
But there is plenty of demand if you will see whatever to build up a PCPs refer base. Communicate well and meet people. You can get choosy later. Leave it to the hospital pods to be discriminating from the start... and then get talked to by their admins that they are not full/productive enough.
BeaverBlade
Full Member
Same… are you…. Me?Just opened my doors today fellas. Wish me luck!!
Same… are you…. Me?
You BOTH opened for the first time ever on the SAME exact day?!!!
What are the odds!!
Your post's goldYou would probably get 10/wk (2/day) for a couple weeks (basically just walk-ins, a few refers from ER or UCare),
then ~15/wk for a couple weeks (PCP refers begin to trickle in if you market f2f + bring snacks),
then 20 weekly (4-5/d) for awhile.
I'd expect it to take a year or more to make it up to 20pts/day if you have no foothold or name value or PCP relationships in the area at all at the start. It may take longer if competition is strong, your location is not good, you are timid with marketing, etc.
It depends on the area. Obviously if other podiatry group(s) in the area are not on much of a wait list, it'll take longer. If there is no podiatrist there (refer patterns wide open), it takes less time. Cold start takes awhile, but just gives you plenty of time to work on getting onto insurance plans, optimize your system, streamline your supply prices, market with f2f and go to doc meetings/lounge. You obviously only need one employee for awhile (90% phones). It really does not take much volume at all to pay your utilities and some EMRs have low use rate, though... the employees are the expensive part.
...the best thing to do in that new office situation (owner starting, owner expand / hire associate, or even associate if you have a productivity bonus) is SHORT follow-ups. That is how you fill the schedule faster. The people are in pain... nothing wrong with seeing PF or ankle sprains back 2wks, any XR/test ordered back in 2wks, chronic joint/tendon pain 3wks, skin conditions 3wks, RFC ~65d, etc etc.
Later, when you get established and on wait list (without expand plan), you do basically the opposite: PRN as many as you can, 6wks for most pain/injects, 4-6wks for fractures, 3-4mo for RFC care, etc... gotta make room for new pts and the ones you can't PRN (active wounds, surg healing, injuries, etc). That is what I do now (decided awhile ago no expand/associate/partner)... but half the PRNs seem to come back for something else or send a friend/fam anyways. 😛 Good "problem" to have though.
I'm some variation of 3 months "on site" though not technically 3 months of seeing patients. Have 13 people a day scheduled on quite a few days, but still have days with painful amounts of no shows / reschedules. I'm in network with most of what I'm going to be able to be in with. Tricare is having some sort of problem generating a contract. One of my hospitals offered me 130%-Medicare for their employee plan - I countered with the rates I got at my last office and I'm still waiting to hear if they will agree. Trying to see if I can get some good rates from prisoners, but not sure how that will play.
Collections last month were $28K against expenses of $16K. I'm still learning Xero, but I think my collections have grown from $14K->$21K->$28K. $5K of the expenses was rent on the building I own. My staff want me to hire a receptionist because they are having difficulty with all the hats they are wearing. Have 2 people currently at $21 an hour. No health insurance. I would like to give them a 401k but not till I can benefit from it and I haven't paid myself yet. Haven't had to infuse cash since July when I put $10K in for malpractice.
The MA does all cleaning, all instrument prep, rooms people, turns the rooms over, assists with surgery, takes x-rays, dispenses DME, works the referral fax folder, works the phone, and does surgery paperwork. No non-staff cleaning crew. Cleans the toilets on Friday etc. Vacuums, mops, etc.
My receptionist works the front desk, works the phone, works referrals, does all of our billing-clearinghouse, fights bills with me on Friday during admin hour, does posting, statement generating, etc. She checks Availity for deductibles. I'm not paying any sort of billing company at present. I enter the charges myself on all encounters and the receptionist then posts the claims and follows them through.
At my last office we had a useless office manager who pointed out to me that there was no process in place in which we checked to see if billing from Athena actually resulted in postings to our bank account. This was very easy to remedy. I control the bank account. When ERA shows up saying we received money - my receptionist doesn't "post" it to the EHR until I confirm that the deposit was actually received.
We rapidly learned not to use ECW's credit card reader. We bill in Helcim and then she brings the payments into ECW to credit copays/co-insurance etc.
I've written scripts and we're going to go harder on taking money from people before procedures.
I probably do need another person because the receptionist answering phones / working the front desk is also often posting paper EOBs and checks all simultaneously. Her billing work is too precious to complicate when I could just hire a receptionist.
I'm still spending my lunches resolving ERA/EFT issues.
I've got a lot supplements submitted to ECHO. Found a new ERA website - Data Stream where some of my Vpay insurance supplements are going to be ERA-ed.
My concern is that our collections last month represented a lot of work that posted from prior months, but that is the nature of the game.
What's working.
1. Mostly haven't been punished yet for dropping health insurance. Using Crowd Health. Hospital has been very affordable as a self-pay.
2. Was able to replace meds/pharmacy relatively affordable.
3. Owning building verse paying partner continues to pay off.
4. Learning SOO much about the transactional/merchant fees that were eating my lunch at last office. We were routinely paying "card not present" fees to the tune of like 3.5% + change and then Athena was taking another 8%. I did not know this, but if you give up $4 of a $100 transaction to merchant fees then Athena will still charge you 8% of the $100 because $100 was what posted on the 835. You thought you made $100, but really you kept $88. I've eliminated the transaction fee on all sorts of EFT transactions and I'm not paying anyone any sort of RCM.
5. Surgical volume is actually increasing.
6. Top problems last office - a loser deadweight partner with a personality disorder who made my staff miserable/fired people, Athena 8% charges, expenses constantly increasing, IT constantly increasing, partner fraudulently increasing rent. Seem to have jettisoned all of them.
What's not working.
1. Hurt knee/shoulder at beginning of year and just can't seem to get 100%. Probably wouldn't have pursued treatment anyway, but not a perfect situation.
2. Still haven't gotten a paycheck, but work bank account increased $10K last month.
2. Having ...small midlife crisis - ie. do I really have to do this forever. I worked my ass off trying to save the last office, but I also had days where I knew the office couldn't be saved and would just say screw it - see my patients and leave at 3. I'm there at 7:10 every day and I stay till 5pm every day asking myself "what can we do right".
4. But honestly the biggest problem is its just tooo damn Hot. I'm ready for fall.
5. Staff pecking at each other a bit. People making mistakes that others have to clean up. My 2 staff were united at the last office in that they hated my partner and they hated our worthless office manager. Now there's just us.
Dead on for everything I've also experienced.I'm some variation of 3 months "on site" though not technically 3 months of seeing patients. Have 13 people a day scheduled on quite a few days, but still have days with painful amounts of no shows / reschedules. I'm in network with most of what I'm going to be able to be in with. Tricare is having some sort of problem generating a contract. One of my hospitals offered me 130%-Medicare for their employee plan - I countered with the rates I got at my last office and I'm still waiting to hear if they will agree. Trying to see if I can get some good rates from prisoners, but not sure how that will play.
Collections last month were $28K against expenses of $16K. I'm still learning Xero, but I think my collections have grown from $14K->$21K->$28K. $5K of the expenses was rent on the building I own. My staff want me to hire a receptionist because they are having difficulty with all the hats they are wearing. Have 2 people currently at $21 an hour. No health insurance. I would like to give them a 401k but not till I can benefit from it and I haven't paid myself yet. Haven't had to infuse cash since July when I put $10K in for malpractice.
The MA does all cleaning, all instrument prep, rooms people, turns the rooms over, assists with surgery, takes x-rays, dispenses DME, works the referral fax folder, works the phone, and does surgery paperwork. No non-staff cleaning crew. Cleans the toilets on Friday etc. Vacuums, mops, etc.
My receptionist works the front desk, works the phone, works referrals, does all of our billing-clearinghouse, fights bills with me on Friday during admin hour, does posting, statement generating, etc. She checks Availity for deductibles. I'm not paying any sort of billing company at present. I enter the charges myself on all encounters and the receptionist then posts the claims and follows them through.
At my last office we had a useless office manager who pointed out to me that there was no process in place in which we checked to see if billing from Athena actually resulted in postings to our bank account. This was very easy to remedy. I control the bank account. When ERA shows up saying we received money - my receptionist doesn't "post" it to the EHR until I confirm that the deposit was actually received.
We rapidly learned not to use ECW's credit card reader. We bill in Helcim and then she brings the payments into ECW to credit copays/co-insurance etc.
I've written scripts and we're going to go harder on taking money from people before procedures.
I probably do need another person because the receptionist answering phones / working the front desk is also often posting paper EOBs and checks all simultaneously. Her billing work is too precious to complicate when I could just hire a receptionist.
I'm still spending my lunches resolving ERA/EFT issues.
I've got a lot supplements submitted to ECHO. Found a new ERA website - Data Stream where some of my Vpay insurance supplements are going to be ERA-ed.
My concern is that our collections last month represented a lot of work that posted from prior months, but that is the nature of the game.
What's working.
1. Mostly haven't been punished yet for dropping health insurance. Using Crowd Health. Hospital has been very affordable as a self-pay.
2. Was able to replace meds/pharmacy relatively affordable.
3. Owning building verse paying partner continues to pay off.
4. Learning SOO much about the transactional/merchant fees that were eating my lunch at last office. We were routinely paying "card not present" fees to the tune of like 3.5% + change and then Athena was taking another 8%. I did not know this, but if you give up $4 of a $100 transaction to merchant fees then Athena will still charge you 8% of the $100 because $100 was what posted on the 835. You thought you made $100, but really you kept $88. I've eliminated the transaction fee on all sorts of EFT transactions and I'm not paying anyone any sort of RCM.
5. Surgical volume is actually increasing.
6. Top problems last office - a loser deadweight partner with a personality disorder who made my staff miserable/fired people, Athena 8% charges, expenses constantly increasing, IT constantly increasing, partner fraudulently increasing rent. Seem to have jettisoned all of them.
What's not working.
1. Hurt knee/shoulder at beginning of year and just can't seem to get 100%. Probably wouldn't have pursued treatment anyway, but not a perfect situation.
2. Still haven't gotten a paycheck, but work bank account increased $10K last month.
2. Having ...small midlife crisis - ie. do I really have to do this forever. I worked my ass off trying to save the last office, but I also had days where I knew the office couldn't be saved and would just say screw it - see my patients and leave at 3. I'm there at 7:10 every day and I stay till 5pm every day asking myself "what can we do right".
4. But honestly the biggest problem is its just tooo damn Hot. I'm ready for fall.
5. Staff pecking at each other a bit. People making mistakes that others have to clean up. My 2 staff were united at the last office in that they hated my partner and they hated our worthless office manager. Now there's just us.
The staff pecking gets a little crazier when you expand. Good workers are worth their weight in gold.
The female MAs tend to gossip more and drive a wedge between themselves, a little more emotional but are better at telephone/front desk/ multitasking stuff.
The male MAs are great at back end/ prep procedures/supplies/dispense but some patients don't like how terse they are.
Last edited:
BeaverBlade
Full Member
If there are any female sdn podiatry posters you’re about to get it boy.The females tend to gossip more and drive a wedge between themselves, a little more emotional but are better at telephone/front desk/ multitasking stuff.
The males are great at back end/ prep procedures/supplies/dispense but some patients don't like how terse they are.
But it is hilarious how much better my staff is at answering phones than me. I didn’t even get the patients date of birth when trying to schedule someone
Yah no feel free to let them rip into me.If there are any female sdn podiatry posters you’re about to get it boy.
But it is hilarious how much better my staff is at answering phones than me. I didn’t even get the patients date of birth when trying to schedule someone
I am terrible at stuff some of my female colleagues can pull off with their eyes closed. Its not even close.
Not saying all females or males are like that. Just anecdotal observations.
Took my 5 years after graduating fellowship to finally take the leap. Hbu?Same… are you…. Me?
BeaverBlade
Full Member
graduated residency in 23. still a young pup sort of.Took my 5 years after graduating fellowship to finally take the leap. Hbu?
Just got offered this fee schedule:
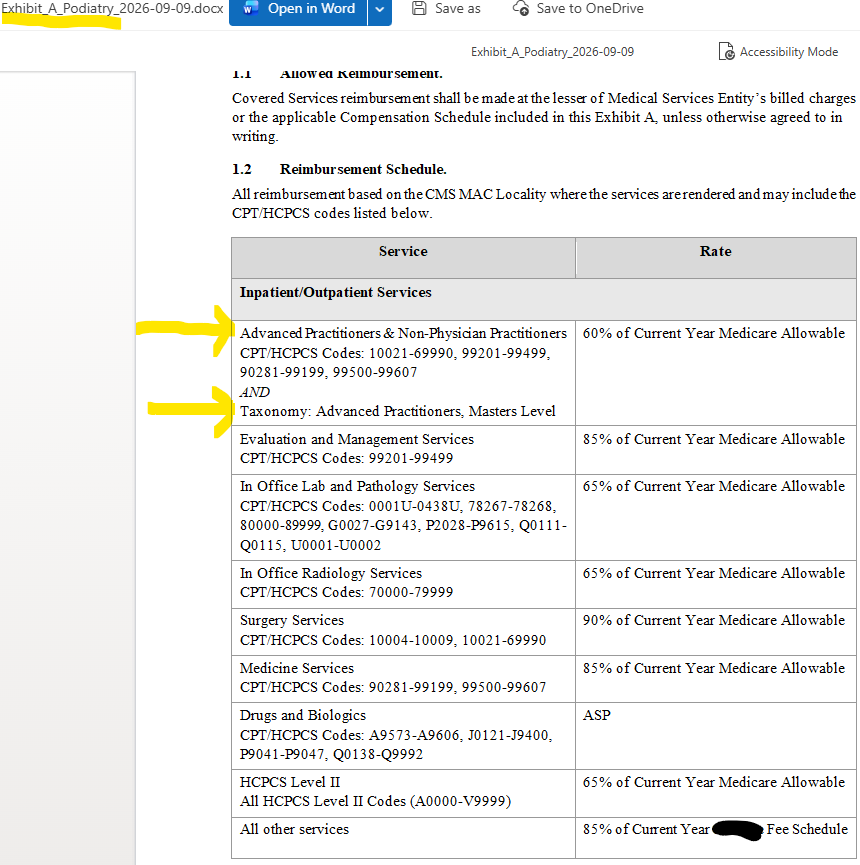
We are truly valued.
But I want to touch on something for people who haven't done this before. Medicare is the anchor around all fee schedule negotiations. You don't negotiate individual codes. Everyone I'm interacting with is sending a sheet like this with a percentage next to Medicare. Yes - you can negotiate it, but you're negotiating from a position of a deep deficit in most cases.
BeaverBlade
Full Member
So where did this lie happen where commercial insurances pay better than Medicare? For podiatry it clearly doesn’t. I wish all my patients were Medicare.Just got offered this fee schedule:
View attachment 424371
We are truly valued.
But I want to touch on something for people who haven't done this before. Medicare is the anchor around all fee schedule negotiations. You don't negotiate individual codes. Everyone I'm interacting with is sending a sheet like this with a percentage next to Medicare. Yes - you can negotiate it, but you're negotiating from a position of a deep deficit in most cases.
Should we want Medicare for all? I mean why not? They pay the best
This was actually the case 20 years ago. Those days are long gone. Nowadays, Medicare is KING!So where did this lie happen where commercial insurances pay better than Medicare? For podiatry it clearly doesn’t. I wish all my patients were Medicare.
Should we want Medicare for all? I mean why not? They pay the best
Advertisement - Members don't see this ad
BeaverBlade
Full Member
Procedure codes are still better with most commercial but e&m Medicare is king for sureThis was actually the case 20 years ago. Those days are long gone. Nowadays, Medicare is KING!

Procedure codes are still better with most commercial but e&m Medicare is king for sure
Very location dependent. I had a BCBS contract at 180% Medicare, UHC was my worst commercial payer at 130% Medicare. And MA plans were 100% Medicare. Prison insurance payed 2x Medicare for inmates…cha-ching…for the most part this was true for both E/M and CPT codes.
Oh word? I need to go holler at the closest county jail!!!!Very location dependent. I had a BCBS contract at 180% Medicare, UHC was my worst commercial payer at 130% Medicare. And MA plans were 100% Medicare. Prison insurance payed 2x Medicare for inmates…cha-ching…for the most part this was true for both E/M and CPT codes.
I got my clinic open saturdays, and on tuesdays i'm open till 7pm. Add rounding at nursing homes and Prisoners and I'll be golden. Gotta be a hustler if you gonnna try to survive this profession
Go get em.Oh word? I need to go holler at the closest county jail!!!!
I got my clinic open saturdays, and on tuesdays i'm open till 7pm. Add rounding at nursing homes and Prisoners and I'll be golden. Gotta be a hustler if you gonnna try to survive this profession
I've got a surplus of podiatrists around me.
When I first came to town I reached out to 4 or 5 nursing homes/ assisted living/ LTC facilities. All 5 told me to kick rocks.
Had a CEO via their secretary tell me "We already have a podiatrist." and nothing else, just radio silence.
Really rooting for you and the other 2 who just opened up shop.
Had a CEO via their secretary tell me "We already have a podiatrist." and nothing else, just radio silence.
Ouch. Have we reached nursing home toenail clipping saturation?


