
You are using an out of date browser. It may not display this or other websites correctly.
You should upgrade or use an alternative browser.
You should upgrade or use an alternative browser.
Job Market
Started by DogSnoot

Get help with your application
Use all the free resources available to you from SDN: articles, guides, expert advising, forums discussions, and school research.

If all you have is a nipper, everything looks like a nail 
I'd love to do nothing but easy in office procedures, MSK stuff, ingrowns, PF, easy wound care, warts etc and not do any elective surgery.Agree with nails/calluses being the easiest thing to fill up my schedule. Don't get me wrong - I get paid decently to do it and it's good to provide a medical service that patients want, but it's definitely soul-sucking and existential crisis-inducing after a time.
Podiatry as it stands now seems to have painted itself in a corner. Nails are pretty much the guaranteed thing to see in practice and basically dictates our job market - more mobile podiatry/heavier outpatient clinic jobs, fewer surgery jobs. Reconstruction surgery is just not as in-demand - good connections and/or the willingness to go to BFE in order to practice full training is a must. But IMO, even being able to offer surgical options feels like a trap - all of us could be trained to the top of the podiatry license and we still would be dictated by what other surgical specialties (especially ortho, even more especially F&A ortho) want to do, making pursuing that feel like a waste of time too. All of this makes me feel that the best way to get out of this corner is to formally come into the ACGME fold as a properly trained semi-specialized PCP that can help fill an actual demand vs being a niche pseudo-surgeon that nobody wants or asked for.
Odd amp or salvage or tendon stuff to offload an ulcer? Sure.
In the current space of increasing DPMs in the market, doesn't seem viable to limit what you can do.
If someone is already doing this, let me know.
Being fresh out and wasting time doing outpatient procedures while I could be cranking clinic is frustrating.
Advertisement - Members don't see this ad
I do this + some elective sx. Its boring. You know whats not boring? 400k/yr.I'd love to do nothing but easy in office procedures, MSK stuff, ingrowns, PF, easy wound care, warts etc and not do any elective surgery.
Odd amp or salvage or tendon stuff to offload an ulcer? Sure.
In the current space of increasing DPMs in the market, doesn't seem viable to limit what you can do.
If someone is already doing this, let me know.
Being fresh out and wasting time doing outpatient procedures while I could be cranking clinic is frustrating.
Fair enough.I do this + some elective sx. Its boring. You know whats not boring? 400k/yr.
I could be completely naïve and short sighted cause I can't see 10 years down the line.
I do this + some elective sx. Its boring. You know whats not boring? 400k/yr.
Nice. Is this PP as owner, associate of PP or supergroup (lol), rural hospital with clinic owned by hospital where they just throw money at you cause there is no one else around? lol
Isn't this like >50% of pods out there lol. A lot, probably not even by choice. lolI'd love to do nothing but easy in office procedures, MSK stuff, ingrowns, PF, easy wound care, warts etc and not do any elective surgery.
Odd amp or salvage or tendon stuff to offload an ulcer? Sure
Last edited:

Now do that but add in some limb salvage....it's boring. You know what's not boring? 500k+/yrI do this + some elective sx. Its boring. You know whats not boring? 400k/yr.

Sendin_Toes_2market
Full Member
I get paid by wRVU now. I have a very unhealthy population 70% of my routine foot care patients come in with another issue. So I’m making 1.2-1.5 RVU for them. Non diabetics are done by my nurses so 0.5 RVU to just sign the note and say hi. Life is so hard. Only at 20 a day with 50/50 msk with ingrowns.
I have 6 bunions, 3 bronstroms, 2 Lapidus, a couple of met head resections, one peroneal tendon repair following TG. I also have NP in our hospital urgent care feeding me trauma.
I work 4 days a week. Hoping to do 30 patients a day and if my wRVU stays steady around 1.3-1.6, with my cases 150 a year will be making around 450k. My contract is not that great but with my support system I am home every night by 5pm and can make my rec leagues… in my opinion, the support system is essential.
I am in practice 40 years winding down. I knew years ago podiatry going down. The apma and schools need own up!!!A picture is worth a thousand words

This is my set up with outpatient surgery. No trauma because I have zero interest in trauma or any urgent cases.I'd love to do nothing but easy in office procedures, MSK stuff, ingrowns, PF, easy wound care, warts etc and not do any elective surgery.
Odd amp or salvage or tendon stuff to offload an ulcer? Sure.
In the current space of increasing DPMs in the market, doesn't seem viable to limit what you can do.
If someone is already doing this, let me know.
Being fresh out and wasting time doing outpatient procedures while I could be cranking clinic is frustrating.
Completely agree and I make similar incomeI do this + some elective sx. Its boring. You know whats not boring? 400k/yr.
I stopped doing any limb salvage or seeing inpatient consult. Being solo in PP, hospital consult is very time consuming and doing an add-on case after 7pm is not on my bingo card this year or next. I have only been in the hospital once this year for a consult/surgery. I want to make it zero in-patient consult next year. I only do outpatient elective surgery.Now do that but add in some limb salvage....it's boring. You know what's not boring? 500k+/yr
Fun question: If you were given a choice between making $400k/y doing productive clinic/no trauma out-patient surgery (and obviously being home at 5pm everyday) vs making $500k/y doing same clinic plus hospital consults, taking call, limb salvage, trauma and the whole nine yards. Which will y'all pick?
For me, my answer is obvious.
Oh I understand completely what you're saying. I have a very unique and fortunate setup. I walk to work I live 8 minutes Walk to the floor and the operating room. Doing inpatient consults is minimal work for me. My office is across the parking lot from the hospital. I have zero outreach zero other facilities to go to. If you're in private practice and not on RVU and you got to drive to do inpatient stuff and some of that work is uncompensated then yeah 100% don't do any of itThis is my set up with outpatient surgery. No trauma because I have zero interest in trauma or any urgent cases.
Completely agree and I make similar income
I stopped doing any limb salvage or seeing inpatient consult. Being solo in PP, hospital consult is very time consuming and doing an add-on case after 7pm is not on my bingo card this year or next. I have only been in the hospital once this year for a consult/surgery. I want to make it zero in-patient consult next year. I only do outpatient elective surgery.
Fun question: If you were given a choice between making $400k/y doing productive clinic/no trauma out-patient surgery (and obviously being home at 5pm everyday) vs making $500k/y doing same clinic plus hospital consults, taking call, limb salvage, trauma and the whole nine yards. Which will y'all pick?
For me, my answer is obvious.
I used to practice at a hospital location and consults were so easy. Walk over at lunch, add a case on for lunch the next day. I would eat lunch at the hospital every day anyways. Logistically it makes so much sense to see consults when you are connected to the hospital. Free referrals, The ER loved me, sent me trauma, which I often just added onto my friday block time, added revenue for simple MSK and wound followups. If trying to grow a practice this is an awesome setup like you've got. Once clinic get busy with what you like then pick and choose what you see. Harder to make the logistics and time work in your favor if the hospital is like 5 miles away.Oh I understand completely what you're saying. I have a very unique and fortunate setup. I walk to work I live 8 minutes Walk to the floor and the operating room. Doing inpatient consults is minimal work for me. My office is across the parking lot from the hospital. I have zero outreach zero other facilities to go to. If you're in private practice and not on RVU and you got to drive to do inpatient stuff and some of that work is uncompensated then yeah 100% don't do any of it

400 with clinic and no wild ****. That extra 100k ain't worth my mental ****eryThis is my set up with outpatient surgery. No trauma because I have zero interest in trauma or any urgent cases.
Completely agree and I make similar income
I stopped doing any limb salvage or seeing inpatient consult. Being solo in PP, hospital consult is very time consuming and doing an add-on case after 7pm is not on my bingo card this year or next. I have only been in the hospital once this year for a consult/surgery. I want to make it zero in-patient consult next year. I only do outpatient elective surgery.
Fun question: If you were given a choice between making $400k/y doing productive clinic/no trauma out-patient surgery (and obviously being home at 5pm everyday) vs making $500k/y doing same clinic plus hospital consults, taking call, limb salvage, trauma and the whole nine yards. Which will y'all pick?
For me, my answer is obvious.
I am 100% with you on this.I get paid by wRVU now. I have a very unhealthy population 70% of my routine foot care patients come in with another issue. S
Nails on wRVU are profitable when you treat trainwrecks. Healthy patients nails are not profitable. Cant make a living billing 11721 alone. Simply not worth time.
I only accept for DM with neuropathy. Everything else is declined. I practice in an economically depressed area. Near 100% of the time there are other seperate identifiable problems that qualify for E&M. 99213 + 11721 which comes out to 1.8wRVU.
Easy for 10 min care. Wash repeat. 9 wRVU an hour with little risk and no stress is easy work.
....Pays way better than a lapidus and no global

This is my set up with outpatient surgery. No trauma because I have zero interest in trauma or any urgent cases.
Completely agree and I make similar income
I stopped doing any limb salvage or seeing inpatient consult. Being solo in PP, hospital consult is very time consuming and doing an add-on case after 7pm is not on my bingo card this year or next. I have only been in the hospital once this year for a consult/surgery. I want to make it zero in-patient consult next year. I only do outpatient elective surgery.
Fun question: If you were given a choice between making $400k/y doing productive clinic/no trauma out-patient surgery (and obviously being home at 5pm everyday) vs making $500k/y doing same clinic plus hospital consults, taking call, limb salvage, trauma and the whole nine yards. Which will y'all pick?
For me, my answer is obvious.
I would love something like this. Seeing and talking to others in the trenches right now is so depressing. Hell, I'll gladly take that scenario for $250, but most around me are offering 100K with weird bonus nonsense.
Advertisement - Members don't see this ad

He is solo pp owner... not employed.I would love something like this. Seeing and talking to others in the trenches right now is so depressing. Hell, I'll gladly take that scenario for $250, but most around me are offering 100K with weird bonus nonsense.
@air bud said it in another thread, but vast majority of SDN ppl are 10yrs or so out, fair or good training, and doing pretty well.
Many here are private hosp pods making 400+, some are VA pods around 225 or 250k, others PP owner highly varied but 250+ once a year or two in.
All of that is NOT the norm.
Overall, nationwide, it's definitely over half od podiatrists are employees (that will only grow with supergroups expanding, forming, buying out traditional PPs). You don't generally see those $150k associates posting much... although many do read. A lot of the VA pods like to brag if they go from $125k no benefits associate to almost twice that with benefits... can't blame them.
I took all the DPMs licensed and practicing in NMex, and over half are employed in pod groups. Less than a third are hospital employ (most of those govt VA/IHS), and about 1/10 are solo owners. It's a small state, but you get the idea. A whole lot of DPMs are struggling - particularly with the increasing debt burdens.
I have gotten countless PMs on here over the years. (asked for none... no corny "AMA" threads)
I usually just have ppl call me to save time.
Most are just about clerkships or whatever.
Some are family asking to try to help their pod student or affirm their training/residency/whatever choice.
Some are about ideas on starting an office.
A whole LOT are about finding or changing pod jobs. I can sadly tell you that there are waaay more DPMs asking about some $120-180k job options between supergroup vs small practice vs 1099 stuff (often in Cali, Chicago, Boston, etc expensive places) than asking how to negotiate a $350k hospital pod offer higher. The people who create a rural or small hospital job cold calling and then aren't busy or admins suck or ortho sideswipes the cases they want are also a whole lot more common than you think.
...I used to routinely recommend podiatry... the debt was not great, but if you got solid training, it was reasonable... esp if you were flexible on location for job or starting a practice.
Now, it has changed quite a bit. The lending to start/buy office really dried up after the GFC 2007-09. The student loans have more than doubled. interest rates are doubled in %, and that adds up fast. Four more pod schools have opened up. The fellowship fad adds a year of interest. If anything, there are LESS good residency spots as some have watered down and/or added a fellowship that pulls out cases. The ROI is very rugged. I don't tell anyone not to go if they liked shadowing and are interested, but it has to be heavily thought through if one doesn't have family money for school and/or starting an office afterwards, expects to have good job options in a certain area, doesn't have scholarships to offset the now insane tuition, etc.
That is good you like that stuff. I was same when I was building up clinic.I used to practice at a hospital location and consults were so easy. Walk over at lunch, add a case on for lunch the next day. I would eat lunch at the hospital every day anyways. Logistically it makes so much sense to see consults when you are connected to the hospital. Free referrals, The ER loved me, sent me trauma, which I often just added onto my friday block time, added revenue for simple MSK and wound followups. If trying to grow a practice this is an awesome setup like you've got. Once clinic get busy with what you like then pick and choose what you see. Harder to make the logistics and time work in your favor if the hospital is like 5 miles away.
I do everything I can to dodge it now, though, and I'm ground floor a 1min walk from ER, lol.
Even regardless of proximity, it makes no sense due to much poorer insurance mix than scheduled outpt office and OR work. It's simply a way to mess up my lunch, evening, or maybe weekends... sometimes for volunteer work (that still adds liability).
Have a feeling anyone will grow out of it if they are on any kind of collections setup (typically new associates sent to do that work), but if you are on wRVU, it pays the bills... and is probably required. That stuff is basically what most hospital pods are hired for (consult/ER stuff, wound care, etc that ortho or other services don't want). I didn't love it in that setup either, but it's more palatable when a non-negotiable part of the job and compensated accordingly.
It's the old "when you don't have a choice, you don't have discontent either." 🙂
Last edited:
My office is 2 mins or less drive from the hospital. I go to the hospital every single day to grab lunch and coffee from the lounge to eat in my office. I still have no interest in hospital consults/surgery. My hospital is a level II (soon to be level I) trauma hospital so It's very big with multiple floors and unit. A new expansion will be completed soon at my hospital to add over 250 beds. My point is, going to see a consult is not a quick in and out especially when you have multiple consults in different floors and wings.That is good you like that stuff. I was same when I was building up clinic.
I do everything I can to dodge it now, though, and I'm ground floor a 1min walk from ER, lol.
Even regardless of proximity, it makes no sense due to much poorer insurance mix than scheduled outpt office and OR work. It's simply a way to mess up my lunch, evening, or maybe weekends... sometimes for volunteer work (that still adds liability).
Have a feeling anyone will grow out of it if they are on any kind of collections setup (typically new associates sent to do that work), but if you are on wRVU, it pays the bills... and is probably required. That stuff is basically what most hospital pods are hired for (consult/ER stuff, wound care, etc that ortho or other services don't want). I didn't love it in that setup either, but it's more palatable when a non-negotiable part of the job and compensated accordingly.
It's the old "when you don't have a choice, you don't have discontent either." 🙂
Come to think of it. When you have clinic like everyone does, you either do your non-elective hospital cases in the morning, lunch time or after clinic; I go to the gym every morning before clinic so I don't want to sacrifice my health for anymore hospital work. I enjoy my over one hour lunch break relaxing watching youtube videos or on video calls catching up with family/friends so I also do not want to sacrifice that time for any hospital work. After clinic in the evening, I want to go home, relax and spend time with my wife and kids so I also do not want to sacrifice my evenings/night for any hospital consult/surgery. Therefore, I have zero regret in dropping hospital consult/surgery. I feel much better and wayyyyy less stressed/overworked. Almost zero risk of burnout.
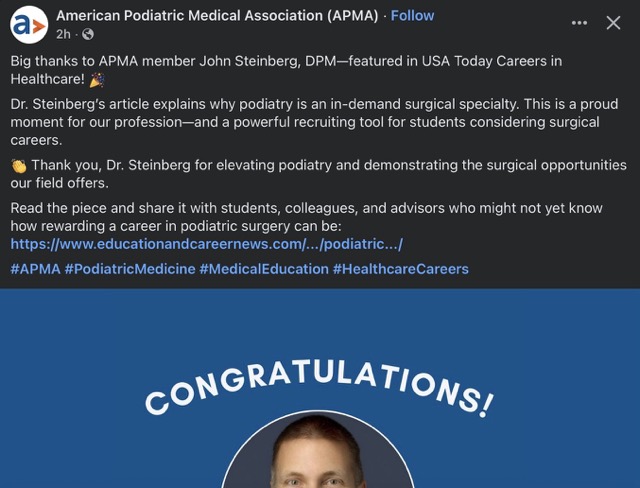
Lol more than half this thread is about the tangible effects of over-saturation (which are obvious if you just look around you or, at compensation compared to even PA's or CRNA's), and they're putting this out?
"In-demand surgeons" don't get offered 120K. Police officers make MORE than that without overtime.
I feel like we live in the twilight zone. Where did these organizations get their information from to come up with these claims on being "in-demand" hahahaha

"In-demand surgeons" don't get offered 120K. Police officers make MORE than that without overtime.
I feel like we live in the twilight zone. Where did these organizations get their information from to come up with these claims on being "in-demand" hahahaha
To be fair, Steinberg did not write the article... they just took a few snippets from him (mostly out of context). He's a pretty legit guy... mostly pus bus stuff but happy with that and does it well. Overall, this one - like all of these "advertorials" - was written by APMA marketing AACPM (says so at the bottom: Author: The American Association of Colleges of Podiatric Medicine).Lol more than half this thread is about the tangible effects of over-saturation (which are obvious if you just look around you or, at compensation compared to even PA's or CRNA's), and they're putting this out?
"In-demand surgeons" don't get offered 120K. Police officers make MORE than that without overtime.
I feel like we live in the twilight zone. Where did these organizations get their information from to come up with these claims on being "in-demand" hahahaha
View attachment 412653View attachment 412654
Gotta love that start, though: "A professional basketball player who tore their achilles tendon during a game, a diabetic patient at risk of losing their foot, and an older woman with a painful bunion who wants to get back to her daily walks. These are all patients served by Doctors of Podiatric Medicine (D.P.M.) ..."
I'd sure like to know that pro basketball player had their Achilles repair by a DPM.. sure wasn't Haliburton or Tatum or Durant or Kobe, haha. The articles are so poorly written, they can't even capitalize Achilles right (or be truthful). These should really say "ADVERTISEMENT" across the top of the 'news story,' but it's marketing strategy (just like buying lists of people who take MCAT). I'm sure podi deans and ampa fluffers and others have already re-tweeted it 10x or more. It's job security.
...In reality, podiatry is fairly in demand. In most areas, it is.
There is enough work... but it's mostly the undesirable work cutting nails, Medicare and ECF calluses, ulcers and wound care, weekend and evening add-on cases for rotting foot uninsured I&Ds and toe amps that gen surg and vascular and ortho and even nurses would rather not do. The MSK stuff, the well insured patients, all that is pretty competitive in any area. There are way too many DPMs for that work. The way the career and school is marketed in these infomercial articles versus what it actually is and the income teased against the actual reality of what most supergroup associate DPMs and similar make causes frustrations in many ways. The "want to be passed the blade" Apma ad was pathetic... can't find it, but look it up, I think @Retrograde_Nail posted it last year?
It's the old "don't mistake a sales pitch for education," and they're counting on people doing just that: learn about podiatry... from the people who profit from the education system for it. Med schools think it's hilarious that podiatry has to have huge budgets for marketing, and I sadly agree.

Last edited:
There are probably a fair amount of us who couldn’t get into medical school or dental school but wanted to be a “doctor” so settled on podiatry.
Yeah, I'd say 80% or more. The vast majority are pre-meds who couldn't get in (and a few who did try it, and it didn't work... Caribb, etc).There are probably a fair amount of us who couldn’t get into medical school or dental school but wanted to be a “doctor” so settled on podiatry.
That's their target market with these ads: pre meds who didn't do well on Mcat or otherwise aren't competitive enough for DO school.
(there are a few pod students, maybe that other 20% or so, who had a parent in podiatry or are foreign MDs or are career changers from a lab, nurse, allied health, non-health, etc job)
The other thing about surgery- not everyone who wants or asks for surgery NEEDS surgery.
Fresh out you will be tempted to cut on anything and everything. Pressure to meet numbers, prove yourself, keep your skills sharp.
Even those who are NOT fresh out and have been in the area for 5+ years are cutting on people who do not need to be cut on.
Just because you can doesn't mean you should.
Get good training. Do right by your patients. Know when NOT to cut.
ParNoMoney
Full Member
Remember, APMA advocates for the APMA, not for podiatrists.
What? What's a pulse procedure?Podiatry in trouble with E and M pulse procedure crackdown. I had knowledge of this three years ago., APMA blew me off …

autocorrect of "plus procedure"
I love me my 25 modifiers. You gotta keep your notes compartmentalized though, separate ICD-10 codes, separate paragraphs, separate sections, and I have a macro that says "this is a new problem in an established patient requiring a significant and separately identifiable evaluation and management service beyond the procedure described below." Tedious AF but that's the game. Never been audited on this but I feel like that's adequate preparation. IDGAF what the PCP thinks when I forward the notes to them, like the commercial says, it's my money and I want it now!
I love me my 25 modifiers. You gotta keep your notes compartmentalized though, separate ICD-10 codes, separate paragraphs, separate sections, and I have a macro that says "this is a new problem in an established patient requiring a significant and separately identifiable evaluation and management service beyond the procedure described below." Tedious AF but that's the game. Never been audited on this but I feel like that's adequate preparation. IDGAF what the PCP thinks when I forward the notes to them, like the commercial says, it's my money and I want it now!

I, like many graduating residents are heading to ACFAS 2026 in hopes for recruitment / job opportunities. The job market is bleak and none of the attendings at my program are helpful with job assistance (they're all hospital employed and have worked there 10+ years. They all live in their own bubble not understanding the struggles of many of their DPM colleagues). The offers we are getting are typically by Upperline Health and big private equity group in the region with some PP offering sub 150k. I looked into the military as I've seen multiple healthcare recruitment advertisements with sign on bonuses / loan repayment program that sounds like a sweet deal but as soon as I get in contact with them they tell me "Podiatry is not part of the medical or dental corps so the offer does not apply or Podiatry services are not needed". It is frustrating to see MD, DO, DDS, DMD, OD, PharmD, PT, OT, PA, NP, CRNA jobs in demand in the military with lucrative sign on bonuses yet Podiatry is not even considered? To add to insult, Podiatry is considered as allied health care in the military sharing ranks and pay with non-doctorate or no residency required fields.
Because I'm originally from an urban/suburban city and my program also is located in that demographic area, it is my desire to be employed at the similar setting. Knowing how saturated my hometown or any other city that seems desirable, I am so discouraged that I may end up either at some rural place or working low salary at PP struggling to pay off over$250K debt I have... I am in my mid 30s and have no $$$ or energy to switch careers, become any actual physician, or even do Caribbean online MD. What's honestly out there for 7 year trained DPMs to do at his point if our skillset can be done by every other speciality?
Because I'm originally from an urban/suburban city and my program also is located in that demographic area, it is my desire to be employed at the similar setting. Knowing how saturated my hometown or any other city that seems desirable, I am so discouraged that I may end up either at some rural place or working low salary at PP struggling to pay off over$250K debt I have... I am in my mid 30s and have no $$$ or energy to switch careers, become any actual physician, or even do Caribbean online MD. What's honestly out there for 7 year trained DPMs to do at his point if our skillset can be done by every other speciality?

Apply every VA hospital job you can find if typical hospital jobs are not available. There are so many VA podiatry jobs out there that are in terrible locations. It's still an option. Lastly you could look into locums. There are always random podiatry locums jobs popping up. It might be just a 3 month contract but you can make significant money. Like 140-150K for 3 months work in some scenarios. Sign up for every locums company you can find. They will email you when a job pops up.I, like many graduating residents are heading to ACFAS 2026 in hopes for recruitment / job opportunities. The job market is bleak and none of the attendings at my program are helpful with job assistance (they're all hospital employed and have worked there 10+ years. They all live in their own bubble not understanding the struggles of many of their DPM colleagues). The offers we are getting are typically by Upperline Health and big private equity group in the region with some PP offering sub 150k. I looked into the military as I've seen multiple healthcare recruitment advertisements with sign on bonuses / loan repayment program that sounds like a sweet deal but as soon as I get in contact with them they tell me "Podiatry is not part of the medical or dental corps so the offer does not apply or Podiatry services are not needed". It is frustrating to see MD, DO, DDS, DMD, OD, PharmD, PT, OT, PA, NP, CRNA jobs in demand in the military with lucrative sign on bonuses yet Podiatry is not even considered? To add to insult, Podiatry is considered as allied health care in the military sharing ranks and pay with non-doctorate or no residency required fields.
Because I'm originally from an urban/suburban city and my program also is located in that demographic area, it is my desire to be employed at the similar setting. Knowing how saturated my hometown or any other city that seems desirable, I am so discouraged that I may end up either at some rural place or working low salary at PP struggling to pay off over$250K debt I have... I am in my mid 30s and have no $$$ or energy to switch careers, become any actual physician, or even do Caribbean online MD. What's honestly out there for 7 year trained DPMs to do at his point if our skillset can be done by every other speciality?
This 1099 locums covering pods who are on vacation or nursing homes? I mean it's do-able but mostly chip n clip / callus kinda deal similar to mobile podiatry?Apply every VA hospital job you can find if typical hospital jobs are not available. There are so many VA podiatry jobs out there that are in terrible locations. It's still an option. Lastly you could look into locums. There are always random podiatry locums jobs popping up. It might be just a 3 month contract but you can make significant money. Like 140-150K for 3 months work in some scenarios. Sign up for every locums company you can find. They will email you when a job pops up.
Advertisement - Members don't see this ad
No its not. They typically are looking for surgical coverage as well as wound care. Prob some routine mixed in as well. You won't know unless you put yourself out there. Nobody is knocking down your door. Sometimes you need to create your own luck.This 1099 locums covering pods who are on vacation or nursing homes? I mean it's do-able but mostly chip n clip / callus kinda deal similar to mobile podiatry?
D
deleted1218629
I agree going locums until you land what you want is far more viable than taking a job you hate/grossly underpaid. Plus the shorter contracts mean you get out of there after 3-6 months so never feel locked in or tied down. Sometimes locums can become permanent if you do a great job and there's a need. l think this is great advice for early career if you can make it happen and have the will for it. The VA job market seems to be a lot less viable lately. There are very few postings anymore. I am not sure if that is due to policy changes or if those jobs just get snatched up, probably both.

This may be true until last week.Apply every VA hospital job you can find if typical hospital jobs are not available. There are so many VA podiatry jobs out there that are in terrible locations. It's still an option.
VA is undergoing a major restructuring now and in the process they have pretty much eliminated around 30k jobs including provider positions. The vacant jobs will just be eliminated. The VA is turning into a giant referral coordinator for community care, effective 2026.
Apply every VA hospital job you can find if typical hospital jobs are not available. There are so many VA podiatry jobs out there that are in terrible locations. It's still an option. Lastly you could look into locums. There are always random podiatry locums jobs popping up. It might be just a 3 month contract but you can make significant money. Like 140-150K for 3 months work in some scenarios. Sign up for every locums company you can find. They will email you when a job pops up.
I've always had this question actually.
How does locums even work for licensing (state pod board and DEA) since there is no "permanent address"?
If these are 1-3 month contracts, how does it work if the next gig is in a different state? You have to get a new state license for every state every 1-3 months? If someone is able to do travel locums, they likely don't have any family responsibilities at the time, so they probably would be able to go to all 50 states if needed, but practically speaking from a licensing and credentialing standpoint, I am not sure how that works.
I know there's MD/DO that do it. Do they have medical licenses in 20 different states? lol
A significant number of podiatry Locums gigs are at IHS facilities where you can generally work with any state license. But yes, otherwise you have to be licensed in each state you work in. MD/DOs can now participate in an interstate medical license program, where you get licensed in a participating state and the rest of the states in the pact will offer expedited licensure if you were to apply (for a Locums gig in a new state, for example).
Locums is getting closer to being a viable career option for an increasing number of DPMs. As hospital and large MSG positions increase, so will the need for call/clinic coverage during times of provider turnover. It’s hard to do for an extended period of time as a podiatrist currently.
It makes complete sense because the quality of VA care is poor. Plus the providers that work there are not motivated. It's not uncommon for podiatry clinics to be booked out months because the DPMs will only do 30 minute visits and work the bare minimum hours.This may be true until last week.
VA is undergoing a major restructuring now and in the process they have pretty much eliminated around 30k jobs including provider positions. The vacant jobs will just be eliminated. The VA is turning into a giant referral coordinator for community care, effective 2026.
My residency we rotated at a VA for a couple of months per year. It was by far the busiest clinic at the VA - I think we saw on average about 60-80 patients a day (2 providers) with residents doing most of the actual work (nails and wounds mostly). The attendings tried as hard as possible to do nothing other than just be there signing off on our notes. I guarantee they would be seeing less than half of that if residents were not there.
I rotated at a couple of other services at that VA (gen surg and derm). They considered 10-12 patients a day to be a busy clinic day!
I rotated at a couple of other services at that VA (gen surg and derm). They considered 10-12 patients a day to be a busy clinic day!
This is true that VA is undergoing major restructuring, where they will be combining various VISNs together to form larger "regions." The current VA Podiatry positions that are posted on USAJOBS will not likely be eliminated since those eliminated positions would have already been removed from USAJOBS and other pending positions that may be on the chopping block would have been put on "hold" and not be allowed to be posted.This may be true until last week.
VA is undergoing a major restructuring now and in the process they have pretty much eliminated around 30k jobs including provider positions. The vacant jobs will just be eliminated. The VA is turning into a giant referral coordinator for community care, effective 2026.

Not holding out much hope that the "internal" only position that I wanted that never filled will be coming back.
VA providers are now held accountable for RVU production as of FY 25. For example, at the level 1 VA facilities, the targeted FY 25 RVU for Podiatry was a little over 6000 with the minimum threshold RVU productivity of 5300. So, any Podiatry services that fall below the minimum threshold RVU would be held accountable by the medical center and VISN leadership. Yes. some of the Podiatry services at VA facilities that have residents and students working in the clinics will likely meet the RVU productivity measures based on the work of the students and residents. However, there are many Podiatry services at VAs with no students and residents in clinic that have not only met the target, but far exceed the targeted RVU productivity measures, such as my VA Podiatry service. My VA Podiatry service does not have any residents or students working in clinics with us. The only time that we work with Podiatry residents from one of the affiliated teaching hospitals will be for our surgical cases in the OR, where the residents will mainly cover our MIS, total ankle replacement, foot and ankle trauma, foot and ankle reconstructive, and some limb salvage cases. Each non surgical DPM provider sees about 20 - 30 patients a day. Each surgical DPM provider sees about 15 - 25 patients a day due to our postop patients and complicated wound cases. In addition to clinic patients, the surgical DPM providers at my VA take call and see inpatient consults without resident support. The Podiatry service at my VA facility is a full foot and ankle service, where we do all surgeries from toes to ankles (trauma to reconstruction to limb salvage) since Ortho are too busy to deal with the ankle stuff. We are somewhat unique in that we are also referral center from other VA hospitals in the region of the US for surgery, such as MIS procedures, total ankle replacements, more advanced foot and ankle reconstruction, second opinions, and revisional surgery for poor outcomes done by both VA and non VA providers (via community care). Like other VAs, we do see our fair share of routine foot care, wounds, etc... However, part of our high RVU productivity is likely from our surgical casesMy residency we rotated at a VA for a couple of months per year. It was by far the busiest clinic at the VA - I think we saw on average about 60-80 patients a day (2 providers) with residents doing most of the actual work (nails and wounds mostly). The attendings tried as hard as possible to do nothing other than just be there signing off on our notes. I guarantee they would be seeing less than half of that if residents were not there.
I rotated at a couple of other services at that VA (gen surg and derm). They considered 10-12 patients a day to be a busy clinic day!
Last edited:
This may be true until last week.
VA is undergoing a major restructuring now and in the process they have pretty much eliminated around 30k jobs including provider positions. The vacant jobs will just be eliminated. The VA is turning into a giant referral coordinator for community care, effective 2026.
So I've picked up a small number of VA referrals. 100% with moderate to severe psych dx, coupled with diabetes and chronic foot pain, so the lazy referring doctor just assumes it's diabetic neuropathy and I of all people am the best person to manage it. It's frustrating because the most important thing they need is some actual history taking, which isn't always easy with these pts. I don't know how I can carve time out of my lobster clinic to be the one to do this while an overpaid va doc can't.
Side note: one of these "diabetic neuropathy" pts turned out to have a high ankle sprain with a gaping wide diastasis!
Oh yeah they all have some mental health issues, and wait until they ask you about Nexus letters to get them to that final 5-10% needed to qualify for 100% service connected disability.So I've picked up a small number of VA referrals. 100% with moderate to severe psych dx, coupled with diabetes and chronic foot pain, so the lazy referring doctor just assumes it's diabetic neuropathy and I of all people am the best person to manage it. It's frustrating because the most important thing they need is some actual history taking, which isn't always easy with these pts. I don't know how I can carve time out of my lobster clinic to be the one to do this while an overpaid va doc can't.
Side note: one of these "diabetic neuropathy" pts turned out to have a high ankle sprain with a gaping wide diastasis!
For reference mt saini nurses union is fighting for a 253k average 3rd yr nurse compensation. They already have about 165k.
So starting 2026 most of the 2k nurses will be earning probably 180k total comp or more for 40hrs not including overtime potential. Two thousand employees. There’s plenty of money out there, and it ain’t going to podiatrists.
So starting 2026 most of the 2k nurses will be earning probably 180k total comp or more for 40hrs not including overtime potential. Two thousand employees. There’s plenty of money out there, and it ain’t going to podiatrists.

Lmao. Nothing more annoying than VA patients hitting you up in private practice for documentation to try and fudge their service disability.Oh yeah they all have some mental health issues, and wait until they ask you about Nexus letters to get them to that final 5-10% needed to qualify for 100% service connected disability.
Brother I do not exist in this system. I am not a VA doctor. You might’ve got your nail fungus from basic training who knows..
For reference mt saini nurses union is fighting for a 253k average 3rd yr nurse compensation. They already have about 165k.
So starting 2026 most of the 2k nurses will be earning probably 180k total comp or more for 40hrs not including overtime potential. Two thousand employees. There’s plenty of money out there, and it ain’t going to podiatrists.
I know plenty of nurses making 175-210K. RN's, not NP's, and multiple, not just some one-off. There's payslips and expected compensation for RN's from the hospital itself floating around on reddit if you look hard enough if you want more proof lol.
NP's and PA's in my state make 180-250k range for all the systems/HMO's/groups. When I was in college 12 years ago volunteering for a homeless clinic, a newer PA I became friends with was making 220k....back then. I haven't spoken to him in years, but he's probably near as makes no difference 300k now.
On Marit, the pods in my area range from 130-320k, with most in the 201-220K category. There is a practice offering 110k (sure, it's just the base, but still) here for a new associate.
Let that sink in hahaha
Advertisement - Members don't see this ad
It is probably due to no VA provider willing to provide the documentation to fudge their service disability.Lmao. Nothing more annoying than VA patients hitting you up in private practice for documentation to try and fudge their service disability.
Brother I do not exist in this system. I am not a VA doctor. You might’ve got your nail fungus from basic training who knows..
It should be noted that many of the community care referrals are from primary care or other medical / mental health / surgical / emergency medical providers and NOT from Podiatry themselves. Podiatry will refer patient out to community care if they do not provide a certain service, such as surgery, or their wait time exceeds 28 days.So I've picked up a small number of VA referrals. 100% with moderate to severe psych dx, coupled with diabetes and chronic foot pain, so the lazy referring doctor just assumes it's diabetic neuropathy and I of all people am the best person to manage it. It's frustrating because the most important thing they need is some actual history taking, which isn't always easy with these pts. I don't know how I can carve time out of my lobster clinic to be the one to do this while an overpaid va doc can't.
Side note: one of these "diabetic neuropathy" pts turned out to have a high ankle sprain with a gaping wide diastasis!
If VA is doing RVU productivity are they getting RVU incentive bonuses? Or are they still stuck at the same lame salary? If they give providers RVU production bonuses then the VA system just got a lot better and will attract higher caliber candidates.VA providers are now held accountable for RVU production as of FY 25. For example, at the level 1 VA facilities, the targeted FY 25 RVU for Podiatry was a little over 6000 with the minimum threshold RVU productivity of 5300. So, any Podiatry services that fall below the minimum threshold RVU would be held accountable by the medical center and VISN leadership. Yes. some of the Podiatry services at VA facilities that have residents and students working in the clinics will likely meet the RVU productivity measures based on the work of the students and residents. However, there are many Podiatry services at VAs with no students and residents in clinic that have not only met the target, but far exceed the targeted RVU productivity measures, such as my VA Podiatry service. My VA Podiatry service does not have any residents or students working in clinics with us. The only time that we work with Podiatry residents from one of the affiliated teaching hospitals will be for our surgical cases in the OR, where the residents will mainly cover our MIS, total ankle replacement, foot and ankle trauma, foot and ankle reconstructive, and some limb salvage cases. Each non surgical DPM provider sees about 20 - 30 patients a day. Each surgical DPM provider sees about 15 - 25 patients a day due to our postop patients and complicated wound cases. In addition to clinic patients, the surgical DPM providers at my VA take call and see inpatient consults without resident support. The Podiatry service at my VA facility is a full foot and ankle service, where we do all surgeries from toes to ankles (trauma to reconstruction to limb salvage) since Ortho are too busy to deal with the ankle stuff. We are somewhat unique in that we are also referral center from other VA hospitals in the region of the US for surgery, such as MIS procedures, total ankle replacements, more advanced foot and ankle reconstruction, second opinions, and revisional surgery for poor outcomes done by both VA and non VA providers (via community care). Like other VAs, we do see our fair share of routine foot care, wounds, etc... However, part of our high RVU productivity is likely from our surgical cases
I cannot speak for other VAs, but I am sure that there are some VAs that do, My VA has RVU productivity as part of our annual pay for performance bonus. My VA has been looking at RVU productivity of providers in Surgical Services and made it a part of the pay for performance bonus for several years, even before the national RVU productivity requirements came out. The sad reality is that I know of some of my VA Podiatry colleagues at other VAs are not even aware about the new RVU productivity requirements.If VA is doing RVU productivity are they getting RVU incentive bonuses? Or are they still stuck at the same lame salary? If they give providers RVU production bonuses then the VA system just got a lot better and will attract higher caliber candidates.
As for recruitment, when my VA was recruiting for DPMs, we had well over 100 applicants. We ended up hiring two fellowship trained DPMs, whom have helped to further develop our surgical services (MIS for example) at my VA. The last several hires that were fresh out from residency or fellowship have been able to attain the case volume and diversity to sit for ABFAS case review within 1 to 2 years of being hired. Majority of them have stayed on at my VA after getting board certified.
Last edited:
Is that in CA or something and how many extra shifts are they pulling? Most I’ve ever heard PA/NP getting paid was ~200k and they were picking up extra shifts regularly. Nurses most I have heard of around my area was ~85k.I know plenty of nurses making 175-210K. RN's, not NP's, and multiple, not just some one-off. There's payslips and expected compensation for RN's from the hospital itself floating around on reddit if you look hard enough if you want more proof lol.
NP's and PA's in my state make 180-250k range for all the systems/HMO's/groups. When I was in college 12 years ago volunteering for a homeless clinic, a newer PA I became friends with was making 220k....back then. I haven't spoken to him in years, but he's probably near as makes no difference 300k now.
On Marit, the pods in my area range from 130-320k, with most in the 201-220K category. There is a practice offering 110k (sure, it's just the base, but still) here for a new associate.
Let that sink in hahaha
Similar threads

- Replies
- 310
- Views
- 33K


