

-
CycleTrack and SDN are teaming up to make medical school admissions more transparent and accessible! Read the announcement to learn how we’re supporting the future of CycleTrack’s free application-tracking tools .
You are using an out of date browser. It may not display this or other websites correctly.
You should upgrade or use an alternative browser.
You should upgrade or use an alternative browser.
Pictures of the Week
Started by Epidural

Get help with your application
Use all the free resources available to you from SDN: articles, guides, expert advising, forums discussions, and school research.
View attachment 243279
Axial back pain, chronic. 60 y/o female. HLA B27 neg. PMH: DM, HTN. No h/o CA. No prior back surgery.
DISH variant? Getting CT ordered. Any idea what is going on here?
the AP looks like AS, but there are no bridging syndesmophytes on lateral. i think it is just OA, or call it DISH if you like. do an MBB
the AP looks like AS, but there are no bridging syndesmophytes on lateral. i think it is just OA, or call it DISH if you like. do an MBB
Here is the oblique. Will get CT before trying MBB, really to see if this getting into canal and if I have viable targets to acquire.
Advertisement - Members don't see this ad
View attachment 243281
Here is the oblique. Will get CT before trying MBB, really to see if this getting into canal and if I have viable targets to acquire.
it does look funky. almost like calcification of the supraspinus ligament
Normal Ca over several years. No PTH on file. Might order with alk phos/phos. Or ask Rheum or PCP to do.
Really pretty contrast spread on a CESI (contralateral oblique approach, nice posterior epidural spread but saw some little wisps going anterior so I grabbed an AP too - you can see it highlighting the nerve roots, especially on the left).
Attachments


Love those crooked spines. And the double cross to get leads in position. Left IS left.Her implant healed up.


Under things I’ve never seen before...
Lemme guess. Presents with SIJ pain
So I have no idea what I am looking at. But I do have the report. Thinking Freddy or Oreos could probably get it.
Guess the underlying problem.
View attachment 244671
So I have no idea what I am looking at. But I do have the report. Thinking Freddy or Oreos could probably get it.
Guess the underlying problem.
Popliteal aneurysm?
partially thrombosed pseudoanyreusm?
Synovial proliferation from RA compressing artery and vein in popliteal fossa.
Advertisement - Members don't see this ad


Synovial proliferation from RA compressing artery and vein in popliteal fossa.
Per Radiologist, get MRI. Changing referral from Ortho to Vascular. Looks like a popliteal aneurysm at this point. I know a CTA is getting done prior to surgery.
View attachment 244798
Per Radiologist, get MRI. Changing referral from Ortho to Vascular. Looks like a popliteal aneurysm at this point. I know a CTA is getting done prior to surgery.
So I called it right?! Hahah
Sent from my iPhone using SDN
GDS: Ghost dens syndrome

Last edited:
No kypho for this guy.
ouch
screw above and below with rods in between?
...shocked no one liked my unhappy dens...
He was braced up for a couple months but did not have surgery. He had multiple other injuries that precluded pretty much anything else. I just see him for some medial branch blocks now and again.ouch
screw above and below with rods in between?
Severe pain with twisting and leaning forward. Better with extension and Baclofen. Going to try bracing.

Single bone spine. Has a touch of AS.
im only seeing blobogram. sorry...
im only seeing blobogram. sorry...
Exactly, that is the image I saw on my patient's old records. Contrast everywhere but epidural. This is the nonsense that my competition gets away with.
Do 2 adjacent levels and perhaps some medication will be epidural.
Referral for new patient. Dropped off mri ahead of visit. Had scs trial elsewhere. MRI when they could not get wires in. Asked me to retrial. No thanks.
Advertisement - Members don't see this ad
View attachment 248351 View attachment 248352
Referral for new patient. Dropped off mri ahead of visit. Had scs trial elsewhere. MRI when they could not get wires in. Asked me to retrial. No thanks.
And that’s why all my patients get thoracic MRIs before the trial. A surgeon would never cut without imaging and we would never inject without imaging. Never made sense why that all went out the window when it came to stim.
Random one but I get EMG referrals. This was a weird case because the patient was referred twice within 3 weeks. First referral for new onset LUE painless weakness followed by second for new onset LLE painless weakness. I sent him to the ER. Passed away 9 months later. Metastatic renal cell.
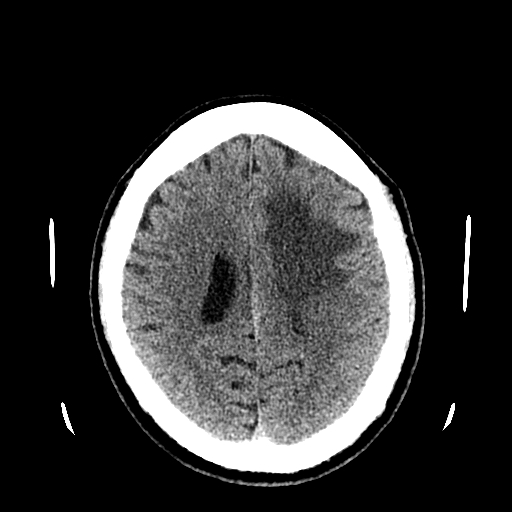
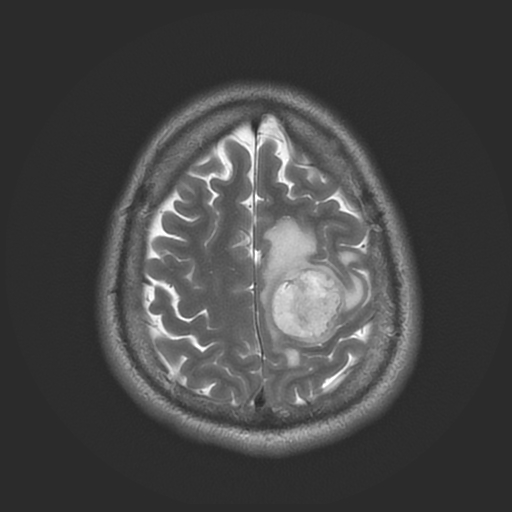
@lobelsteve
You didn’t do this, did you?
What is the metal south of the scrotum?
You didn’t do this, did you?
What is the metal south of the scrotum?
Scrotum? Maybe im wrong but i see frontal and lateral skull...dentures/fillings@lobelsteve
You didn’t do this, did you?
What is the metal south of the scrotum?
Looks like pns for headache
I believe he’s referring to Dr Lobel’s scrotum, not the patient’s.Scrotum? Maybe im wrong but i see frontal and lateral skull
Done by Neurosurgeon at Emory. I recommended against it. Patient no better.
One lead supraorbital, 1 lead through foramen ovale and an inch into brain.
Gasserian RF trajectory with a 14G Tuohy and leaving a wire is more than I imagine reasonable.
Offered SCS over C2 in the canal for her primary V2 right sided pain.
One lead supraorbital, 1 lead through foramen ovale and an inch into brain.
Gasserian RF trajectory with a 14G Tuohy and leaving a wire is more than I imagine reasonable.
Offered SCS over C2 in the canal for her primary V2 right sided pain.
Man I was really disoriented.
I thought the fillings were a goofy pns IPG and the leads were obterator and femoral. Geez.
And this was done on a little person with very odd hip dysplasia
Done by Neurosurgeon at Emory. I recommended against it. Patient no better.
One lead supraorbital, 1 lead through foramen ovale and an inch into brain.
Gasserian RF trajectory with a 14G Tuohy and leaving a wire is more than I imagine reasonable.
Offered SCS over C2 in the canal for her primary V2 right sided pain.
Did the pain pattern change as that seems like overkill for V2? I'm sure they already offered to drop Nevro percs at C1/C2 for HF10 to the nucleus caudalis to fix all things above the neck.
Did the pain pattern change as that seems like overkill for V2? I'm sure they already offered to drop Nevro percs at C1/C2 for HF10 to the nucleus caudalis to fix all things above the neck.
elavil to start, 250k later, elavil +/- butrans
Dont forget, a publication in some neurosurgeon journal documenting 80% reduction of pain until lost to follow up...
Advertisement - Members don't see this ad
42 yo M with just under 3 weeks of severe right leg pain. Driving home one day from work (desk job) and right leg started hurting, then couldn't get out of his car. No medical history. Gainfully employed. Wants to get back to work but does not tolerate even minimal ROM of the leg or weight bearing.
IM Toradol, Medrol dose pack, gabapentin, home exercise regimen, follow up in 3 weeks. Will MRI if no better.
I kept thinking I saw fracture but I'm not so sure. That L4-5 disk has seen better days.
IM Toradol, Medrol dose pack, gabapentin, home exercise regimen, follow up in 3 weeks. Will MRI if no better.
I kept thinking I saw fracture but I'm not so sure. That L4-5 disk has seen better days.
Attachments

Last edited:
42 yo M with just under 3 weeks of severe right leg pain. Driving home one day from work (desk job) and right leg started hurting, then couldn't get out of his car. No medical history. Gainfully employed. Wants to get back to work but does not tolerate even minimal ROM of the leg or weight bearing.
IM Toradol, Medrol dose pack, gabapentin, home exercise regimen, follow up in 3 weeks. Will MRI if no better.
I kept thinking I saw fracture but I'm not so sure. That L4-5 disk has seen better days.
MRI now. Cant get out of car is red flag enough for me.
The posterior inferior L4 body looks... weird. I’d agree with MRI now too. Definitely enough on physical exam to justify to insurance. Reflexes normal and bowel/bladder normal I assume?42 yo M with just under 3 weeks of severe right leg pain. Driving home one day from work (desk job) and right leg started hurting, then couldn't get out of his car. No medical history. Gainfully employed. Wants to get back to work but does not tolerate even minimal ROM of the leg or weight bearing.
IM Toradol, Medrol dose pack, gabapentin, home exercise regimen, follow up in 3 weeks. Will MRI if no better.
I kept thinking I saw fracture but I'm not so sure. That L4-5 disk has seen better days.
The posterior inferior L4 body looks... weird. I’d agree with MRI now too. Definitely enough on physical exam to justify to insurance. Reflexes normal and bowel/bladder normal I assume?
Posterior L4 is what I was talking about as looking possibly like fracture, but probably just shadow and bony overlay. The getting out of the car thing was exclusively pain related and not neuromuscular. Reflexes are 2+. No bowel or bladder issues.
42 yo M with just under 3 weeks of severe right leg pain. Driving home one day from work (desk job) and right leg started hurting, then couldn't get out of his car. No medical history. Gainfully employed. Wants to get back to work but does not tolerate even minimal ROM of the leg or weight bearing.
IM Toradol, Medrol dose pack, gabapentin, home exercise regimen, follow up in 3 weeks. Will MRI if no better.
I kept thinking I saw fracture but I'm not so sure. That L4-5 disk has seen better days.
ALIF time
Similar threads


- Replies
- 29
- Views
- 1K

- Replies
- 33
- Views
- 2K
- Replies
- 30
- Views
- 5K
